White blood cell count, especially neutrophil count, as a predictor of hypertension in a Japanese population
Related Experiment Video
Updated: Jun 28, 2026

Intracellular Staining and Flow Cytometry to Identify Lymphocyte Subsets within Murine Aorta, Kidney and Lymph Nodes in a Model of Hypertension
Published on: January 28, 2017
Yoshimi Tatsukawa1, Wan-Ling Hsu, Michiko Yamada
1Department of Clinical Studies, Radiation Effects Research Foundation, 5-2 Hijiyama Park, Minami-ku, Hiroshima 732-0815, Japan.

Although several studies have shown that high WBC count is a risk factor for hypertension, the relationship between WBC count and the incidence of hypertension in Japanese is poorly understood, as are the effects of WBC components on that relationship. Our objective was to verify in a Japanese population whether WBC or differential WBC count predicts hypertension incidence. A total of 9,383 initially hypertension-free subjects (3,356 men and 6,027 women), whose WBC counts were within the normal range (3,000 to < 10,000 cells/mm3), were followed from 1965 to 2004. During this 40-year follow-up, 4,606 subjects developed hypertension. After adjusting for conventional risk factors, including smoking status, we found that elevated WBC count was associated with hypertension incidence in a Cox regression model with both fixed and time-varying covariates for women. For men, elevated WBC count was a significant risk factor for hypertension only in the time-varying Cox-regression covariate. We also observed a significant association between increased neutrophil count and hypertension incidence among women. In a fully adjusted model, the relative risks of hypertension incidence, from the lowest to the highest quartiles of neutrophil count, were 1.00, 1.18, 1.28, and 1.22 in women (p for trend < 0.001). In conclusion, elevated WBC count predicted an increased incidence of hypertension in Japanese, especially among females. Moreover, neutrophils were the major WBC component contributing to the increased risk.
Although several studies have shown that high WBC count is a risk factor for hypertension, the relationship between WBC count and the incidence of hypertension in Japanese is poorly understood, as are the effects of WBC components on that relationship. Our objective was to verify in a Japanese population whether WBC or differential WBC count predicts hypertension incidence. A total of 9,383 initially hypertension-free subjects (3,356 men and 6,027 women), whose WBC counts were within the normal range (3,000 to < 10,000 cells/mm3), were followed from 1965 to 2004. During this 40-year follow-up, 4,606 subjects developed hypertension. After adjusting for conventional risk factors, including smoking status, we found that elevated WBC count was associated with hypertension incidence in a Cox regression model with both fixed and time-varying covariates for women. For men, elevated WBC count was a significant risk factor for hypertension only in the time-varying Cox-regression covariate. We also observed a significant association between increased neutrophil count and hypertension incidence among women. In a fully adjusted model, the relative risks of hypertension incidence, from the lowest to the highest quartiles of neutrophil count, were 1.00, 1.18, 1.28, and 1.22 in women (p for trend < 0.001). In conclusion, elevated WBC count predicted an increased incidence of hypertension in Japanese, especially among females. Moreover, neutrophils were the major WBC component contributing to the increased risk.

Related Concept Videos
 01:18
Hypertension and Regulation of Blood Pressure
 01:28
Factors affecting Blood pressure
Physiological Factors:
 01:30
Blood Pressure
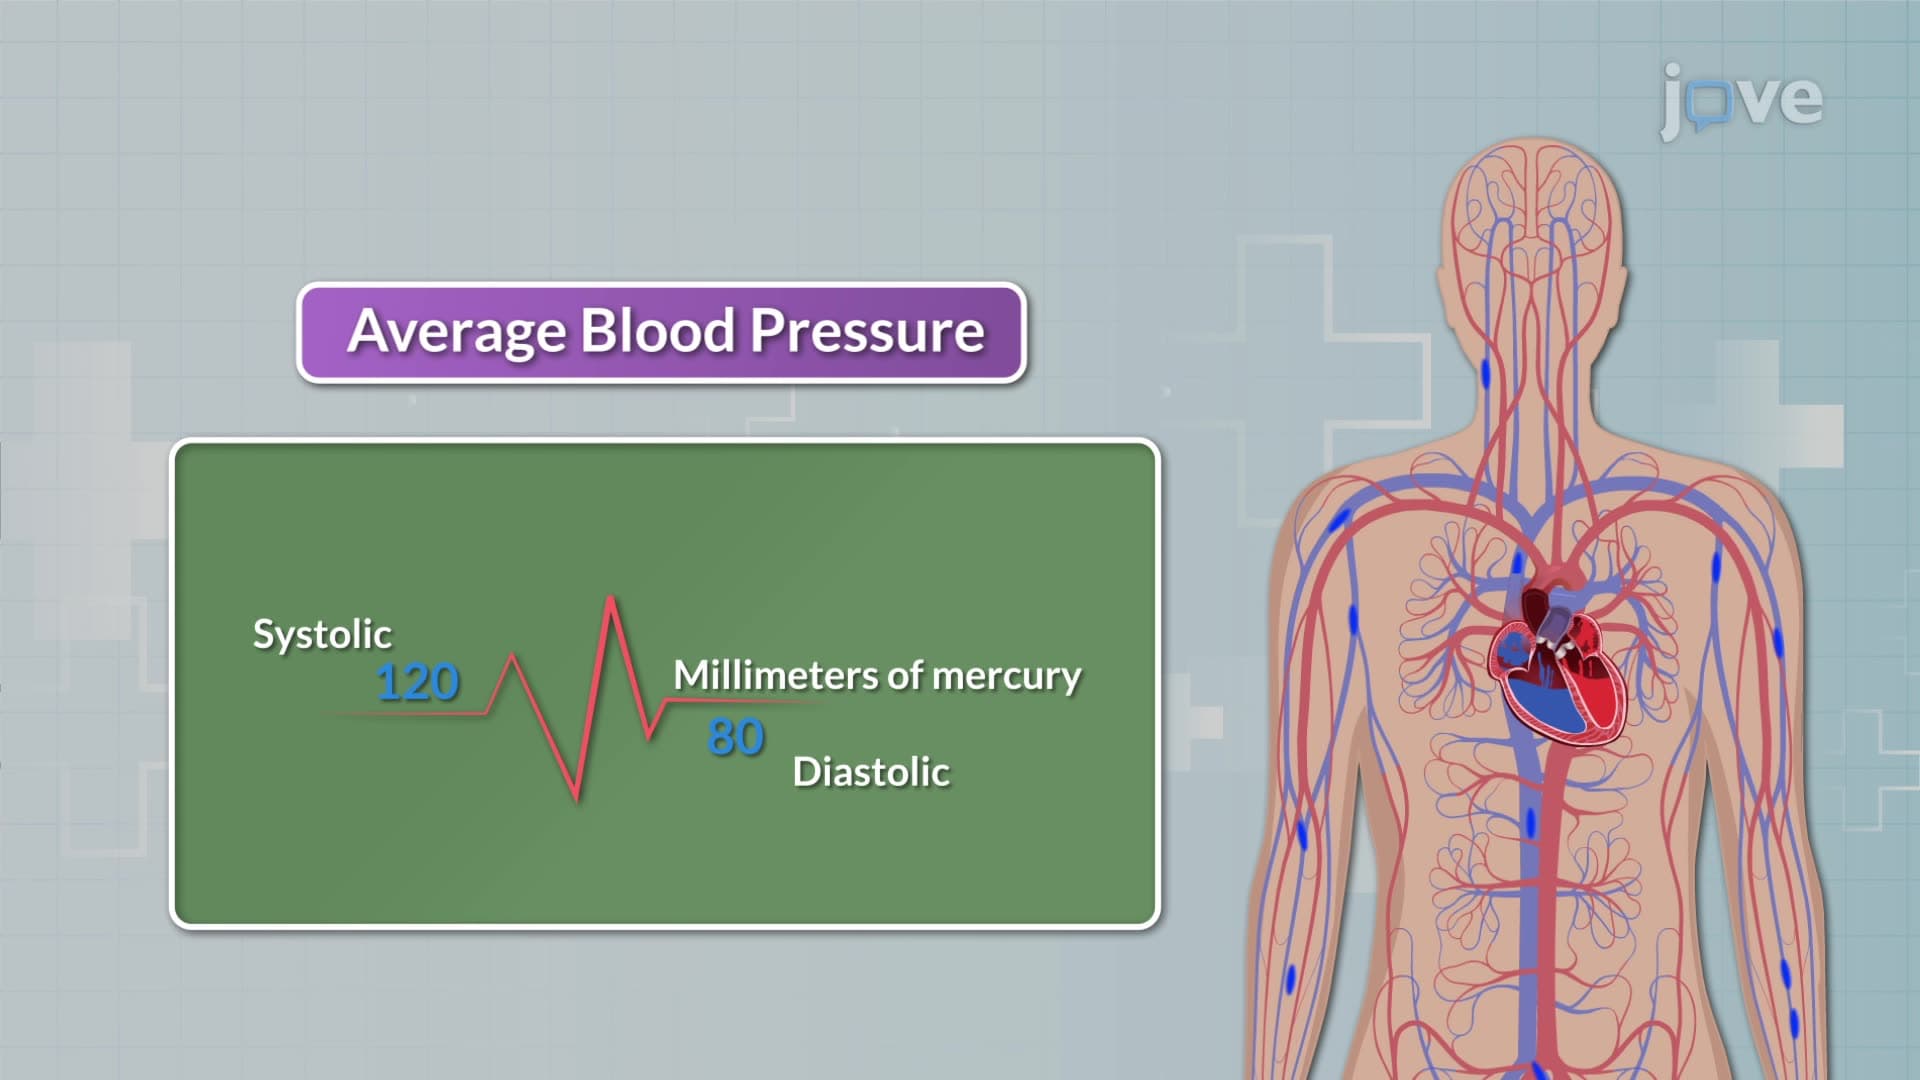
The average BP in an adult is typically around 120/80 mmHg (millimeters of mercury). In this measurement, the numerator (120) indicates the systolic pressure, which is the pressure in the arteries during the contraction of the heart's ventricles as blood is expelled. The denominator (80) represents the diastolic...
 01:24
Blood Pressure
 01:28
Special considerations while measuring blood pressure
Monitoring Both Arms:
Monitoring BP in both arms during the initial assessment is advisable, as the systolic value may differ by five to ten mm Hg between arms. For subsequent BP assessments, use the arm with the higher reading.
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies