Related Experiment Video
Updated: Jun 28, 2026


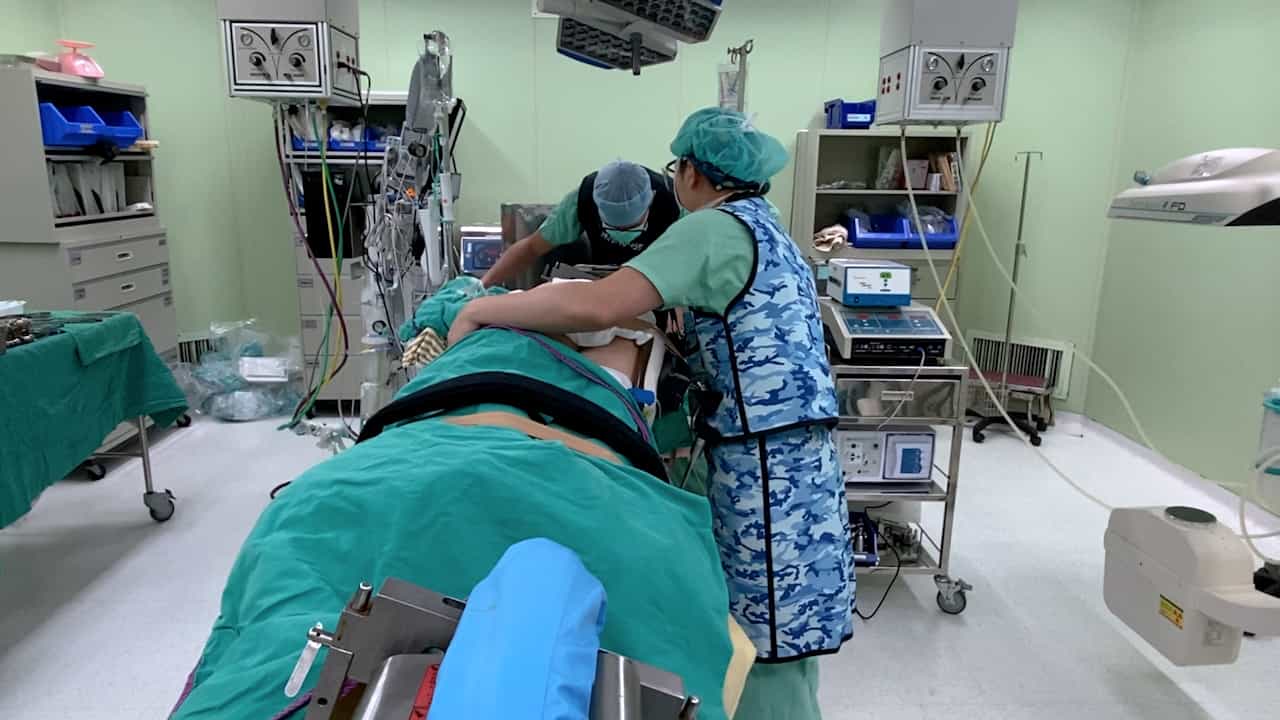
Local Anesthetic Thoracoscopy for Undiagnosed Pleural Effusion
Published on: November 10, 2023
Semi-rigid thoracoscopy for undiagnosed exudative pleural effusions: a comparative study
Zhen Wang1, Zhao-Hui Tong, Hong-Jie Li
1Department of Respiratory Diseases, Beijing Chaoyang Hospital, Beijing Institute of Respiratory Diseases, Capital Medical University, Beijing, China.

Background:
Thoracoscopy is highly sensitive and accurate for detecting pleural effusions. However, most respiratory physicians are not familiar with the use of the more common rigid thoracoscope or the flexible bronchoscope, which is difficult to manipulate within the pleural cavity. The semi-rigid thoracoscope combines the best features of the flexible and rigid instruments. Since the practice with this instrument is limited in China, the diagnostic utility of semi-rigid thoracoscopy (namely medical thoracoscopy) under local anesthesia for undiagnosed exudative pleural effusions was evaluated.
Methods:
In 50 patients with undiagnosed pleural effusions who were studied retrospectively, 23 received routine examinations between July 2004 and June 2005 and the rest 27 patients underwent medical thoracoscopy during July 2005 and June 2006. Routine examinations of the pleural effusions involved biochemistry and cytology, sputum cytology, and thoracentesis. The difference in diagnostic sensitivity, costs related to pleural fluid examination and complications were compared directly between the two groups.
Results:
Medical thoracoscopy revealed tuberculous pleurisy in 6 patients, adenocarcinoma in 7, squamous-cell carcinoma in 2, metastatic carcinoma in 3, mesothelioma in 2, non-Hodgkin's lymphoma in 1, and others in 4. Only 2 patients could not get definite diagnoses. Diagnostic efficiency of medical thoracoscopy was 93% (25/27). Only 21% patients were diagnosed after routine examinations, including parapneumonic effusion in 2 patients, lung cancer in 2 and undetermined metastatic malignancy in 1. Twelve patients with tuberculous pleurisy were suspected by routine examination. Costs related to pleural effusion testing showed no difference between the two groups (P=0.114). Twenty-three patients in the routine examination group underwent 97 times of thoracentesis. Two pleural infection patients and 2 pneumothorax patients were identified and received antibiotic treatment and drainage. Medical thoracoscopy could be well tolerated by all the patients. The semi-rigid thoracoscope could be easily controlled by chest physicians. The most common complication was transient chest pain (20 of 27 patients) from the indwelling chest tube, which would be managed with conventional analgesics. One case of subcutaneous emphysema and 2 cases of postoperative fever were self-limiting. No severe complications occurred.
Conclusions:
Medical thoracoscopy is a simple, safe, and cost-effective tool, with a high positive rate. Physicians should extend its access to proper patients if the facilities for medical thoracoscopy are available.
Related Concept Videos
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:30
Endoscopic Studies I: Bronchoscopy and Thoracoscopy
Bronchoscopy
Description
Bronchoscopy is a procedure that involves direct visualization of the larynx, trachea, and bronchi for diagnostic and therapeutic purposes. A flexible fiber optic or rigid bronchoscope is used to carry out the procedure. The fiber-optic bronchoscope is more frequently used due to...
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:25
Pleural Effusion I: Introduction
There are two main types of pleural effusion: transudative and exudative. They are differentiated using Light's criteria,...
 01:28
Pleural Effusion II: Symptoms and Management
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care