Related Experiment Video
Updated: Jun 28, 2026


Modeling Ascending Vaginal Infection, Preterm Birth, and Neonatal Morbidity in Mice
Published on: October 10, 2025
Uncultivated bacteria as etiologic agents of intra-amniotic inflammation leading to preterm birth
Yiping W Han1, Tao Shen, Peter Chung
1Department of Periodontics, School of Dental Medicine, Case Western Reserve University, 10900 Euclid Avenue, Cleveland, OH 44106-4905, USA. yiping.han@case.edu

Abstract:
Intra-amniotic infection and inflammation are major causes of preterm birth (PTB). However, intra-amniotic inflammation is often detected in the absence of infection. This may partly be due to the culturing methods employed in hospital laboratories, which are unable to detect the uncultivated species. In this study, intra-amniotic microbial infections associated with PTB were examined by both culture and 16S rRNA-based culture-independent methods and were corroborated by the presence of intra-amniotic inflammation. Amniotic fluid (AF) specimens from 46 pregnancies complicated by PTB and 16 asymptomatic women were analyzed. No bacterial DNA was amplified in AF collected from the asymptomatic women. Among the 46 samples associated with PTB, bacterial DNA was amplified from all (16/16) of the culture-positive samples and 17% (5/30) of the culture-negative samples. In the culture-positive group, additional species were detected in more than half (9/16) of the cases by PCR and clone analysis. Altogether, approximately two- thirds of the species detected by the culture-independent methods were not isolated by culture. They included both uncultivated and difficult-to-cultivate species, such as Fusobacterium nucleatum, Leptotrichia (Sneathia) spp., a Bergeyella sp., a Peptostreptococcus sp., Bacteroides spp., and a species of the order Clostridiales. To examine intra-amniotic inflammation, an AF proteomic fingerprint (mass-restricted score) was determined by surface-enhanced laser desorption ionization-time-of-flight mass spectrometry. Inflammation was detected in all five samples which were culture negative but PCR positive. Women who were PCR positive more often had elevated interleukin-6 levels in their AF, histological chorioamnionitis, and funisitis and delivered neonates with early-onset neonatal sepsis. Previously unrecognized, uncultivated, or difficult-to-cultivate species may play a key role in the initiation of PTB.
Insights
Intra-amniotic inflammation often precedes preterm birth (PTB). This study reveals that uncultivated bacteria, missed by standard cultures, are linked to PTB and inflammation, suggesting a role in initiating premature delivery.
Area of Science:
- Microbiology
- Obstetrics
- Neonatal Health
Background:
- Intra-amniotic infection and inflammation are leading causes of preterm birth (PTB).
- Intra-amniotic inflammation can occur without detectable infection using standard culture methods.
- Limitations in culturing techniques may fail to identify uncultivated or difficult-to-cultivate microbial species.
Purpose of the Study:
- To investigate intra-amniotic microbial infections associated with PTB using both culture and culture-independent methods.
- To correlate microbial findings with the presence of intra-amniotic inflammation.
- To identify microbial species potentially missed by traditional culturing methods in PTB cases.
Main Methods:
- Analysis of amniotic fluid (AF) from 46 PTB pregnancies and 16 asymptomatic controls.
- Bacterial DNA amplification using 16S rRNA-based culture-independent methods.
- Proteomic fingerprinting of AF via surface-enhanced laser desorption ionization-time-of-flight mass spectrometry to assess inflammation.
Main Results:
- Bacterial DNA was detected in all culture-positive PTB samples and 17% of culture-negative PTB samples.
- Culture-independent methods identified numerous species not isolated by culture, including uncultivated and difficult-to-cultivate bacteria.
- Inflammation was detected in culture-negative, PCR-positive samples, which were associated with elevated IL-6, histological chorioamnionitis, funisitis, and neonatal sepsis.
Conclusions:
- Previously unrecognized, uncultivated, or difficult-to-cultivate microbial species may play a significant role in initiating PTB.
- Culture-independent methods are crucial for detecting a broader spectrum of microbes associated with PTB.
- The presence of these microbes correlates with intra-amniotic inflammation and adverse neonatal outcomes.

Related Concept Videos
 01:28
Development of the Oral Microbiota
 01:24
Bacterial Meningitis
 01:30
Development of Human Microbiota
 01:28
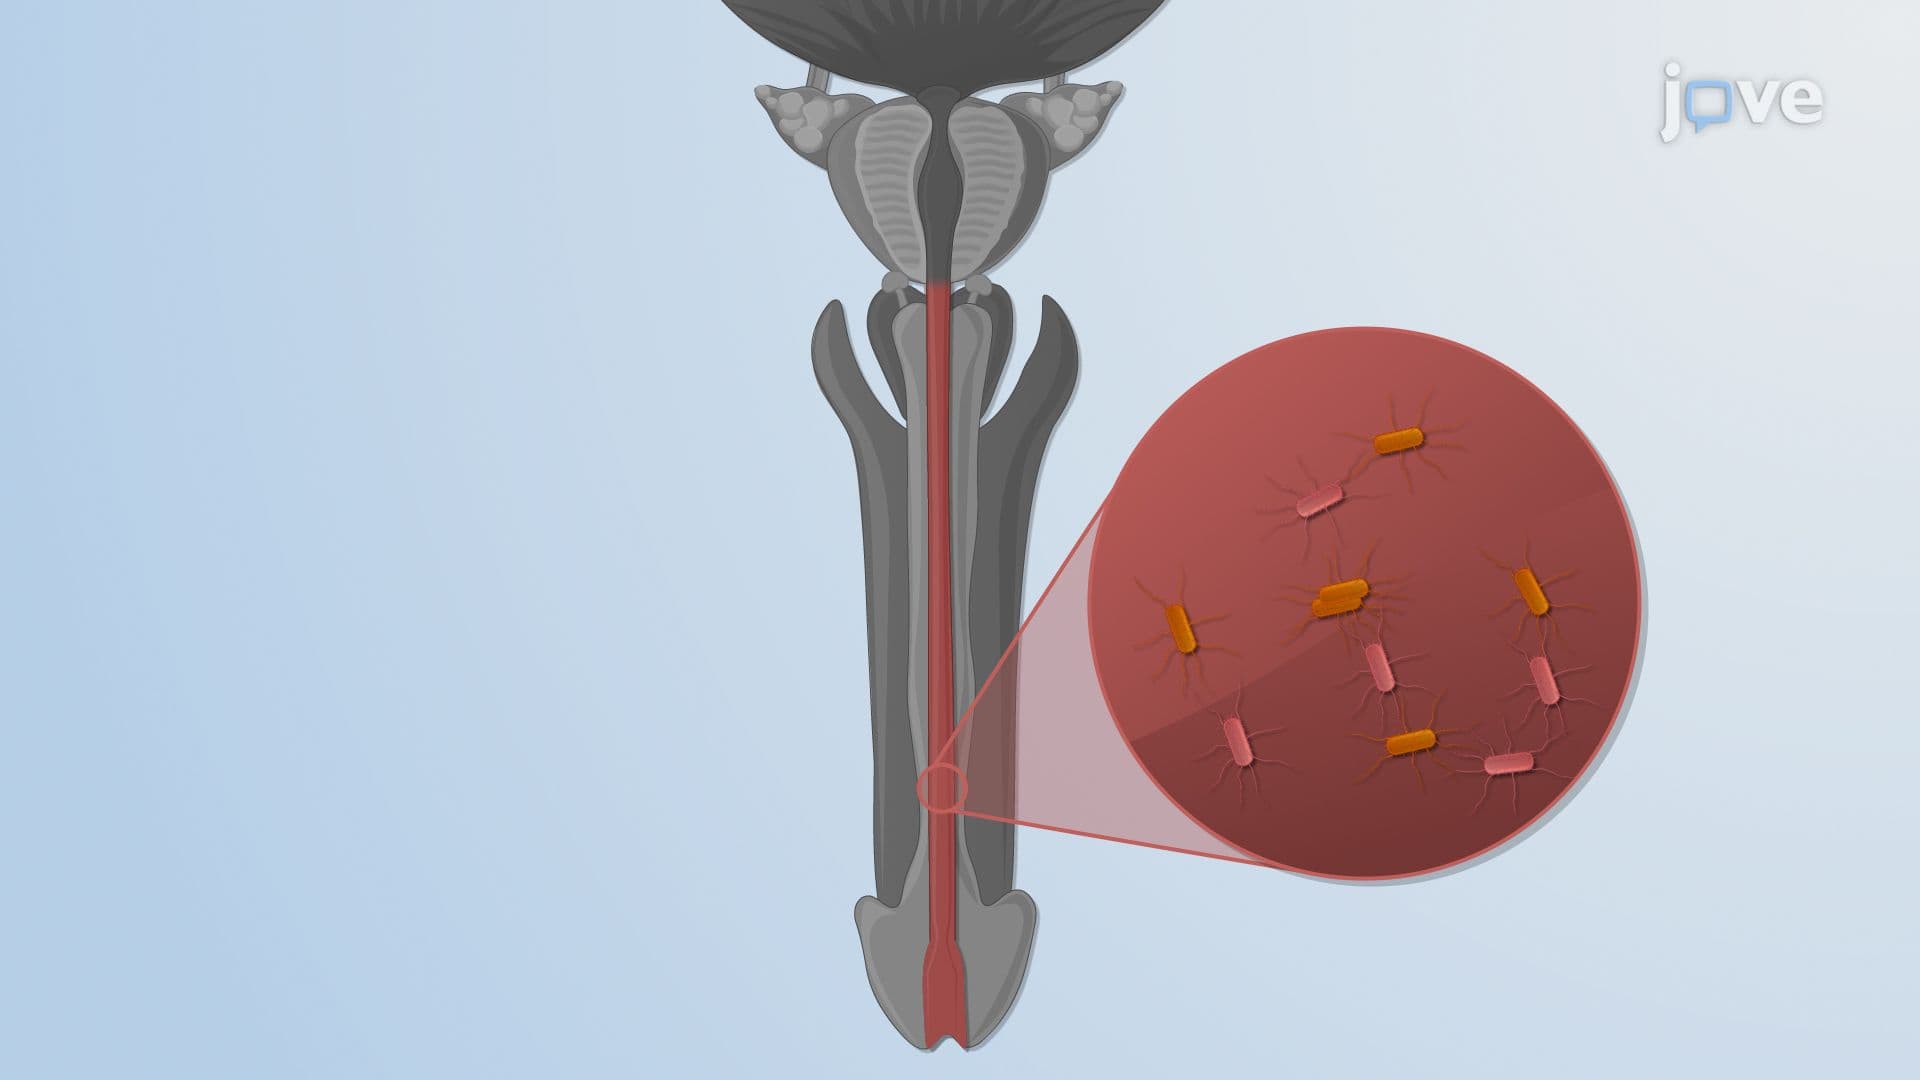
Microbiota of the Urogenital Tract
 01:22
Introduction to the Human Microbiota
 01:26
Bacterial Meningitis II: Pathophysiology