Related Experiment Video
Updated: Jun 28, 2026


In Vivo Telemetry to Record Long-Term Cardiovascular Parameters, Temperature, and Activity in Spinal Cord Injury Rat Models
Published on: January 2, 2026
Cardiovascular complications after acute spinal cord injury: pathophysiology, diagnosis, and management
Julio C Furlan1, Michael G Fehlings
1Division of Genetics and Development, Toronto Western Research Institute, University Health Network, Ontario, Canada.

Abstract:
Cardiovascular complications in the acute stage following traumatic spinal cord injury (SCI) require prompt medical attention to avoid neurological compromise, morbidity, and death. In this review, the authors summarize the neural regulation of the cardiovascular system as well as the pathophysiology, diagnosis, and management of major cardiovascular complications that can occur following acute (up to 30 days) traumatic SCI. Hypotension (both supine and orthostatic), autonomic dysreflexia, and cardiac arrhythmias (including persistent bradycardia) are attributed to the loss of supraspinal control of the sympathetic nervous system that commonly occurs in patients with severe spinal cord lesions at T-6 or higher. Current evidence-based guidelines recommend: 1) monitoring of cardiac and hemodynamic parameters in the acute phase of SCI; 2) maintenance of a minimum mean arterial blood pressure of 85 mm Hg during the hyperacute phase (1 week after SCI); 3) timely detection and appropriate treatment of neurogenic shock and cardiac arrhythmias; and 4) immediate and adequate treatment of episodes of acute autonomic dysreflexia. In addition to these forms of cardiovascular dysfunction, individuals with acute SCIs are at high risk for deep venous thrombosis (DVT) and pulmonary embolism due to loss of mobility and, potentially, altered fibrinolytic activity, abnormal platelet function, and impaired circadian variations of hemostatic and fibrinolytic parameters. Current evidence supports a recommendation for thromboprophylaxis using mechanical methods and anticoagulants during the acute stage up to 3 months following SCI, depending on the severity and level of injury. Low-molecular-weight heparin is the first choice for anticoagulant prophylaxis in patients with acute SCI. Although there is insufficient evidence to recommend (or refute) the use of screening tests for DVT in asymptomatic adults with acute SCI, this strategy may detect asymptomatic DVT in at least 9.4% of individuals who undergo thromboprophylaxis using lowmolecular- weight heparin. Indications and treatment of DVT and acute pulmonary embolism are well established and are summarized in this review. Recognition of cardiovascular complications after acute SCI is essential to minimize adverse outcomes and to optimize recovery.
Related Concept Videos
 01:25
Secondary Spinal Cord Injury llI: Pathophysiology
 01:14
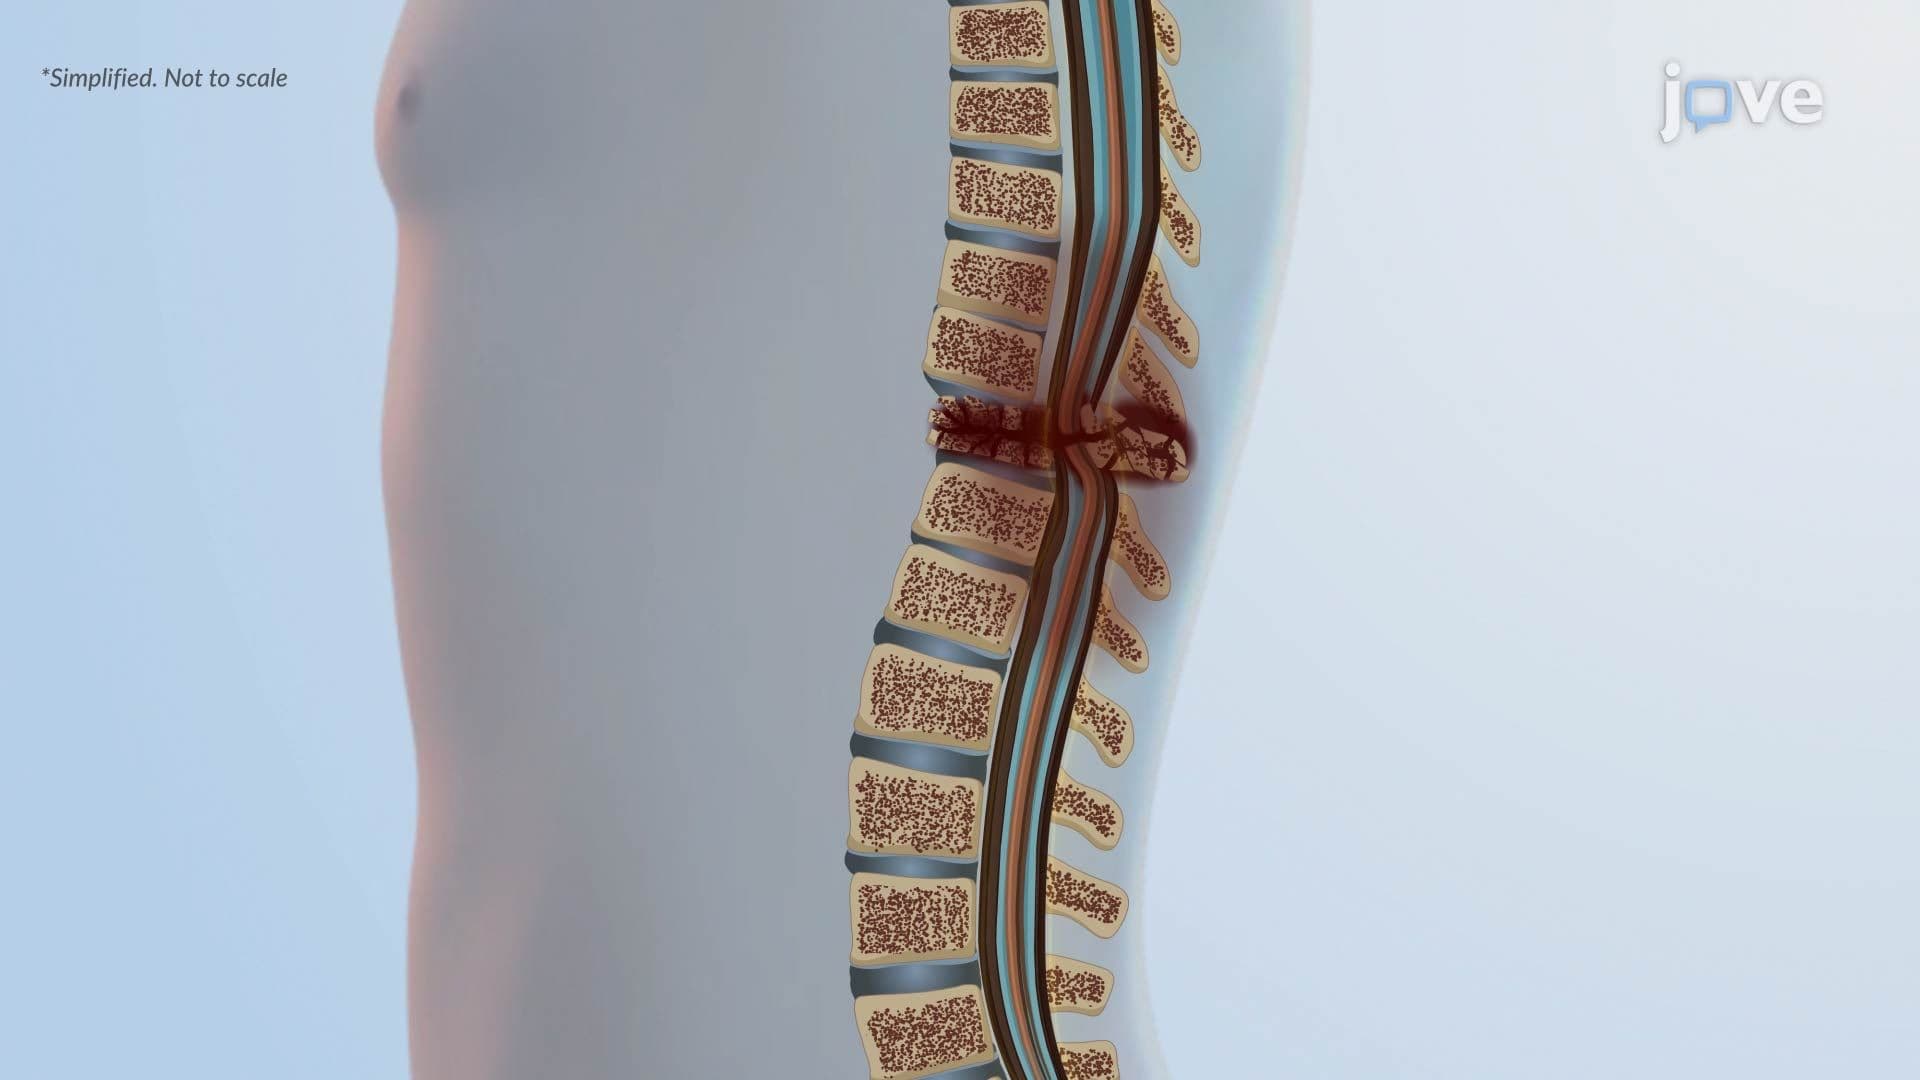
Spinal Cord Injury ll: Pathophysiology
 01:15
Ischemic Stroke ll: Pathophysiology
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:28
Acute Coronary Syndrome IV: Interprofessional Care