Related Experiment Video
Updated: Jun 28, 2026


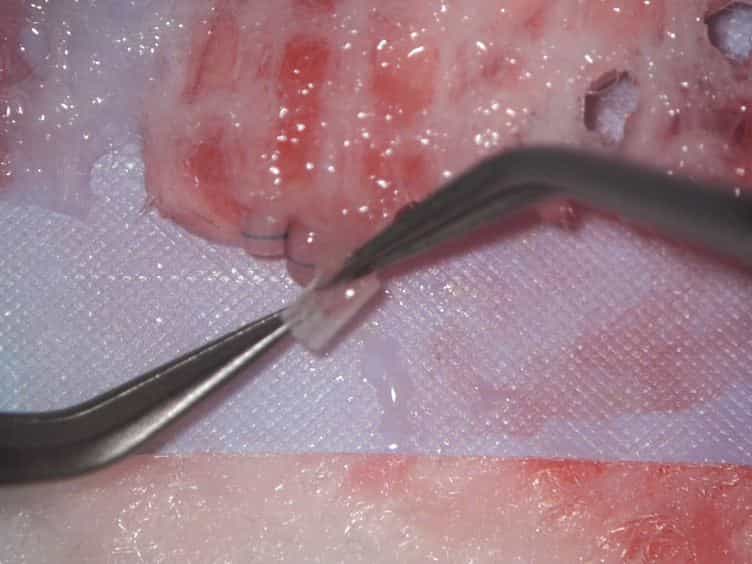
Murine Intrapulmonary Tracheal Transplantation: A Model for Investigating Obliterative Airway Disease After Lung Transplantation
Published on: November 10, 2023
Airway complications after lung transplantation: risk factors, prevention and outcome
Walter Weder1, Ilhan Inci, Stephan Korom
1University Hospital, Division of Thoracic Surgery, University of Zurich, Switzerland. walter.weder@usz.ch

Purpose:
Anastomotic complications following lung transplantation (LuTx) have been described in up to 15% of patients. Challenging to treat, they are associated with high morbidity and a mortality rate of 2-5%. The aim of this study was to analyze the incidence of complications in a consecutive series of bronchial anastomosis after LuTx at our center and to delineate the potential risk factors.
Methods:
Between 1992 and 2007, 441 bronchial anastomoses were performed in 235 patients. Indications for transplantation were cystic fibrosis (35.7%) emphysema (28.1%) pulmonary fibrosis (12.8%) and pulmonary hypertension (7.7%). There were 206 sequential bilateral and 28 single transplants including lobar engraftments in 20 cases. The donor bronchus was shortened to the plane of the lobar carina including the medial wall of the intermediate bronchus. Peribronchial tissue was left untouched. Anastomosis was carried out using a continuous absorbable running suture (PDS 4/0) at the membranous and interrupted sutures at the cartilaginous part. Six elective surveillance bronchoscopies were done monthly during the first half-year post-LuTx, with detailed assessment of the pre- and post-anastomotic airways.
Results:
One-year survival since 2000 was 90.5%. In all 441 anastomoses performed, no significant dehiscence was observed. In one patient, a small fistula was detected and closed surgically on postoperative day five. Fungal membranes were found in 50% of the anastomoses at 1 month and in 14% at 6 months. Discrete narrowing of the anastomotic lumen without need for intervention was found in 4.9% of patients at 1 month and in 2.4% at 6 months. Age, cytomegalovirus status, induction therapy, immunosuppressive regimen, ischemic time, and ventilation time had no influence on bronchial healing.
Conclusions:
Clinically relevant bronchial anastomotic complications after LuTx can be avoided by use of a simple standardized surgical technique. Aggressive antibiotic and antifungal therapy might play an important supportive role.

Related Concept Videos
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD:
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed.
 01:16
Kidney Transplant III: Nursing Management
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:28
Kidney Transplant I: Introduction