Related Experiment Video
Updated: Jun 28, 2026
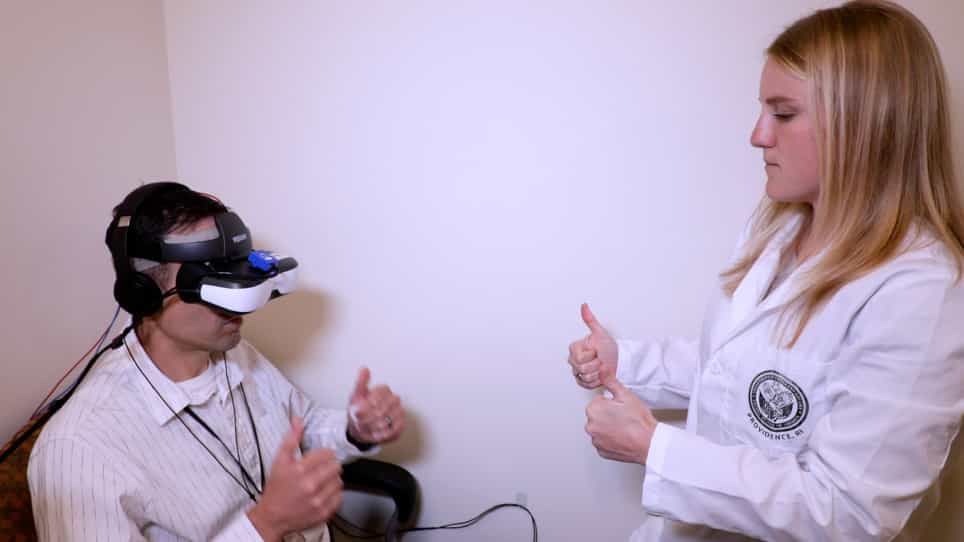

Simultaneous Application of Transcranial Direct Current Stimulation during Virtual Reality Exposure
Published on: January 18, 2021
[Therapeutic possibilities after traumatic experiences]
1Klinik für Psychiatrie, Medizinische Universität Graz, Auenbruggerplatz 31, Graz, Austria. Hans-peter.kapfhammer@klinikum-graz.at

Abstract:
Acute stress disorder (ASD) and posttraumatic stress disorder (PTSD) are frequent, but not obligatory psychological sequelae following trauma. A major subgroup of patients face a chronic course of illness associated with an increased psychiatric comorbidity and significant impairments in psychosocial adaptation. The typical psychopathological symptoms of ASD and PTSD are best described within a multifactorial model integrating both neurobiological and psychosocial influences. The complex etiopathogenesis of acute and posttraumatic stress disorder favours multimodal approaches in the treatment. Differential psychotherapeutic and pharmacological strategies are available. In a critical survey on empirical studies, psychological debriefing cannot be considered as a positive approach to be recommended as general preventive measure during the immediate posttraumatic phase. Positive effects of cognitive-behavioral interventions can be established for ASD. Psychodynamic psychotherapy, cognitive-behavioral therapy and EMDR show promising results in the treatment of PTSD. Major clinical restrictions of patient sampling within special research facilities, however, do not allow an unconditional generalization of these data to psychiatric routine care. In an empirical analysis the SSRIs are the most and best studied medications for ASD and PTSD. In comparison to tricyclic antidepressants SSRIs demonstrate a broader spectrum of therapeutic effects and are better tolerated. The substance classes of SSNRI, DAS, SARI and NaSSA are to be considered as drugs of second choice. They promise a therapeutic efficacy equivalent to the SSRIs, being investigated so far only in open studies. MAO-inhibitors may dispose of a positive therapeutic potential, their profile of side effects must be respected, however. Mood stabilizers and atypical neuroleptics may be used first and foremost in add-on strategies. Benzodiazepines should be used only with increased caution for a short time in states of acute crisis. In early interventions, substances blocking the norepinephric hyperactivity seem to be promising alternatives. Stress doses of hydrocortisone may be considered as an experimental pharmacological strategy so far.
More Related Videos
 09:55
Use of a Psychophysiological Script-driven Imagery Experiment to Study Trauma-related Dissociation in Borderline Personality Disorder
Published on: March 8, 2018
 09:29
Stereotactic Atlas-Guided Laser Capture Microdissection of Brain Regions Affected by Traumatic Injury
Published on: September 11, 2017
Related Concept Videos
 01:20
Traumatic Memory
 01:28
Psychotherapy
 01:27
Post-traumatic Stress Disorder
Symptoms and Behavioral Manifestations
A spectrum of distressing symptoms characterizes PTSD. Recurrent flashbacks, where individuals involuntarily relive traumatic events, are a...
 01:26
Group Therapy
 01:24
Humanistic Therapy
 01:29
Psychodynamic Therapy