Related Experiment Video
Updated: Jul 20, 2026

DNBS/TNBS Colitis Models: Providing Insights Into Inflammatory Bowel Disease and Effects of Dietary Fat
Published on: February 27, 2014
The influence of zinc status and malnutrition on immunological function in Crohn's disease
C Ainley1, J Cason, B M Slavin
1Department of Gastroenterology, St. Thomas' Hospital, London, England.

Abstract:
Cellular immunity is likely to be important in the pathogenesis of Crohn's disease; whether it is abnormal is not clear. The heterogeneity of patients with Crohn's disease probably underlies the disparity of reports, but attempts to determine which clinical features influence cellular immunity have been largely unsuccessful. This is probably caused by the omission of nutritional status as a potential factor, even though zinc deficiency has frequently been linked with abnormal immunity. Therefore, a detailed study of nutritional and tissue zinc status, nonspecific cellular immunity, and a measure of phagocytic function was performed in 32 patients with Crohn's disease and in a control group of 18 normal subjects and 12 patients with anorexia nervosa. Fourteen patients with Crohn's disease, all patients with anorexia nervosa, but none of the normal controls were malnourished. Peripheral blood lymphocyte population levels were normal in patients with Crohn's disease and in normal controls, but there was a small decrease in the levels of patients with anorexia nervosa. In vivo delayed hypersensitivity skin test responses were profoundly depressed in patients with anorexia nervosa and decreased in patients with Crohn's disease who were malnourished or receiving systemic glucocorticoids. In vitro lymphocyte transformation was reduced in malnourished patients with Crohn's disease, but there were only minor changes in patients with anorexia nervosa. There were alterations of in vitro immunoregulation in Crohn's disease, but they were not responsible for the abnormal lymphocyte transformation responses in malnourished patients. In vitro phagocytic function was reduced in patients with active Crohn's disease. These findings suggest that depressed in vivo and in vitro cellular immunity in malnourished patients with Crohn's disease is caused by a qualitative lymphocyte defect and that depressed in vivo but normal in vitro cellular immunity in anorexia nervosa is caused by a quantitative defect. Thus, malnutrition in Crohn's disease resembles kwashiorkor; in anorexia nervosa, it resembles marasmus. Tissue zinc status was mostly normal in Crohn's disease and anorexia nervosa, and zinc deficiency was not responsible for depressed nonspecific cellular immunity in either condition.
More Related Videos


Related Concept Videos
 01:26
Factors Affecting the Risk of Infection
The integrity and count of the white blood cells help the body resist pathogens and fight infection. When impaired, it reduces the body's resistance to pathogens. The acidic pH levels of the gastrointestinal, genitourinary tracts, and skin create...
 01:29
Drugs for Treatment of Crohn's Disease in IBD Using Immunomodulatory Agents
 01:30
Inflammatory Bowel Disease II: Crohn's Disease
Inflammatory bowel disease, commonly known as IBD, refers to a collection of disorders that lead to persistent inflammation of the gastrointestinal tract. The two types of IBD are ulcerative colitis, which impacts the colon, and Crohn's disease, which can involve any part of the gastrointestinal segment.
Crohn's disease
Crohn's disease is a chronic, systemic inflammatory bowel disease (IBD) that predominantly affects the gastrointestinal tract. It is marked by transmural...
 01:30
Inflammatory Bowel Disease III: Diagnostic Studies and Management I-Nutritional Therapy
Diagnostic studies
A colonoscopy is the definitive screening test, distinguishing ulcerative colitis from other colon diseases with similar symptoms. During a colonoscopy test, inflamed mucosa with exudate ulcerations can be observed, and biopsies are taken to determine the histologic characteristics of the colonic...
 01:18
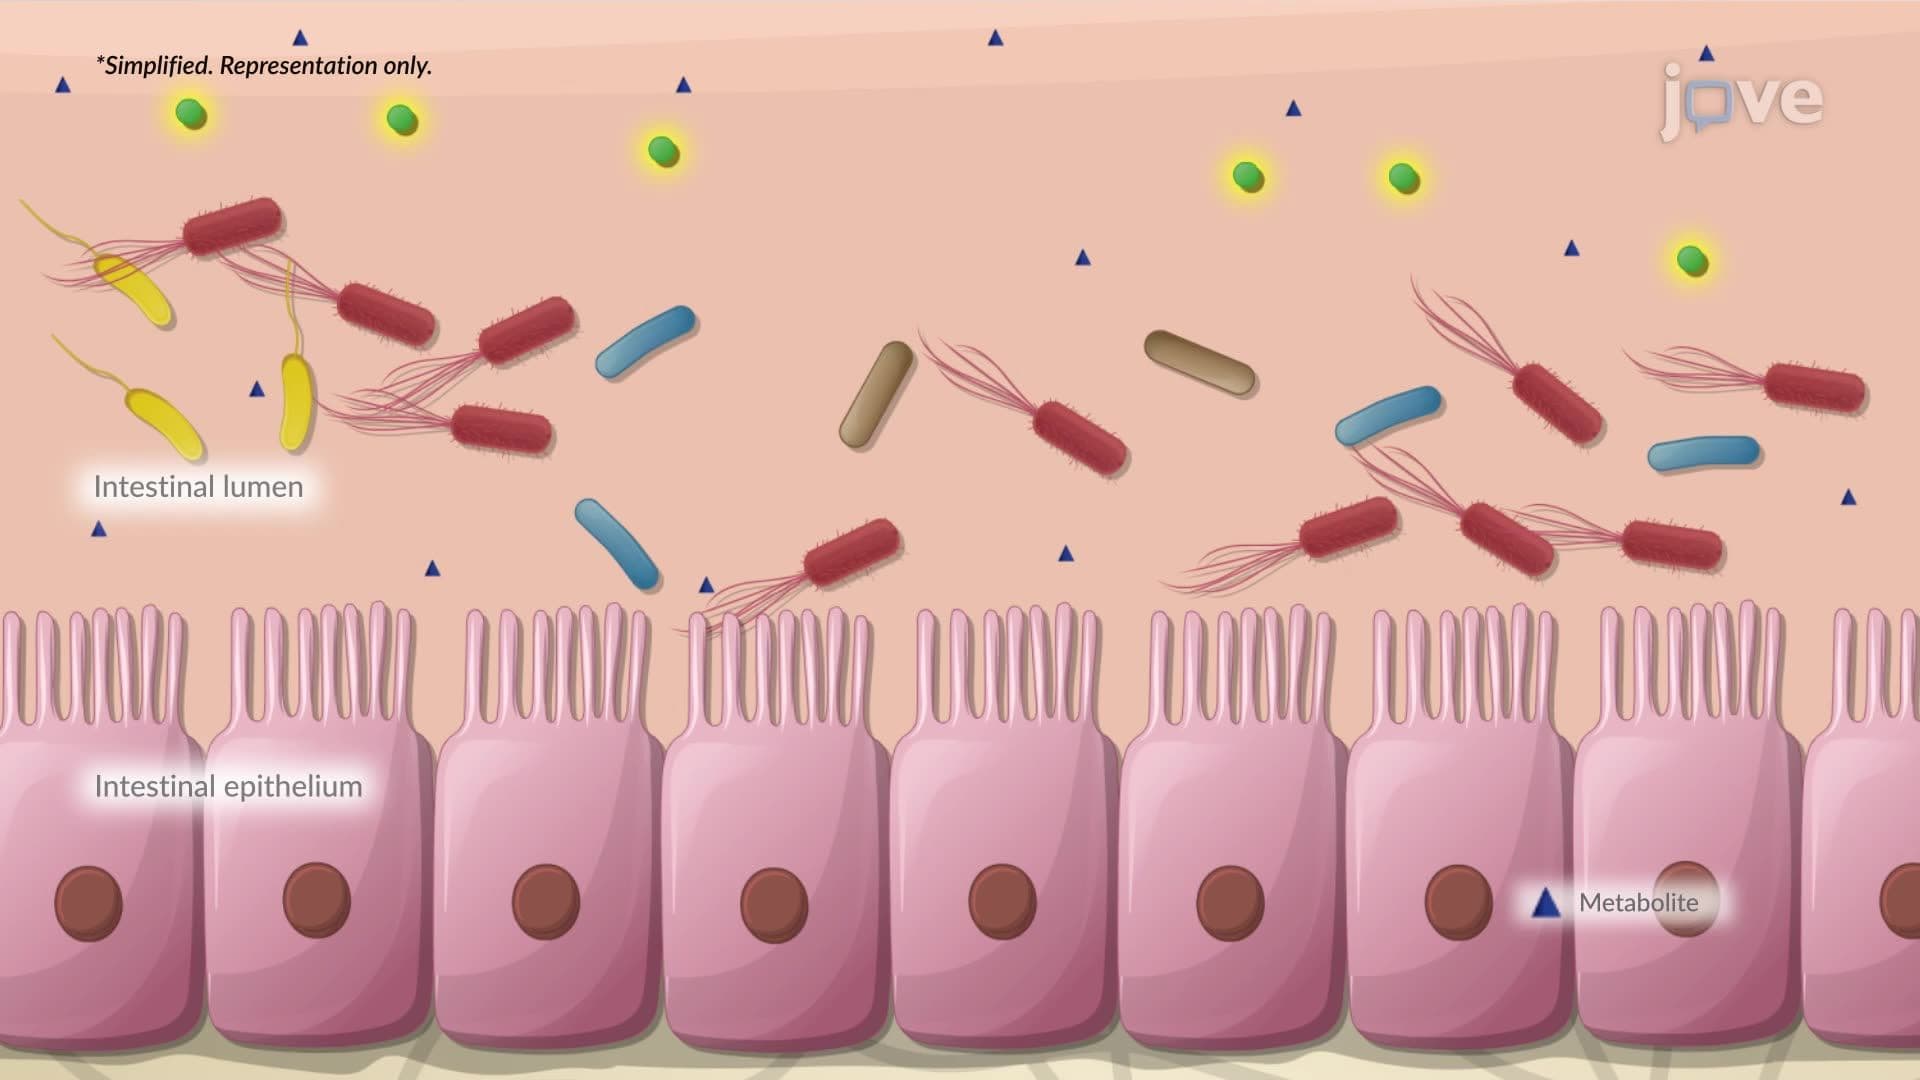
Dysbiosis of the Gut Microbiota
 01:25
Inflammatory Bowel Disease III: Crohn's Disease