Related Experiment Video
Updated: Jun 27, 2026

Intradermal Microdialysis: An Approach to Investigating Novel Mechanisms of Microvascular Dysfunction in Humans
Published on: July 21, 2023
Driving forces behind increasing cardiovascular drug utilization: a dynamic pharmacoepidemiological model
Helle Wallach Kildemoes1, Henrik Støvring, Morten Andersen
1Research Unit for General Practice, Institute of Public Health, University of Southern Denmark, Odense, Denmark. hwkildemoes@health.sdu.dk

Insights
Cardiovascular drug use increased significantly due to higher incidence, not population aging. This trend is expected to continue, indicating a pharmacoepidemiological imbalance.
Area of Science:
- Pharmacoepidemiology
- Cardiovascular medicine
- Public health
Background:
- Cardiovascular drug utilization has been increasing.
- Understanding the drivers of this trend is crucial for healthcare planning.
Purpose of the Study:
- To investigate the primary factors contributing to the rising use of cardiovascular drugs.
- To differentiate the impact of population aging versus changes in treatment dynamics.
Main Methods:
- Utilized Danish register data from 1996-2006, tracking cardiovascular drug dispensing.
- Employed a semi-Markov model to analyze treatment incidence, discontinuation, and mortality.
- Assessed the influence of population aging using standardized intensities and prevalences.
Main Results:
- Cardiovascular drug treatment prevalence (ages >=20) rose by 39% (1996-2005), with intensity increasing by 109%.
- Increasing treatment incidence was the main driver, followed by declining discontinuation; population aging had a smaller impact.
- Treatment prevalence continued to increase even when incidence was held constant in models.
Conclusions:
- Rising cardiovascular drug use is driven by increased treatment incidence and prevalence, not solely population aging.
- Pharmacoepidemiological disequilibrium suggests continued growth in treatment prevalence.
- Interventions targeting incidence and discontinuation may be necessary to manage utilization trends.
Aims:
To investigate the driving forces behind increasing utilization of cardiovascular drugs.
Methods:
Using register data, all Danish residents as of 1 January 1996 were followed until 2006. Cohort members were censored at death or emigration. Cardiovascular drug utilization on the individual level was traced, applying registered out-of-hospital dispensing. The impact of population ageing on cardiovascular drug utilization was investigated using standardized intensities and prevalences. Based on a three-state (untreated, treated and dead) semi-Markov model, we explored to what extent increasing treatment prevalence was driven by changing incidence, discontinuation and mortality. Expected treatment prevalences were modelled, applying stratum-specific cohort prevalence in 1996 along with incidence, discontinuation and drug user mortality either throughout 1996-2004 or at fixed 1996 levels.
Results:
Treatment prevalence (ages > or =20 years) with cardiovascular drugs increased by 39% during 1996-2005 from 192.4 to 256.9 per 1000 inhabitants (95% confidence interval 256.5, 257.3). Treatment intensity grew by 109% from 272 to 569 defined daily doses 1000(-1) day(-1). Population 'middle-ageing' accounted for 11.5 and 20.3%, respectively. Increasing treatment incidence was the main driver of the rising treatment prevalence in most drug categories. Declining discontinuation drove some of the growth, declining drug user mortality less. Even with fixed incidence in the model, treatment prevalence continued to increase.
Conclusions:
Age-related increases in treatment intensity and prevalence, rather than population ageing, drove the increasing treatment intensity with cardiovascular drugs. Increasing treatment prevalence in subgroups was primarily caused by increasing incidence. Due to pharmacoepidemiological disequilibrium, treatment prevalence will continue to grow even with unchanged incidence.

Related Concept Videos
 01:09
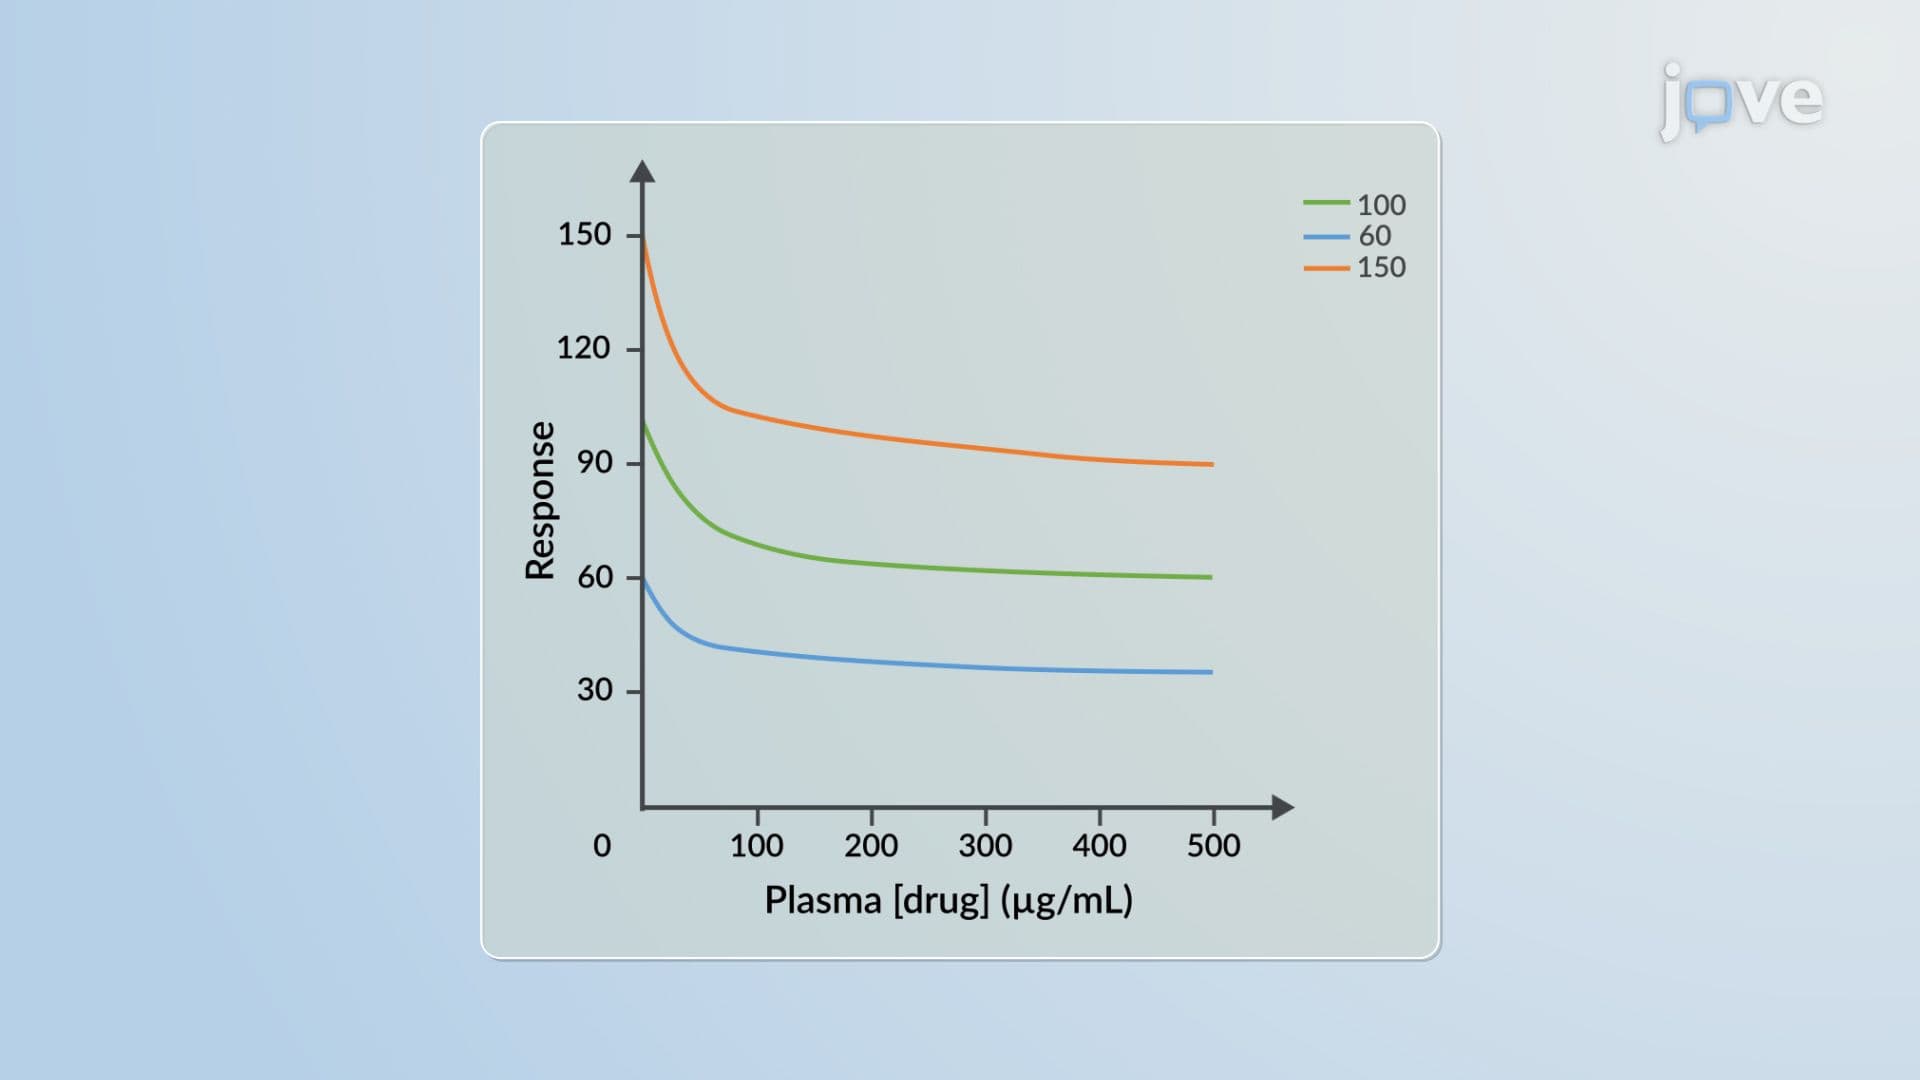
Pharmacodynamic Models: Additive and Proportional Drug Effect Model
 01:18
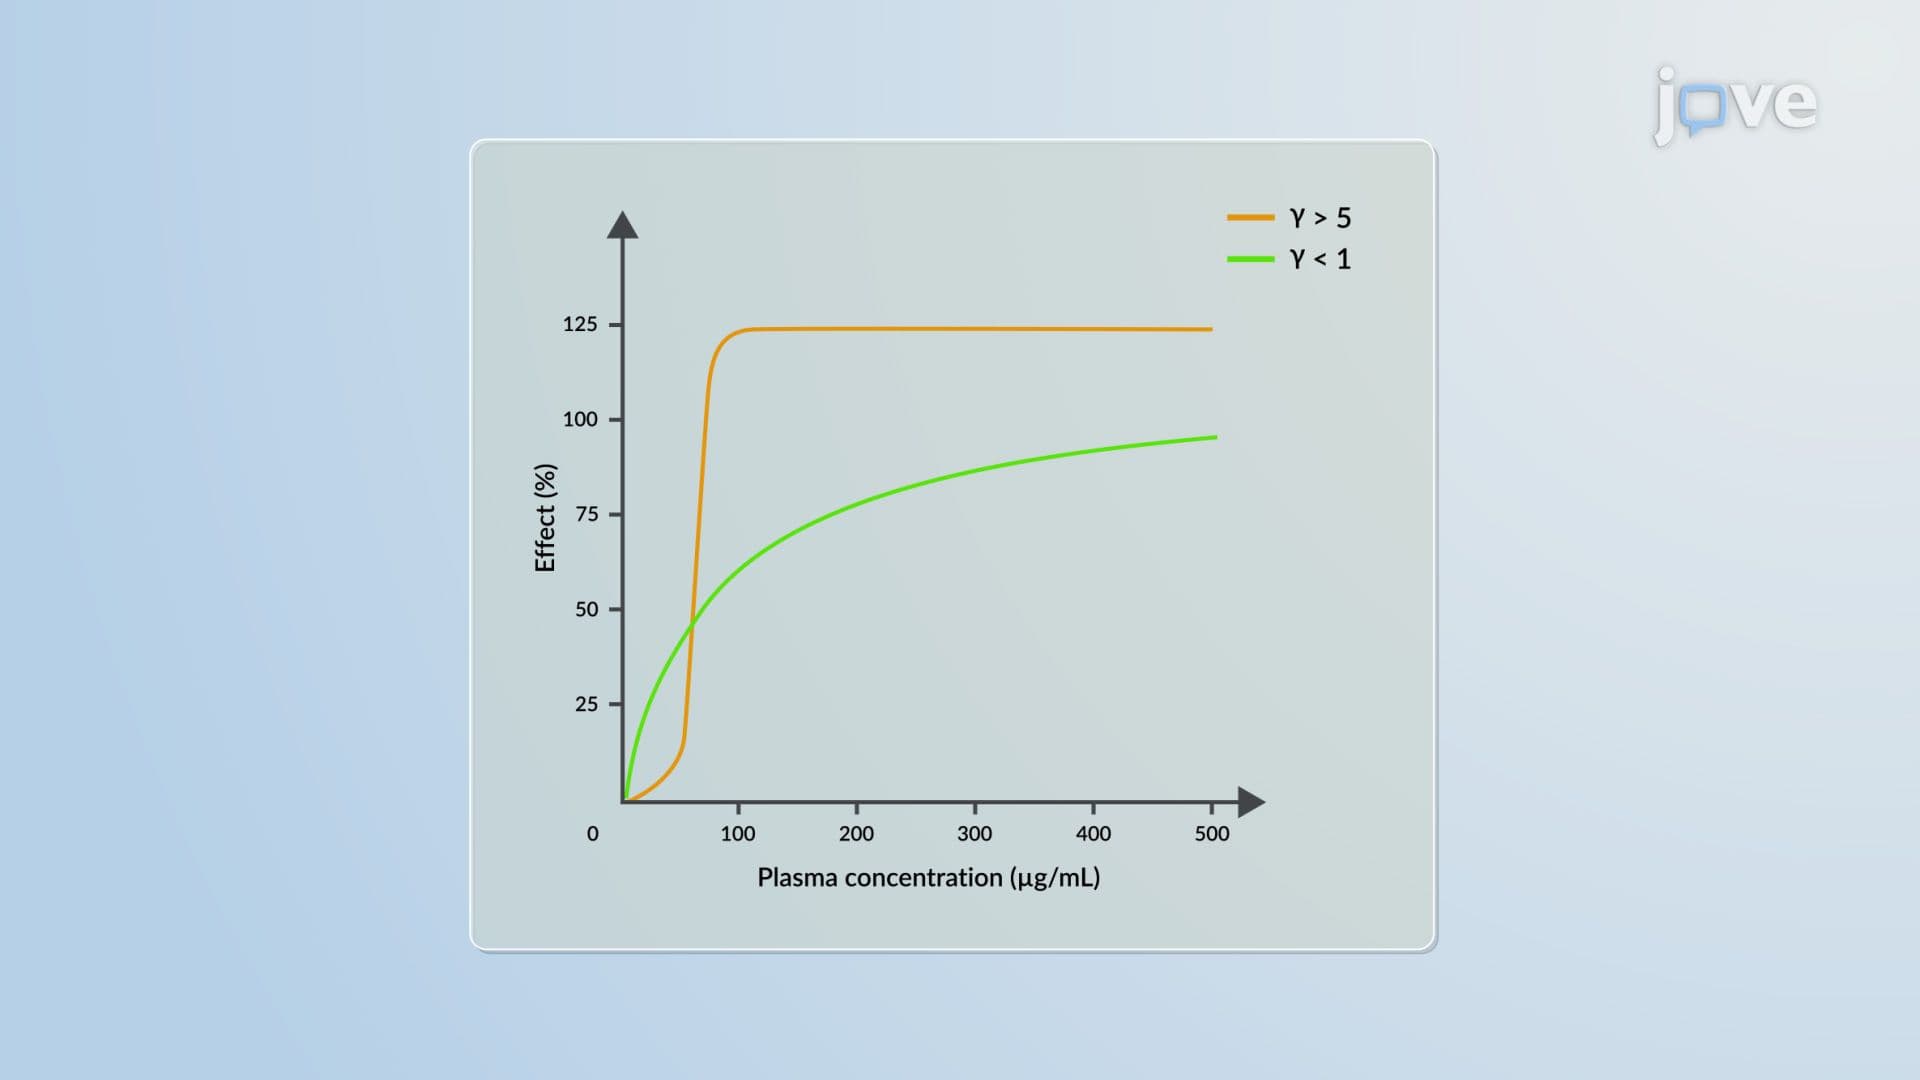
Pharmacodynamic Models: Emax Drug–Concentration Effect Model
 01:29
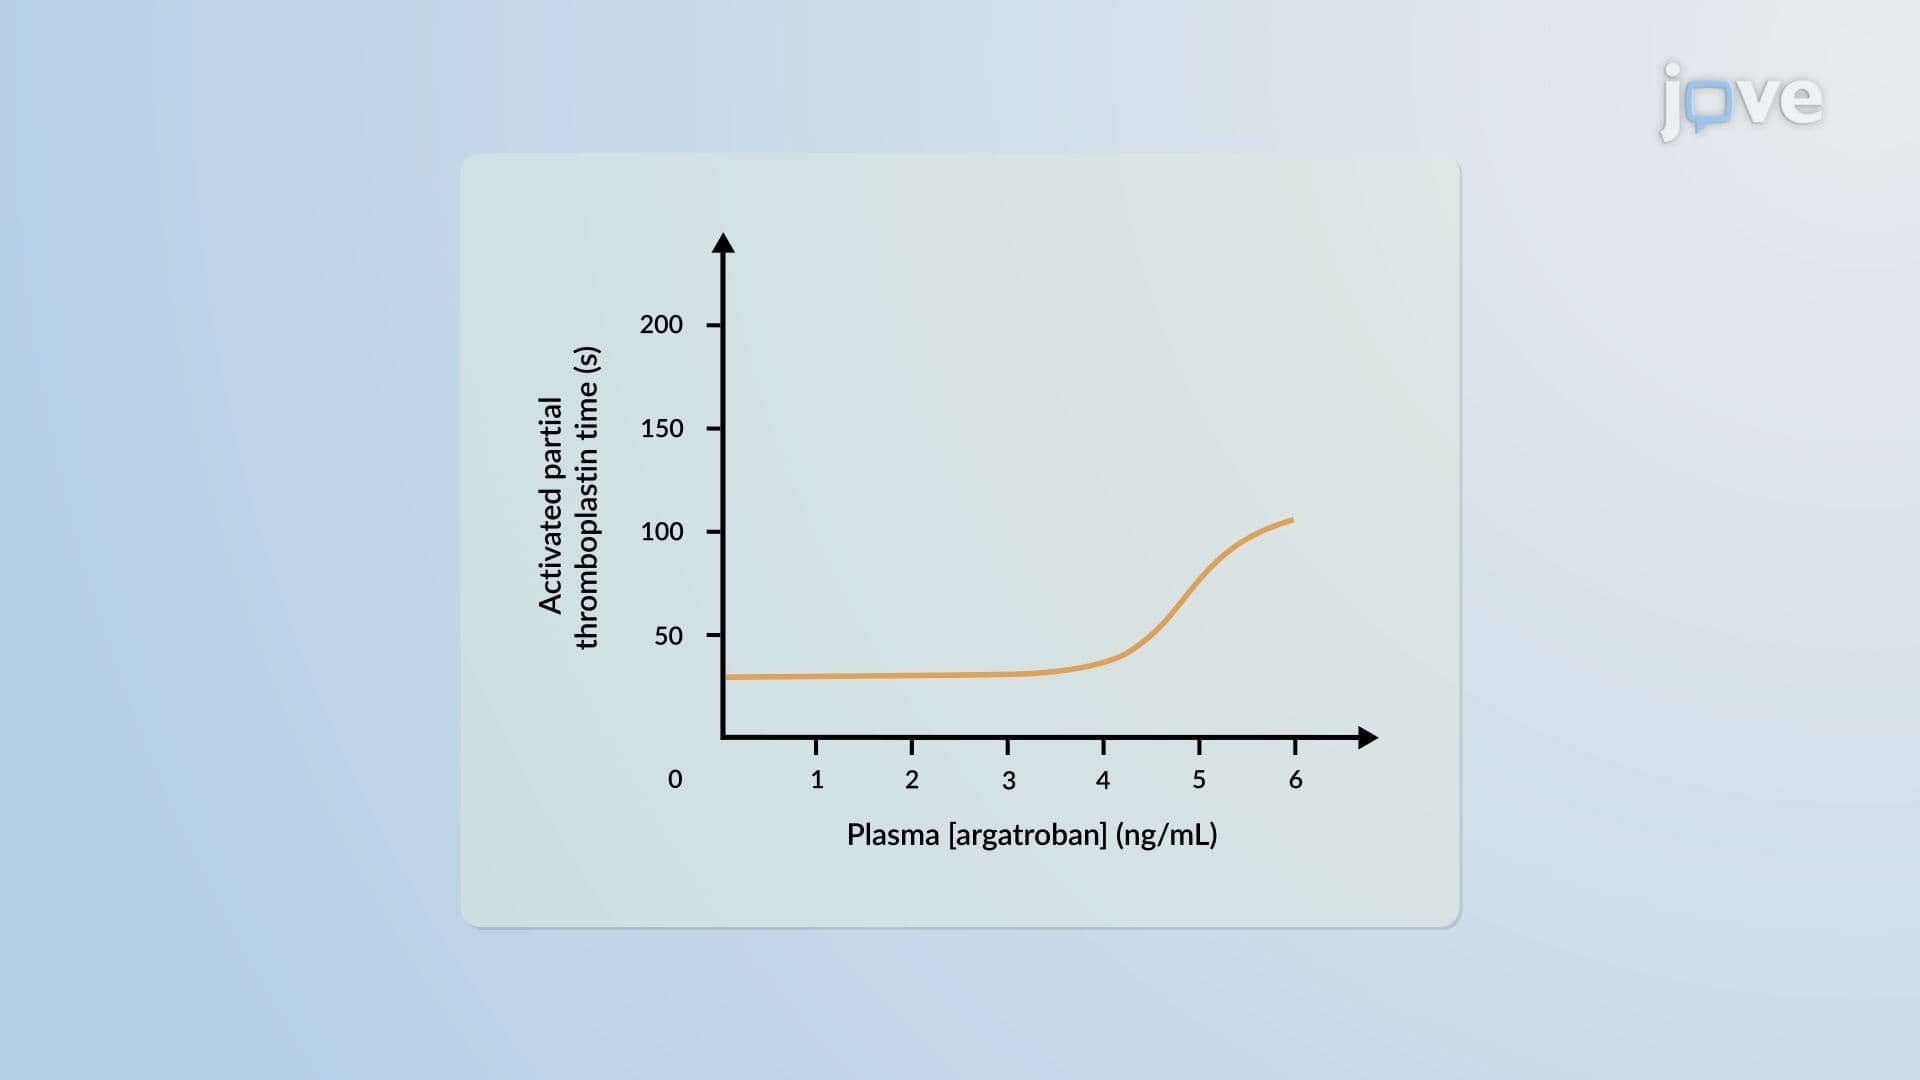
Pharmacodynamic Models: Direct Effect Model and Indirect Response Model
 01:15
Impact of Pharmacokinetic–Pharmacodynamic Models: Regulatory Decisions
 01:24
Pharmacokinetic–Pharmacodynamic Relationship: Problems
 01:27
Pharmacodynamic Models: Overview