Related Experiment Video
Updated: Jun 27, 2026
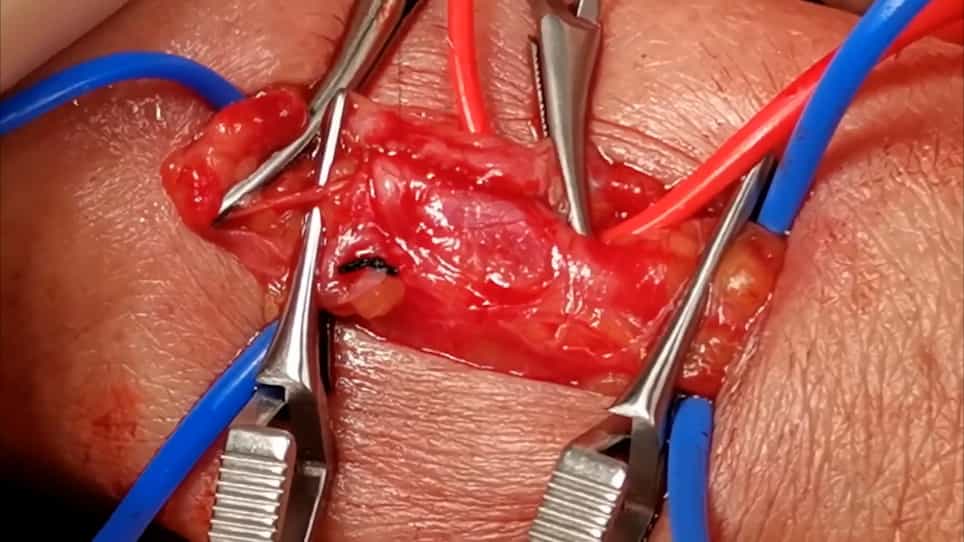

Creating Radio-cephalic Arteriovenous Fistula in the Forearm with a Modified No-Touch Technique
Published on: April 1, 2022
[Vascular access in the elderly: AVF vs CVC. A comment]
1U.O. Nefrologia e Dialisi, IRCCS Multimedica Holding S.p.A., Via Milanese 300, Sesto San Giovanni, MI, Italy. silvio.bertoli@multimedica.it

Insights
Choosing the best vascular access for elderly hemodialysis patients requires a comprehensive evaluation. Native fistulas are preferred, but permanent central venous catheters (CVCs) may suit specific cases, considering cardiovascular risk.
Area of Science:
- Nephrology
- Vascular Surgery
- Geriatrics
Background:
- Aging population undergoing hemodialysis presents complex vascular access challenges.
- Center-specific practices and increasing use of permanent central venous catheters (CVCs) influence access selection.
- Evolving guidelines (e.g., K-DOQI) impact the timing and choice of vascular access.
Purpose of the Study:
- To determine the optimal vascular access strategy for elderly patients with multiple comorbidities requiring hemodialysis.
- To highlight the importance of a multidisciplinary approach in vascular access selection.
- To evaluate the role of patient-specific factors, including cardiovascular risk, in choosing between fistulas and CVCs.
Main Methods:
- Review of existing literature and clinical audit data (DOPPS, Lombardy).
- Analysis of trends in vascular access utilization, including native fistulas, prosthetic fistulas, and permanent CVCs.
- Emphasis on a global clinical evaluation of the patient.
Main Results:
- Native and prosthetic fistulas are generally superior to CVCs for hemodialysis.
- CVCs offer advantages in specific patient groups, such as those with severe cardiac conditions.
- A multidisciplinary team approach involving nephrologists, vascular surgeons, and interventional radiologists is crucial.
Conclusions:
- Individualized patient assessment, considering renal function and cardiovascular risk, is paramount for selecting the most appropriate vascular access.
- Centers capable of offering diverse access options (fistulas and CVCs) enable optimal nephrologist decision-making.
- The nephrologist plays a central role in managing vascular access within a collaborative team.
Abstract:
The aging population starting hemodialysis treatment raises the question as to which is the best vascular access in an older patient with multiple complications. The center effect is an important element in the choice of a vascular access, as shown by the DOPPS data and by a recent audit held in Lombardy. However, other data show an increase in the use of permanent CVCs in the last years and other factors must be taken into account in this clinical choice. Also the timing of proposing a vascular access to a patient has changed over the years (see K-DOQI 2006 vs 2000). Most of the literature agrees on the strategy of a global clinical evaluation of the patient to decide when to place a vascular access and which type of access to use. Native and prosthetic fistulas are considered superior to CVCs although the latter have certain advantages in selected patients, such as those with severe cardiac problems. The nephrologist has a major role in vascular access management as part of a team made up also by a vascular surgeon and an interventional radiologist. Only in a center where both native and prosthetic fistulas can be constructed and permanent CVCs be placed can a nephrologist choose the most appropriate vascular access for individual patients after evaluation not only of their renal function but their cardiovascular risk as well.


