Related Experiment Video
Updated: Jun 27, 2026
Implementing Patch Clamp and Live Fluorescence Microscopy to Monitor Functional Properties of Freshly Isolated PKD Epithelium
Published on: September 1, 2015
Chronic renal failure in a boy with classic Bartter's syndrome due to a novel mutation in CLCNKB coding for the
Chien-Ming Lin1, Jeng-Daw Tsai, Yi-Fen Lo
1Department of Pediatrics, Tri-Service General Hospital, National Defense Medical Center, Taipei, Taiwan.

Background:
Progressive renal failure in patients with classic Bartter's syndrome (cBS) due to inactivating mutations in CLCNKB gene is extraordinarily rare.
Discussion:
We describe a 17-year-old Chinese boy who presented with progressive muscle weakness and renal failure. He was diagnosed as BS of unknown type at the age of 9 months and treated with indomethacin (2 mg/kg/day) and potassium chloride (KCl) supplementation (1.5 mEq/kg/day) for hypokalemia (2.5 mmol/l). At the age of 12 years, serum K+ was 3.0 mmol/l and creatinine reached 2.0 mg/dl. On admission, his blood pressure was normal but volume status was depleted. Urinalysis was essentially normal. Biochemical studies showed hypokalemia (K+ 2.4 mmol/l) with a high transtubular K+ gradient (TTKG) 9.6, metabolic alkalosis (HCO3- 28.4 mmol/l), normomagnesemia (2.0 mg/dl), severe renal failure (BUN 94 mg/dl, Cr 6.3 mg/dl), and hypocalciuria (urine calcium/creatinine ratio 0.02 mg/mg). Abdominal sonography revealed bilateral small size kidneys without nephrocalcinosis or renal stones. After the withdrawal of indomethacin with regular KCl and adequate fluid supplementation for 1 year, serum creatinine and K+ levels have been maintained at 4.0 mg/dl and 3.3 mmol/l, respectively. Direct sequencing of NKCC2, ROMK, ClC-Kb, and NCCT in this patient disclosed a novel homozygous missense mutation (GGG to GAG, G470E) in CLCNKB. This G470E mutation was not identified in 100 healthy Chinese subjects. Long-term therapy of non-steroidal anti-inflammatory drugs (NSAIDs), prolonged hypokalemia, chronic volume depletion, and underlying genetic variety may contribute to the deterioration of his renal function. The cautious use of NSAIDs, aggressive correction of hypokalemia, and avoidance of severe volume depletion may prevent the irreversible renal damage in patients with BS due to a Cl- channel defect.
More Related Videos
 09:40
Isolation, Characterization, And High Throughput Extracellular Flux Analysis of Mouse Primary Renal Tubular Epithelial Cells
Published on: June 20, 2018
 08:50
5/6th Nephrectomy in Combination with High Salt Diet and Nitric Oxide Synthase Inhibition to Induce Chronic Kidney Disease in the Lewis Rat
Published on: July 3, 2013
Related Concept Videos
 01:24
Renal Tubule and Collecting Duct
Proximal Convoluted Tubule (PCT):
The PCT is the initial segment of the renal tubule, extending from the Bowman's capsule that encloses the glomerulus. Its convoluted structure and microvilli-lined cells increase the surface area for reabsorption. The PCT reabsorbs glucose, amino acids, sodium, and water from the filtrate, ensuring essential...
 01:25
Chronic Kidney Disease I: Introduction
 01:10
Nephrons
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:22
Physiology of the Genitourinary System II: Tubular Reabsorption and Secretion
 01:29
Renal Regulation of Acid-Base Balance
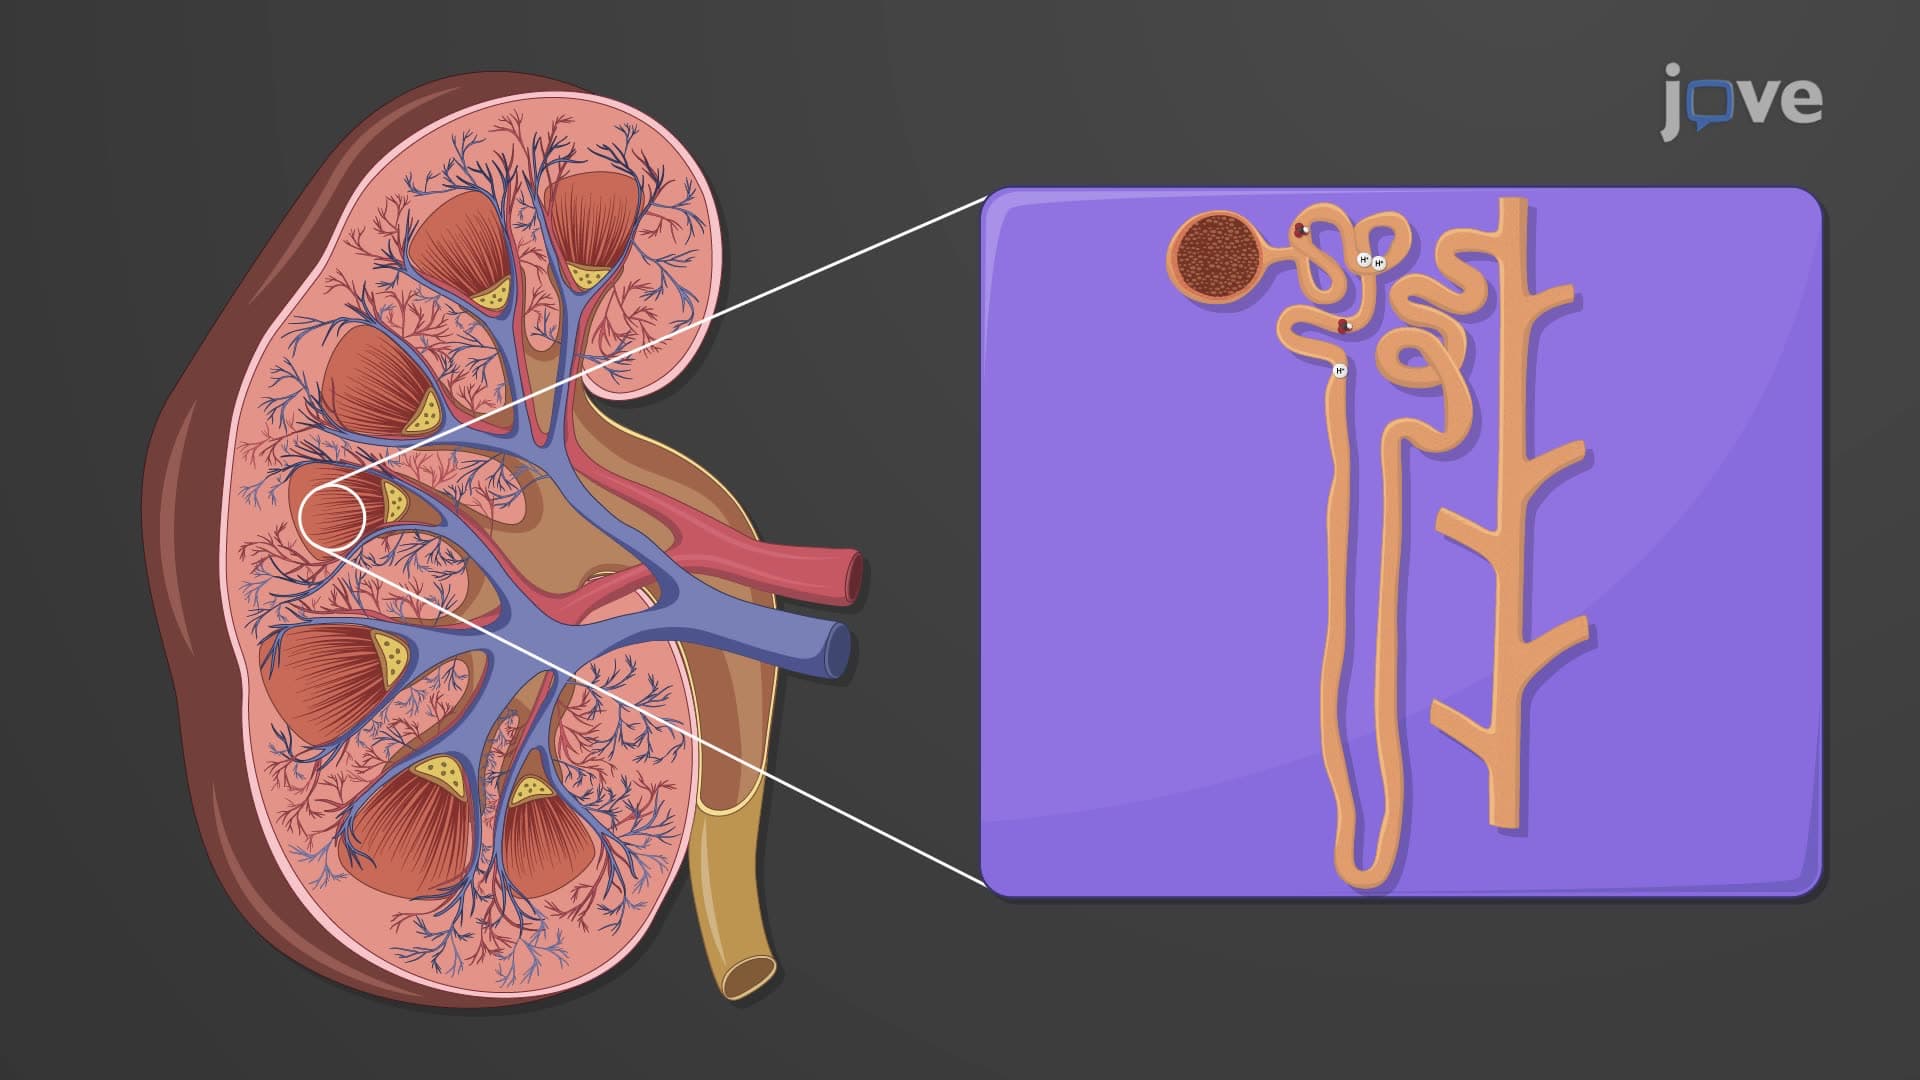
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...