Related Experiment Video
Updated: Jun 27, 2026
Assessment of Sarcoplasmic Reticulum Calcium Reserve and Intracellular Diastolic Calcium Removal in Isolated Ventricular Cardiomyocytes
Published on: September 18, 2017
High-dose adenosine overcomes the attenuation of myocardial perfusion reserve caused by caffeine
Eliana Reyes1, Chee Y Loong, Mark Harbinson
1National Heart and Lung Institute, Imperial College London, United Kingdom. e.reyes@rbht.nhs.uk

Objectives:
We studied whether an increase in adenosine dose overcomes caffeine antagonism on adenosine-mediated coronary vasodilation.
Background:
Caffeine is a competitive antagonist at the adenosine receptors, but it is unclear whether caffeine in coffee alters the actions of exogenous adenosine, and whether the antagonism can be surmounted by increasing the adenosine dose.
Methods:
Myocardial perfusion scintigraphy (MPS) was used to assess adenosine-induced hyperemia in 30 patients before (baseline) and after coffee ingestion (caffeine). At baseline, patients received 140 microg/kg/min of adenosine combined with low-level exercise. For the caffeine study, 12 patients received 140 microg/kg/min of adenosine (standard) and 18 patients received 210 microg/kg/min (high dose) after caffeine intake (200 mg). Myocardial perfusion was assessed semiquantitatively and quantitatively, and perfusion defect was characterized according to the presence of reversibility.
Results:
Caffeine reduced the magnitude of perfusion abnormality induced by standard adenosine as measured by the summed difference score (SDS) (12.0 +/- 4.4 at baseline vs. 4.1 +/- 2.1 after caffeine, p < 0.001) as well as defect size (18% [3% to 38%] vs. 8% [0% to 22%], p < 0.01), whereas it had no effect on the abnormalities caused by high-dose adenosine (SDS, 7.7 +/- 4.0 at baseline vs. 7.8 +/- 4.2 after caffeine, p = 0.7). There was good agreement between baseline and caffeine studies for segmental defect category (kappa = 0.72, 95% confidence interval: 0.65 to 0.79) in the high-dose group. An increase in adenosine after caffeine intake was well tolerated.
Conclusions:
Caffeine in coffee attenuates adenosine-induced coronary hyperemia and, consequently, the detection of perfusion abnormality by adenosine MPS. This can be overcome by increasing the adenosine dose without compromising test tolerability.

Related Concept Videos
 01:25
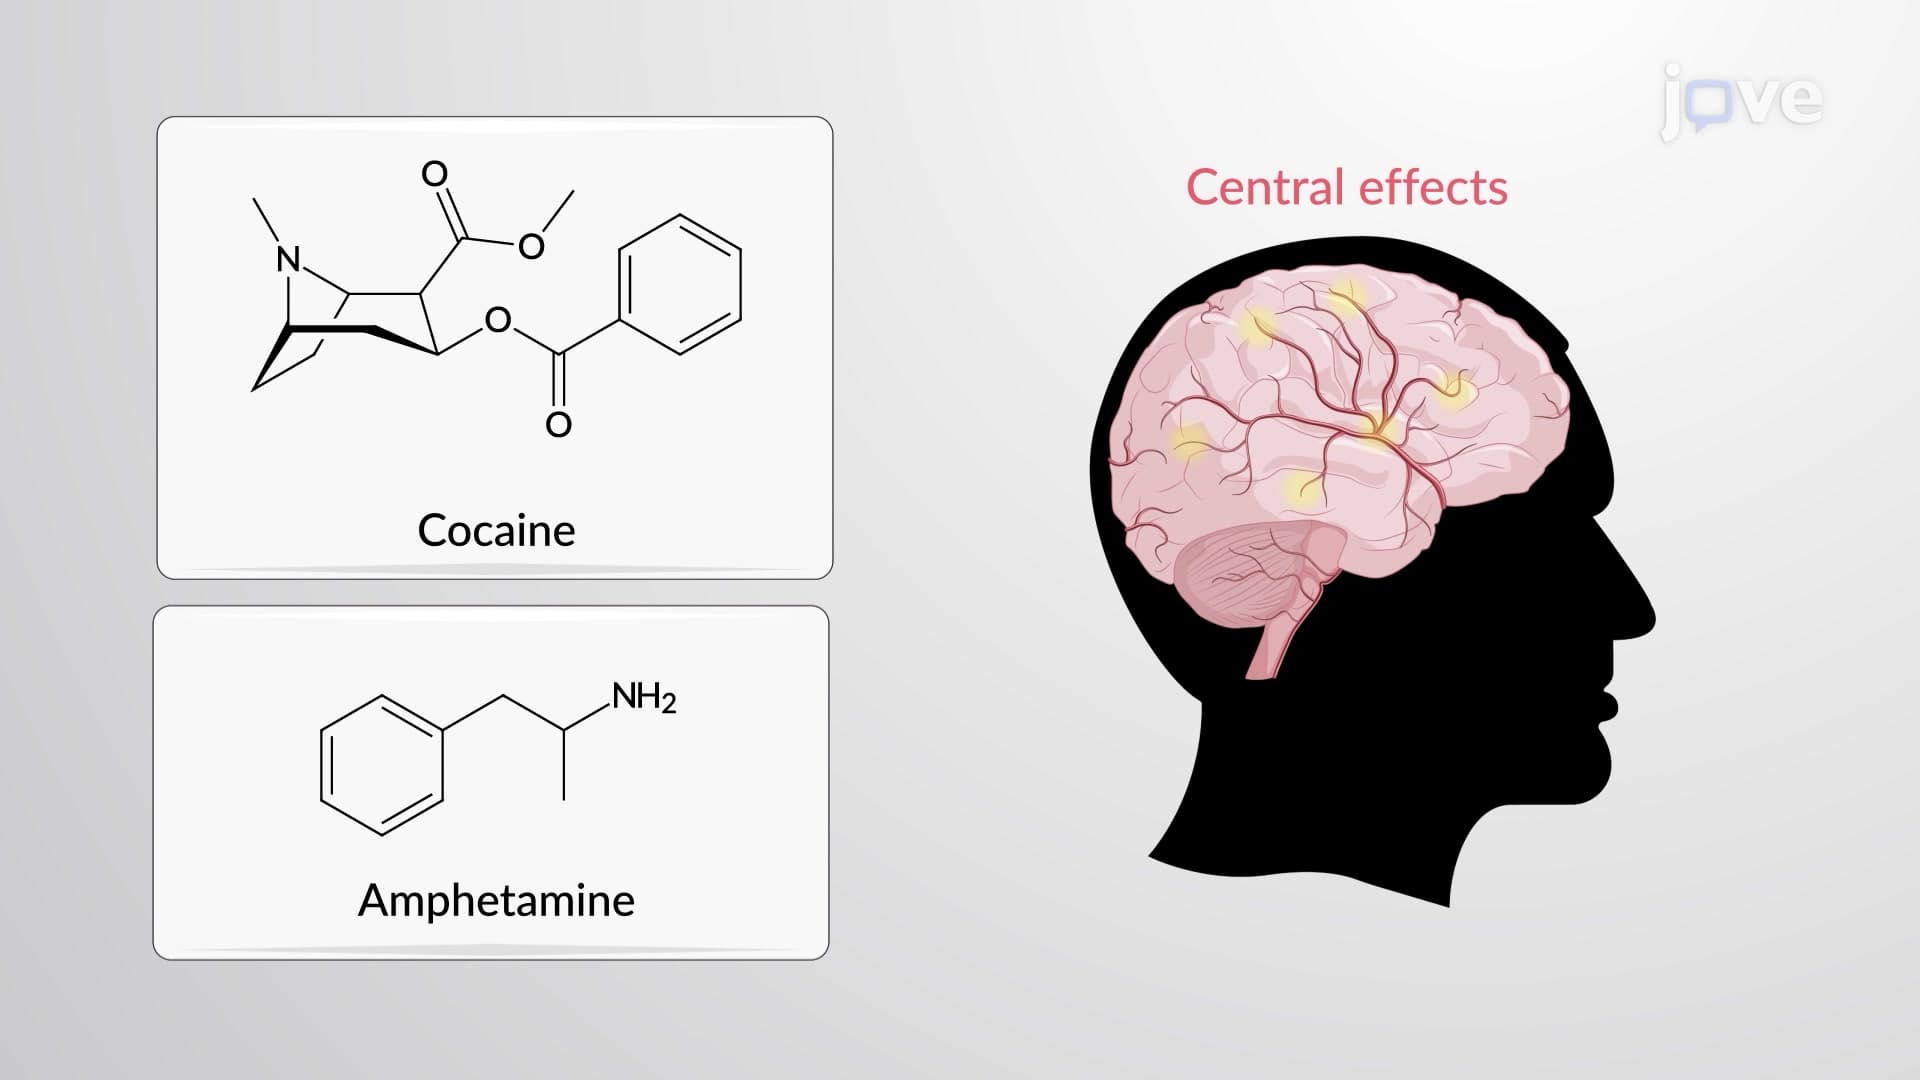
Adrenergic Agonists: Indirect-Acting Agents
One mechanism involves depleting stored catecholamines by displacing them from synaptic vesicles. These agents, known as "displacers," are transported into vesicles at the expense of noradrenaline. Examples include amphetamine and tyramine, which lack a catechol moiety, resulting in prolonged action, improved oral bioavailability, and...
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:22
Heart Failure Drugs: β-Blockers
 01:28
Adrenergic Agonists: Mixed-Action Agents
Ephedrine and pseudoephedrine lack a catecholamine group, making them less susceptible to degradation by metabolic enzymes. They have increased oral bioavailability and lipophilicity, resulting in a longer duration of action. Their response is reduced by...
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System