Related Experiment Videos
Measurement of surgical wait times in a universal health care system
Jun Kawakami1, Wilma M Hopman, Rachael Smith-Tryon
1Assistant Professor, Department of Urology.

Introduction:
Reported increases in surgical wait times for cancer have intensified the focus on this quality of health care indicator and have created a very public, concerted effort by providers to decrease wait times for cancer surgery in Ontario. Delays in access to health care are multifactorial and their measurement from existing administrative databases can lack pertinent detail. The purpose of our study was to use a real-time surgery-booking software program to examine surgical wait times at a single centre.
Methods:
The real-time wait list management system Axcess.Rx has been used exclusively by the department of urology at the Kingston General Hospital to book all nonemergency surgery for 4 years. We reviewed the length of time from the decision to perform surgery to the actual date of surgery for patients in our group urological practice. Variables thought to be potentially important in predicting wait time were also collected, including the surgeon's assessment of urgency, the type of procedure (i.e., diagnostic, minor cancer, major cancer, minor benign, major benign), age and sex of the patient, inpatient versus outpatient status and year of surgery. Analysis was planned a priori to determine factors that affected wait time by using multivariate analysis to analyze variables that were significant in univariate analysis.
Results:
There were 960 operations for cancer and 1654 for benign conditions performed during the evaluation period. The overall mean wait time was 36 days for cancer and 47 days for benign conditions, respectively. The mean wait time for cancer surgery reached a nadir in 2004 at 29.9 days and subsequently increased every year, reaching 56 days in 2007. In comparison, benign surgery reached a nadir wait time of 33.7 days in 2004 and in 2007 reached 74 days at our institution. Multivariate analysis revealed that the year of surgery was still a significant predictor of wait time. Urgency score, type of procedure and inpatient versus outpatient status were also predictive of wait time.
Conclusion:
The application of a prospectively collected data set is an effective and important tool to measure and subsequently examine surgical wait times. This tool has been essential to the accurate assessment of the effect of resource allocation on wait times for priority and nonpriority surgical programs within a discipline. Such tools are necessary to more fully assess and follow wait times at an institution or across a region.
Related Concept Videos
 00:58
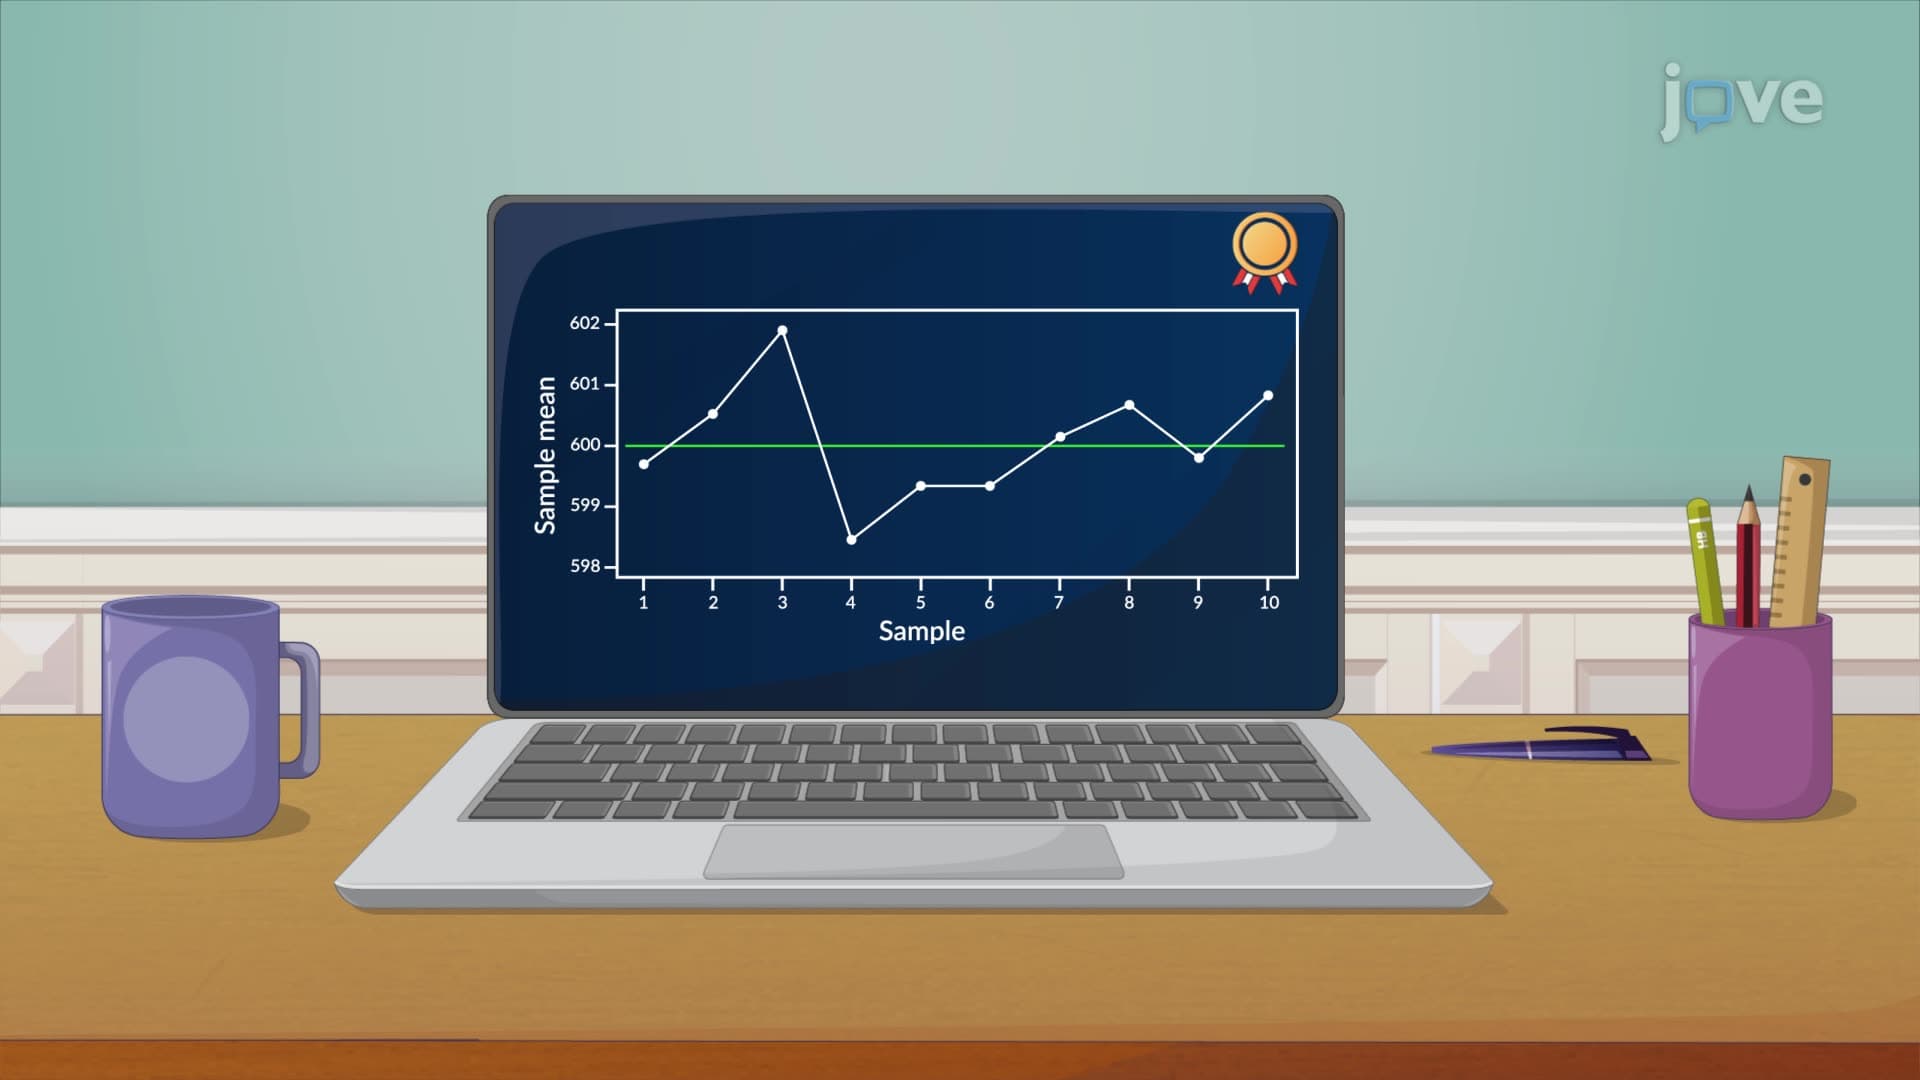
The X̄ Chart
The x̄ chart, often known as the individual control chart, is a crucial tool in statistical process control. It is designed to monitor process behavior and performance over time and is widely used in various industries to ensure that processes are operating at their optimum capacity and within specified limits.
A x̄ chart is constructed by plotting individual measurements of a quality characteristic in the order in which...
 01:26
Methods Of Healthcare Delivery System
Managed Care System:
The managed care system is designed to control the cost while maintaining the quality of care. The patient's care from admission to discharge is planned by the primary care provider or the case manager, also known as the gatekeeper. In a managed care system, the number of care providers is limited...
 01:18
Introduction To Survival Analysis
The primary goal of survival analysis is to estimate survival time—the time until a...
 01:18
Introduction To Health Care Delivery System
The Institute of Medicine (IOM) advocates for a patient-centered, effective, safe, timely, equitable, and effective healthcare system. The National Priorities...
 01:26
Traditional Level Of Health Care System
The preventive healthcare service includes tests for screening. Preventive health care services include identifying and reducing disease risk...
 01:11
Secondary Healthcare System