Related Experiment Video
Updated: Jun 27, 2026


Characterization of Sickling During Controlled Automated Deoxygenation with Oxygen Gradient Ektacytometry
Published on: November 5, 2019
Glucose-6-phosphate dehydrogenase deficiency and sickle cell disease in Burkina Faso
Jacques Simpore1, Denise Ilboudo, Karou Damintoti
1Centre Medical Saint Camille, 01 BP 364 Ouagadougou 01, Burkina Faso, Italy.

Where malaria is endemic, there is an unexpected association between haemoglobinopathies and glucose-6-phosphate dehydrogenase (G-6-PD) deficiency. Their coexistence in a patient with sickle cell disease (SCD) can lead to hemolytic anemia, hemoglobinuria, sepsis, renal failure and vaso-occlusive attacks (VOA). The aim of this research was to determine the impact of G-6-PD deficiency in SCD patients. That is why, we screened haemoglobinopathies and G-6-PD deficiency in 7 villages and at 10 primary schools in Kadiogo Province, Burkina Faso. Hemoglobin electrophoresis was performed on blood from 18,383 people. From these results, we chose 342 subjects for a hemogram and the measure of the G-6-PD activity. The results were analyzed with Epilnfo-6 and Spss-10. Statistical significance was set at p < 0.05. We found a prevalence of 28.9% of Sickle Cell Trait (SCT), 1.3% of Major Sickle Cell Syndromes (MSCS), 12.3% of G-6-PD deficiency among women and 20.5% among men. We did not detect a statistically significant difference for counts of erythrocytes (p = 0.773), leucocytes (p = 0.227) and reticulocytes (0.292); hemoglobin levels (p = 0.998); annual vasoocclusive attacks (p = 0.869) between persons with SCD having a G-6-PD deficiency and those with normal G-6-PD activity. According to this study, G-6-PD deficiency does not seem to increase the severity of SCD. However, these patients should know their G-6-PD genotype in order to avoid consuming oxidative drugs that might provoke oxidative stress.
Where malaria is endemic, there is an unexpected association between haemoglobinopathies and glucose-6-phosphate dehydrogenase (G-6-PD) deficiency. Their coexistence in a patient with sickle cell disease (SCD) can lead to hemolytic anemia, hemoglobinuria, sepsis, renal failure and vaso-occlusive attacks (VOA). The aim of this research was to determine the impact of G-6-PD deficiency in SCD patients. That is why, we screened haemoglobinopathies and G-6-PD deficiency in 7 villages and at 10 primary schools in Kadiogo Province, Burkina Faso. Hemoglobin electrophoresis was performed on blood from 18,383 people. From these results, we chose 342 subjects for a hemogram and the measure of the G-6-PD activity. The results were analyzed with Epilnfo-6 and Spss-10. Statistical significance was set at p < 0.05. We found a prevalence of 28.9% of Sickle Cell Trait (SCT), 1.3% of Major Sickle Cell Syndromes (MSCS), 12.3% of G-6-PD deficiency among women and 20.5% among men. We did not detect a statistically significant difference for counts of erythrocytes (p = 0.773), leucocytes (p = 0.227) and reticulocytes (0.292); hemoglobin levels (p = 0.998); annual vasoocclusive attacks (p = 0.869) between persons with SCD having a G-6-PD deficiency and those with normal G-6-PD activity. According to this study, G-6-PD deficiency does not seem to increase the severity of SCD. However, these patients should know their G-6-PD genotype in order to avoid consuming oxidative drugs that might provoke oxidative stress.
Related Concept Videos
 01:27
Glucose Transporters
Facilitated diffusion-glucose transporters (GLUTs) are encoded by the solute-linked carrier (SLC) family 2, subfamily A gene family, or SLC2A. The 14 GLUT protein members are distributed into three classes:
 01:20
Inborn Errors of Metabolism
 01:21
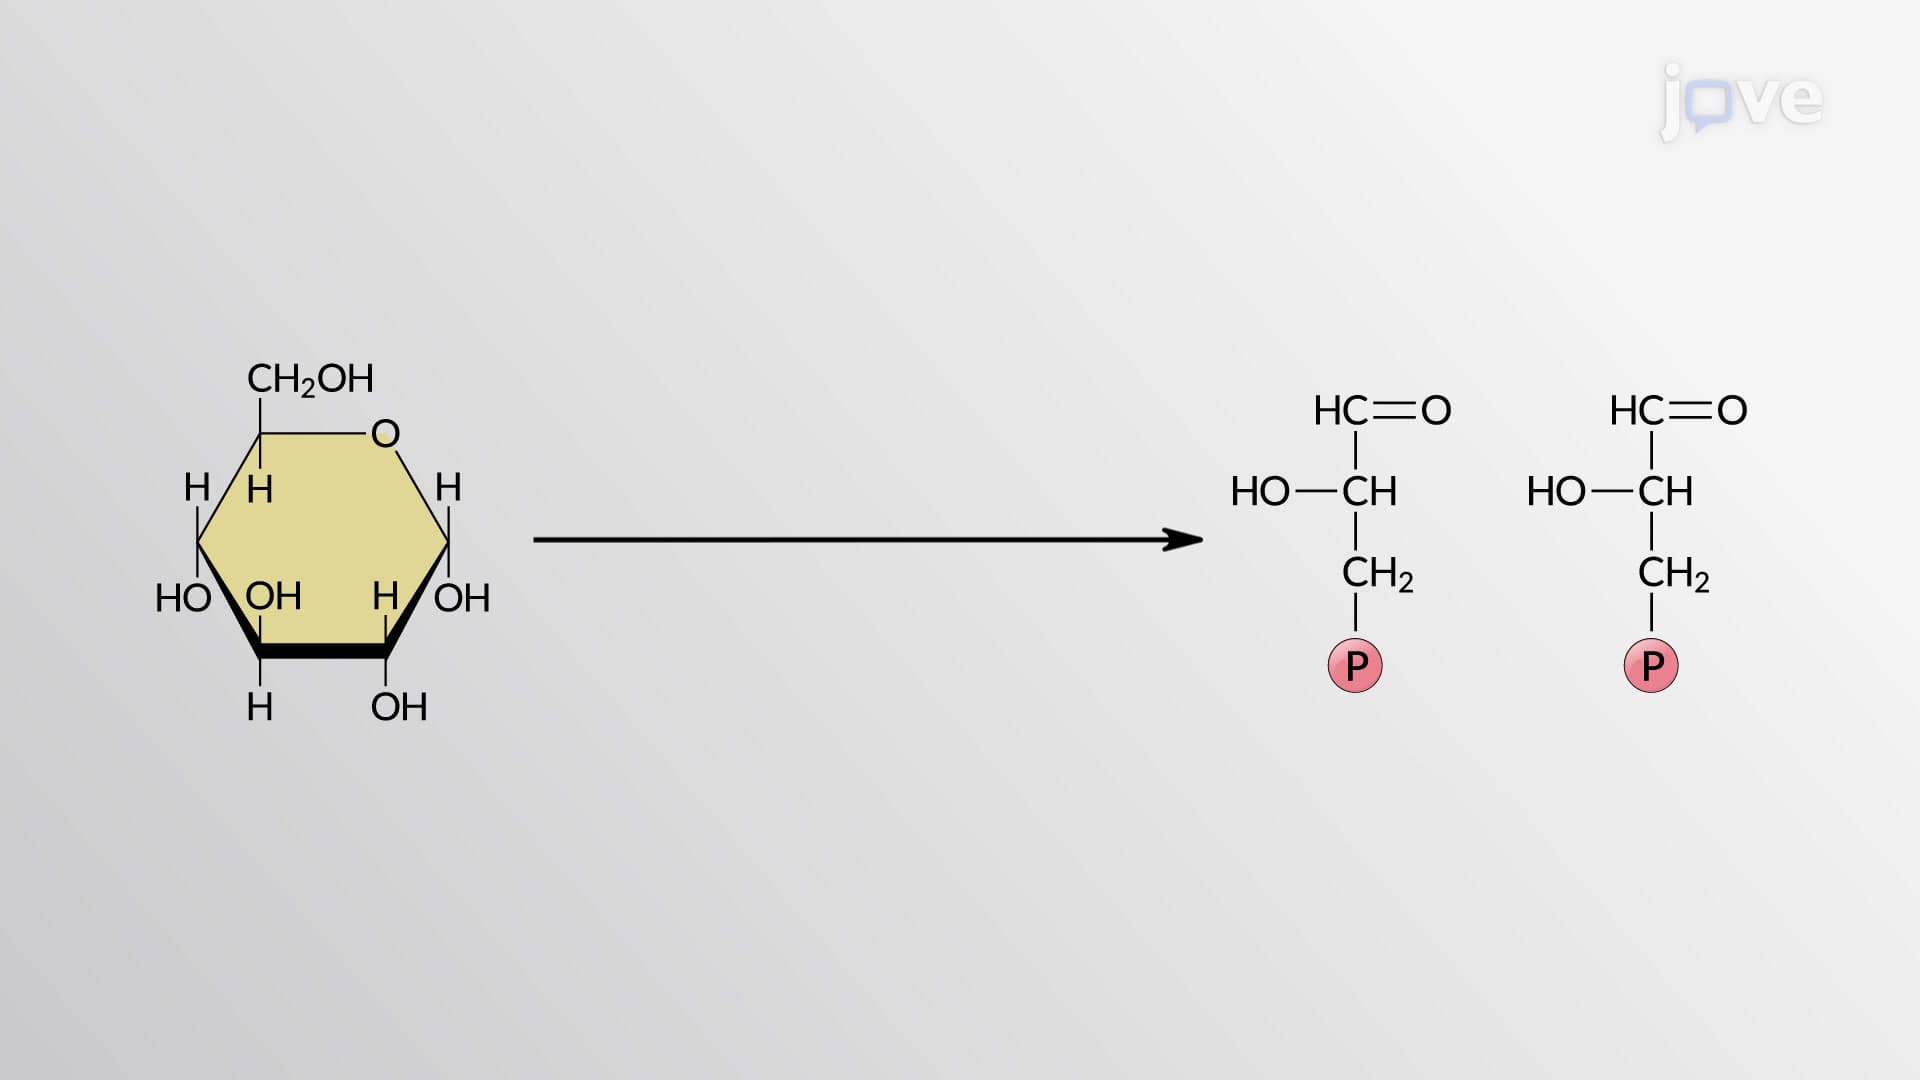
Glycolysis: Preparatory Phase
 01:49
Multiple Allele Traits
 01:24
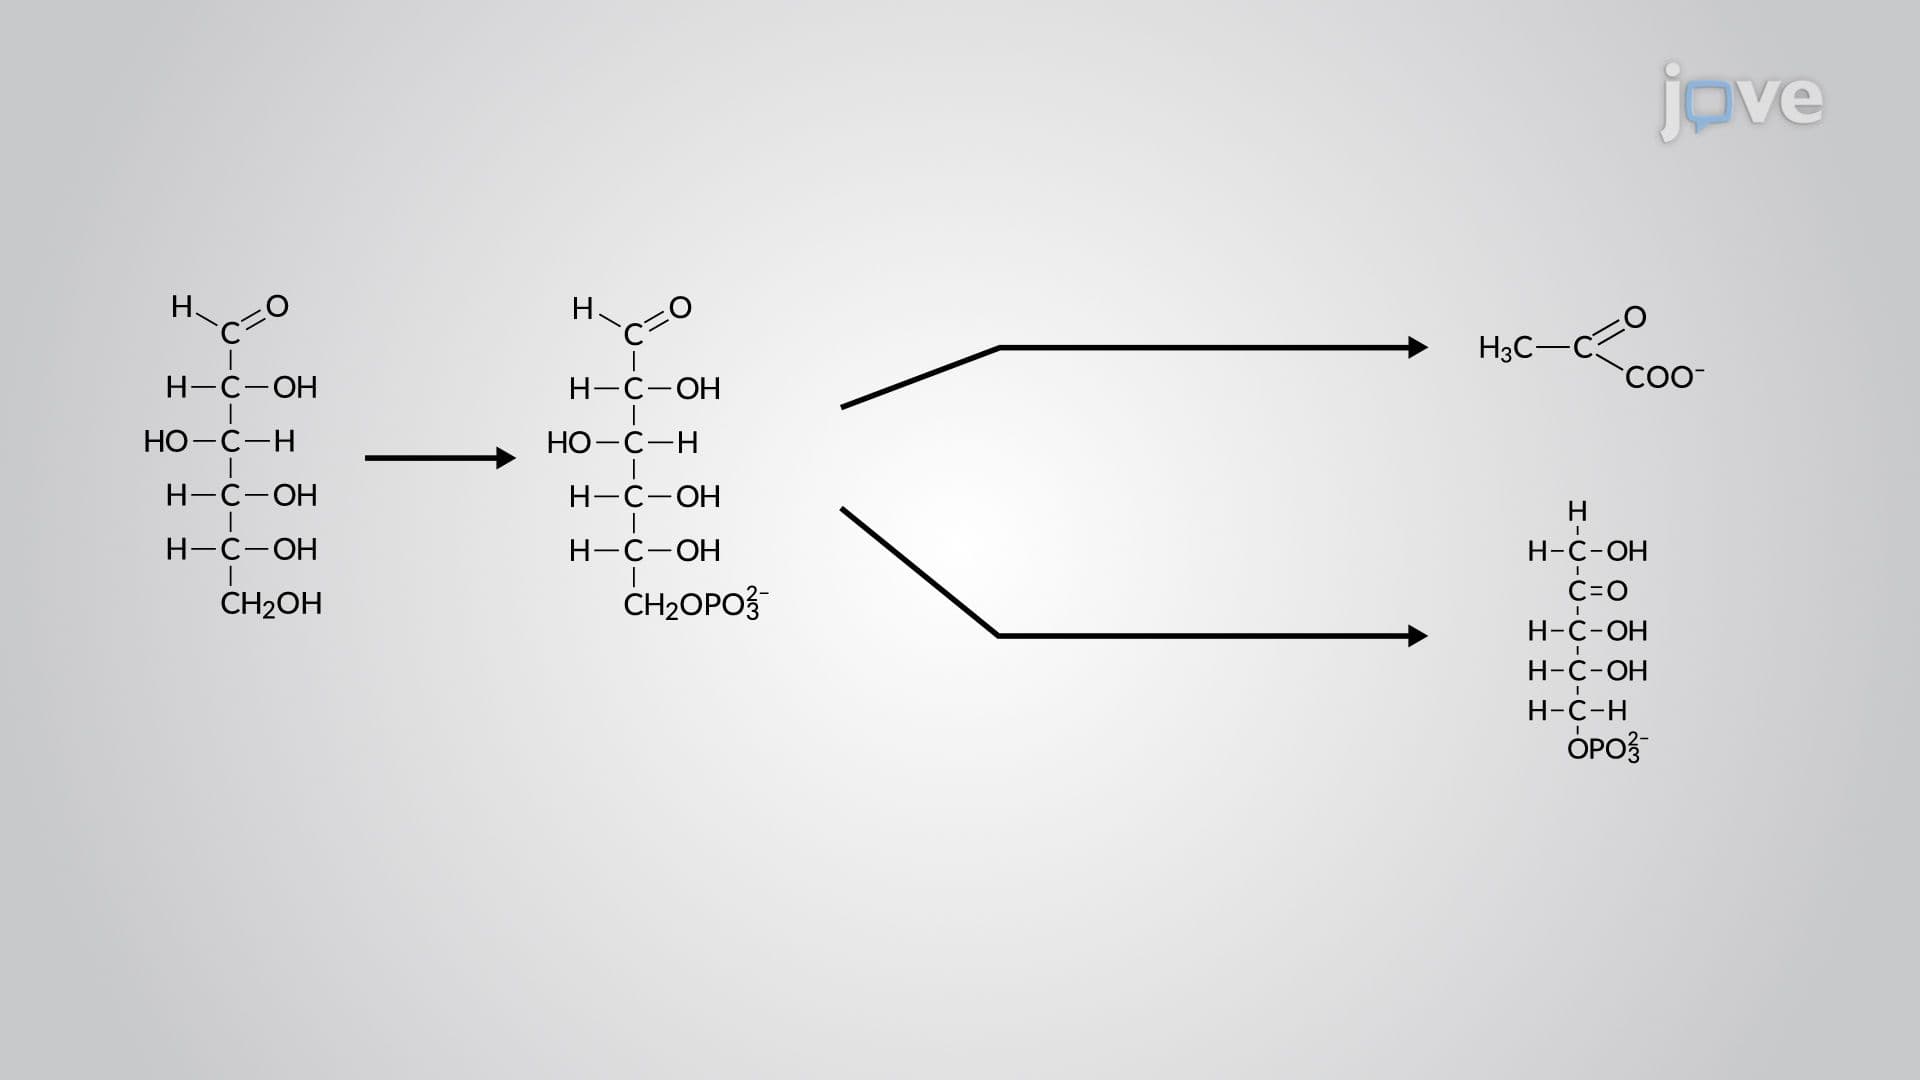
Other Glycolytic Pathways
 01:20
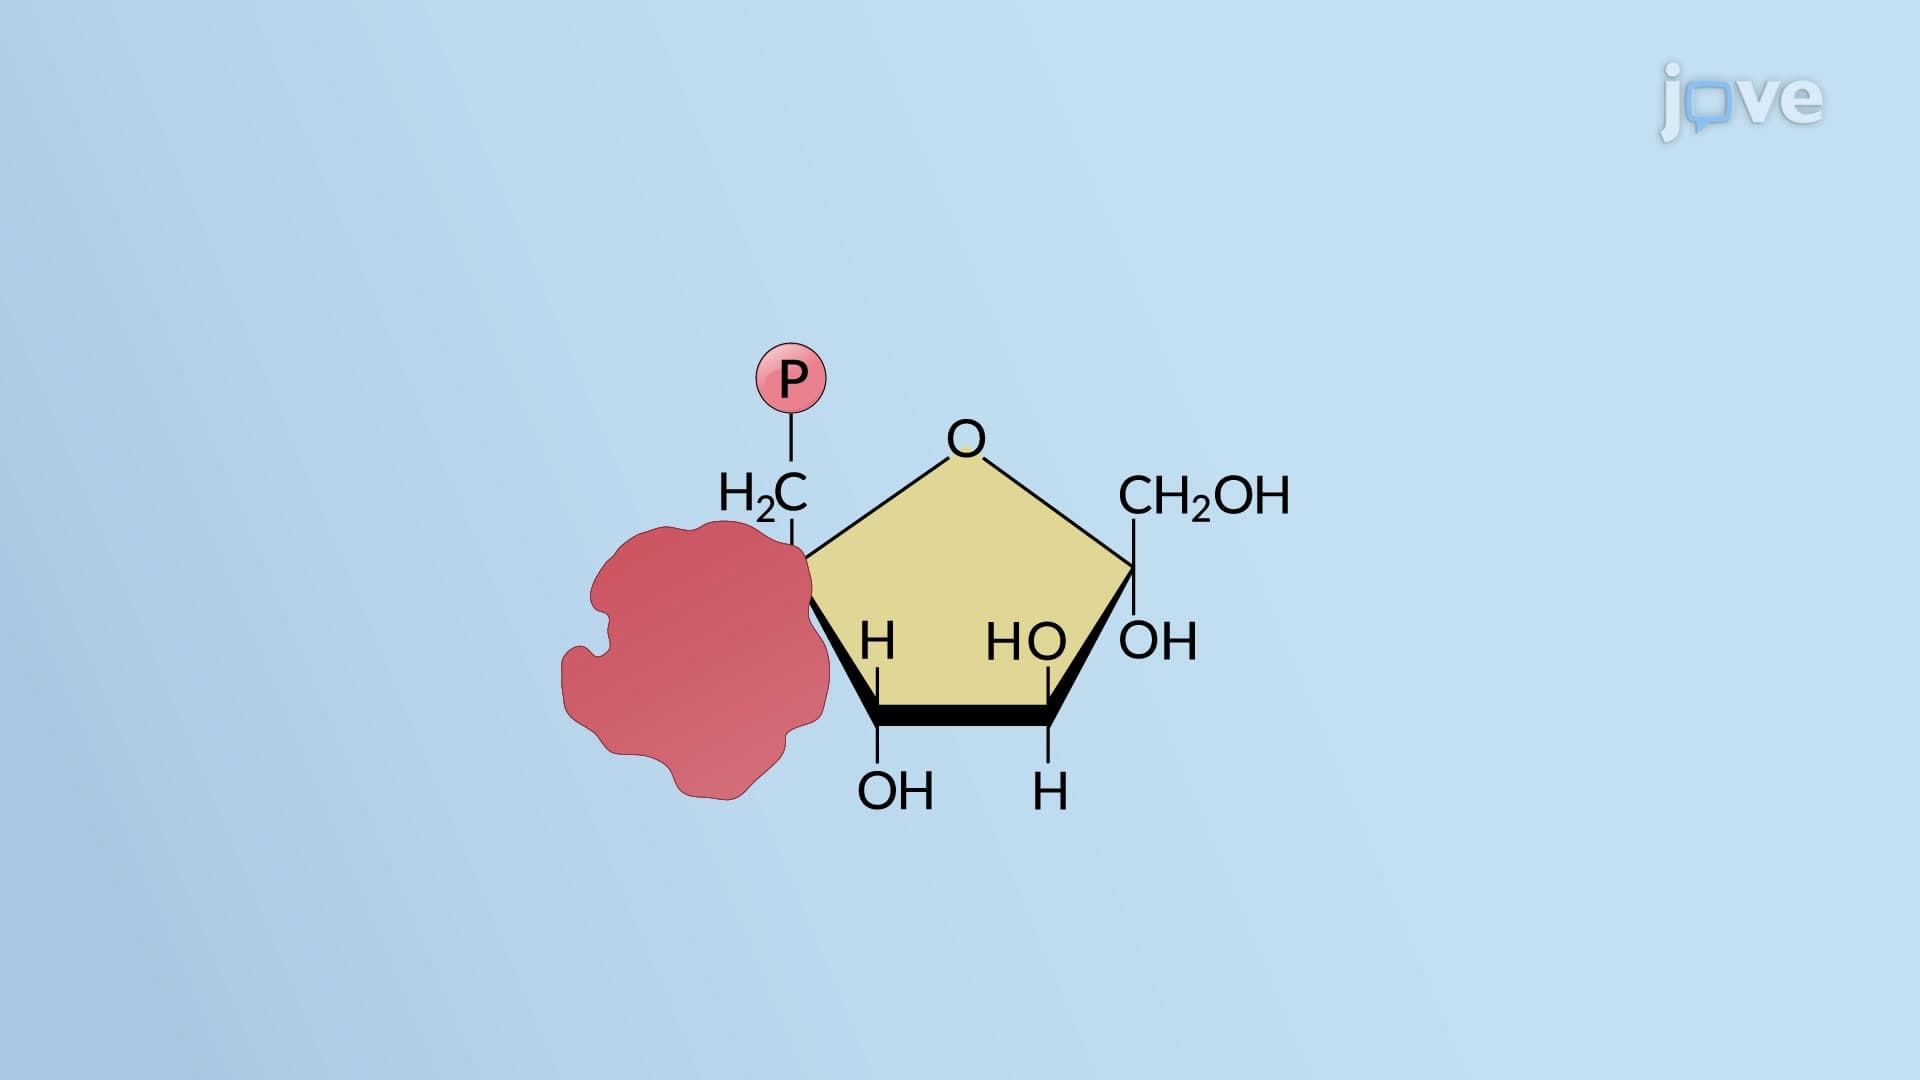
Energy-requiring Steps of Glycolysis