Related Experiment Video
Updated: Jun 27, 2026


Murine Distal Colostomy, A Novel Model of Diversion Colitis in C57BL/6 Mice
Published on: July 12, 2018
How to treat diversion colitis?--Current state of medical knowledge, own research and experience
M Szczepkowski1, A Kobus, K Borycka
1Bielañski Hospital, Department of General Surgery, Warsaw, Poland.

Abstract:
The aim of this study was to present current knowledge about a nospecific inflammation of mucosa within segments of colon excluded from normal bowel passage called as a "diversion colitis" (DC) and to try to determine the role of factors which might modify the clinical course of DC. We also unswered the question; how to treat DC: conservatively or surgically? Our own experience with DC concerns 145 patents (which is most numerous and well exactly examined series presented in literature). In the group of patients studied, clinical signs of DC were present in over 70% of patients (early signs were low abdominal pain and tenesmus, while anal oozing appeared later). Predominating endoscopic features of DC in the group of patients studied were: a. blurring of vascular pattern (in app. 90% of patients); b. contact bleeding (in app. 80% of patients); c. mucosal oedema (in app. 60% of patients). Results of own observations and literature data indicate, that morphologic alterations in the segment of bowel excluded from normal passage are probably vasogenic consisting in atrophy and inflammation of the allergic type (this would confirm the theory about vascular etiology of DC). In our material, we have not noticed any trend toward hyperproliferation or dysplasia in the excluded segment of colon, supporting the thesis that these disturbances are largely reversible. Clinical pathology of DC does not depend on age, sex, cause and type of surgical procedure performed, mode of surgery or concomitant diseases. Authors suggested an alternative algorithm of diagnostic work-up in patients suspected of DC, and proposed that patients with a segment of bowel excluded from normal passage be subdivided into three groups: 1. Patients with no clinical, endoscopic nor morphologic signs of DC. 2. Patients with moderate signs of DC. 3. Patients with severe signs of DC. Patients in the group 1 should remain under continuous specialised supervision, because they are at risk of developing DC, while patients in the groups 2 and 3 should undergo surgical restoration of bowel continuity. This applies particularly to group 3, where indications for surgery do not stem from risk of hyperproliferation, dysplasia or malignant transformation, but from that of a massive inflammation, which may constitute a danger for patientis health and even life. Authors also underline that DC can be treated conservatively but the best and most successful and remained method of treatment of DC is the operation of decolostomy, which means restoration continuity of digestive tract.


Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
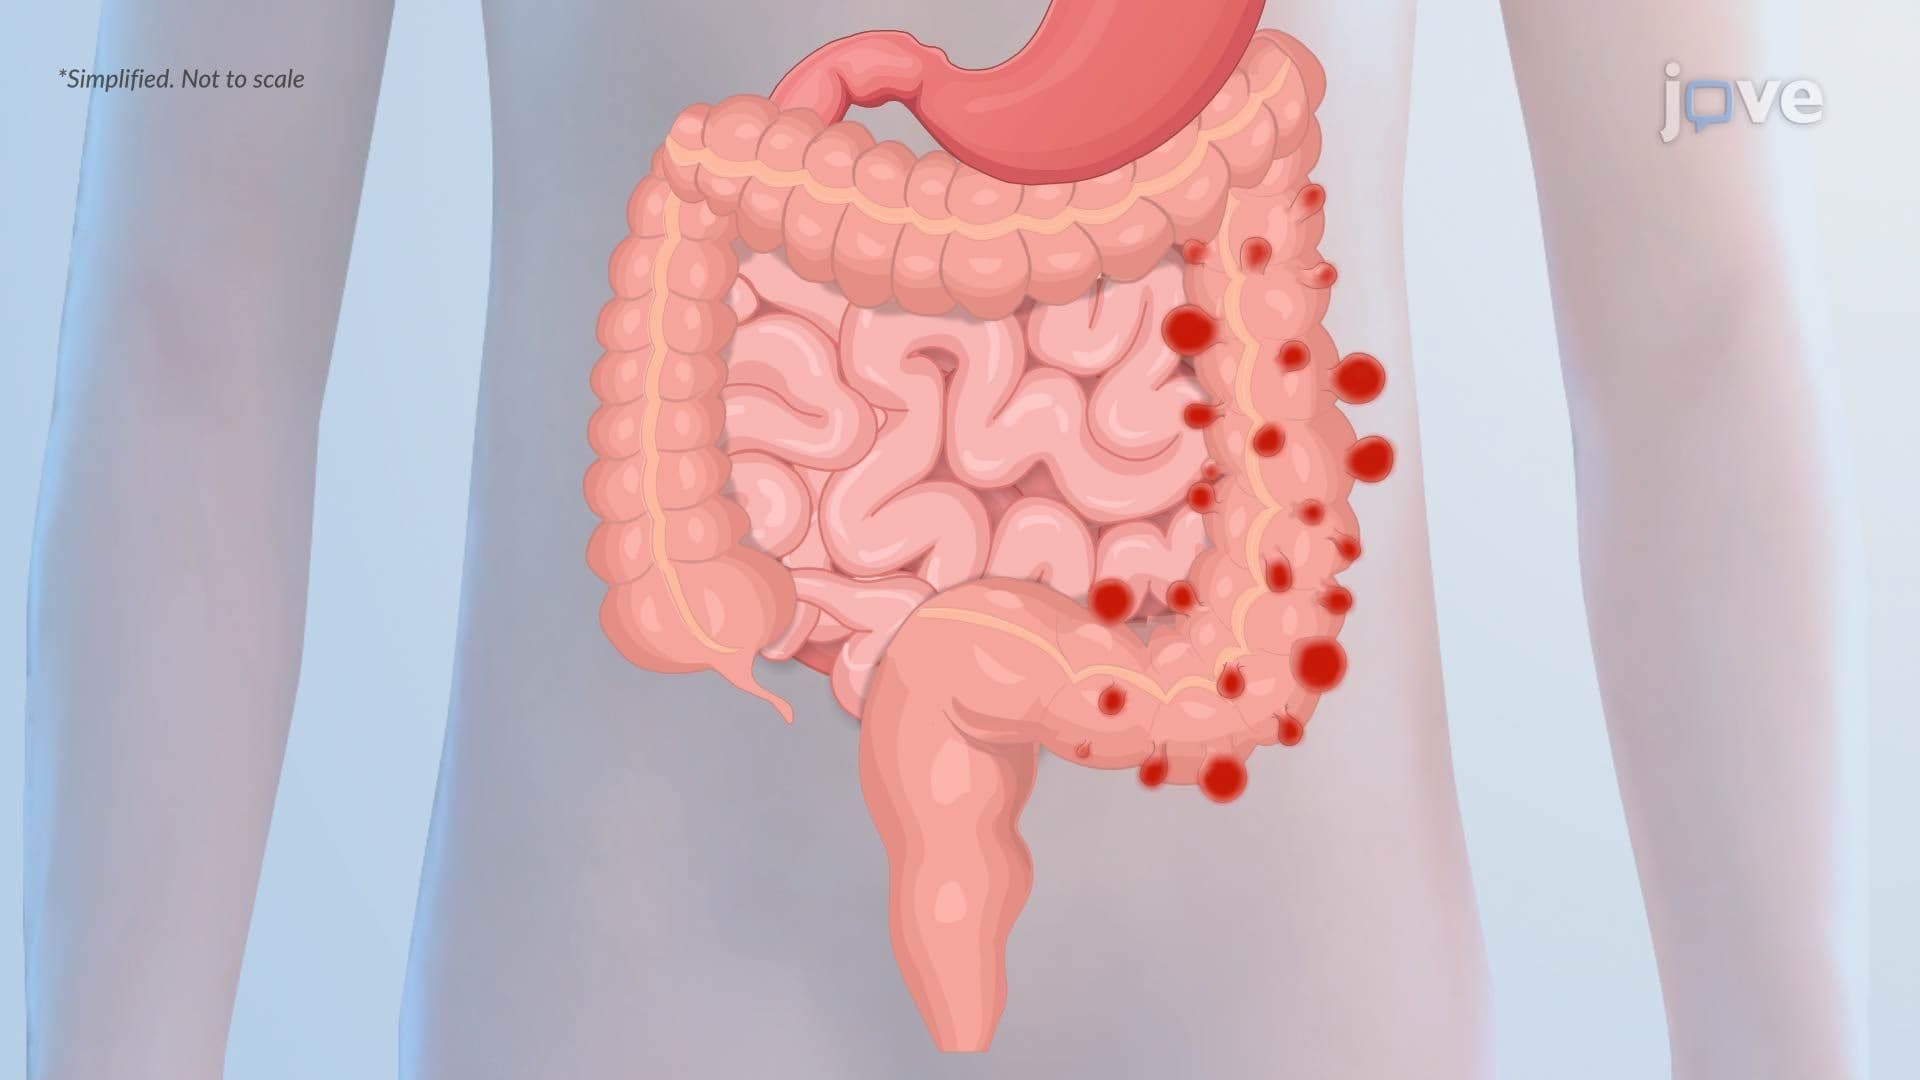
Here are some common surgical interventions for IBD:
 01:27
Diverticular Disease of the Colon
 01:30
Inflammatory Bowel Disease III: Diagnostic Studies and Management I-Nutritional Therapy
Diagnostic studies
A colonoscopy is the definitive screening test, distinguishing ulcerative colitis from other colon diseases with similar symptoms. During a colonoscopy test, inflamed mucosa with exudate ulcerations can be observed, and biopsies are taken to determine the histologic characteristics of the colonic...
 01:29
Drugs for Treatment of Ulcerative Colitis in IBD
 01:29
Inflammatory Bowel Disease IV: Pharmacological Management
Pharmacologic...
 01:27
Inflammatory Bowel Disease I: Ulcerative Colitis
Inflammatory bowel disease, or IBD, encompasses a group of disorders characterized by chronic inflammation or ulceration of the gastrointestinal tract.
Risk Factors
The exact cause of IBD remains unclear, although it is believed to be due to a mix of genetic, environmental, microbial, and immune factors. Genetic factors are significant in determining susceptibility to IBD, with family history being a critical risk factor. Individuals with a first-degree relative who has IBD are at...