Related Experiment Videos

Hidradenitis suppurativa complicated by erosive arthropathy and ulcerative keratitis

N Abid1, A Opran, F Rosner

  • 1Mount Sinai Services at Queens Hospital Center, Department of Medicine, Division of Rheumatology, Jamaica, New York 11432, USA.

Related Concept Videos

Rheumatic Heart Disease I: Introduction01:23

Rheumatic Heart Disease I: Introduction

Rheumatic heart disease or RHD is a chronic condition that results from rheumatic fever, causing permanent damage to the heart valves.Etiology and Risk FactorsIt primarily arises from rheumatic fever, an inflammatory disease that can develop after untreated or inadequately treated group A streptococcal (GAS) pharyngitis. Streptococcus spreads through direct contact with oral or respiratory secretions. While the bacteria are the causative agents, factors like malnutrition, overcrowding, poor...
Staphylococcal Skin Infections01:29

Staphylococcal Skin Infections

Staphylococcus aureus is a Gram-positive coccus that resides harmlessly on the skin and mucous membranes of healthy individuals. When the skin barrier is breached, it can shift from a commensal to an opportunistic pathogen. This transition is facilitated by surface adhesins, such as clumping factor B and S. aureus surface protein G (SasG), which bind to structural proteins, including loricrin and cytokeratin, in the damaged epidermis. Protein A, another key factor, binds the Fc region of...
Peripheral Artery Disease I: Introduction01:30

Peripheral Artery Disease I: Introduction
Peripheral artery disease (PAD) predominantly results from atherosclerosis, which involves the accumulation of fatty deposits, or plaques, within the walls of arteries. This causes them to narrow and harden, significantly reducing blood flow. PAD predominantly affects the legs, particularly the arteries supplying the thighs and calves. In rare cases, it may involve other arteries, including those in the arms.Etiology of PAD:The principal cause of PAD is atherosclerosis, which results from fatty...
Hypersensitivity Reactions: Immune-Complex Reactions01:19

Hypersensitivity Reactions: Immune-Complex Reactions

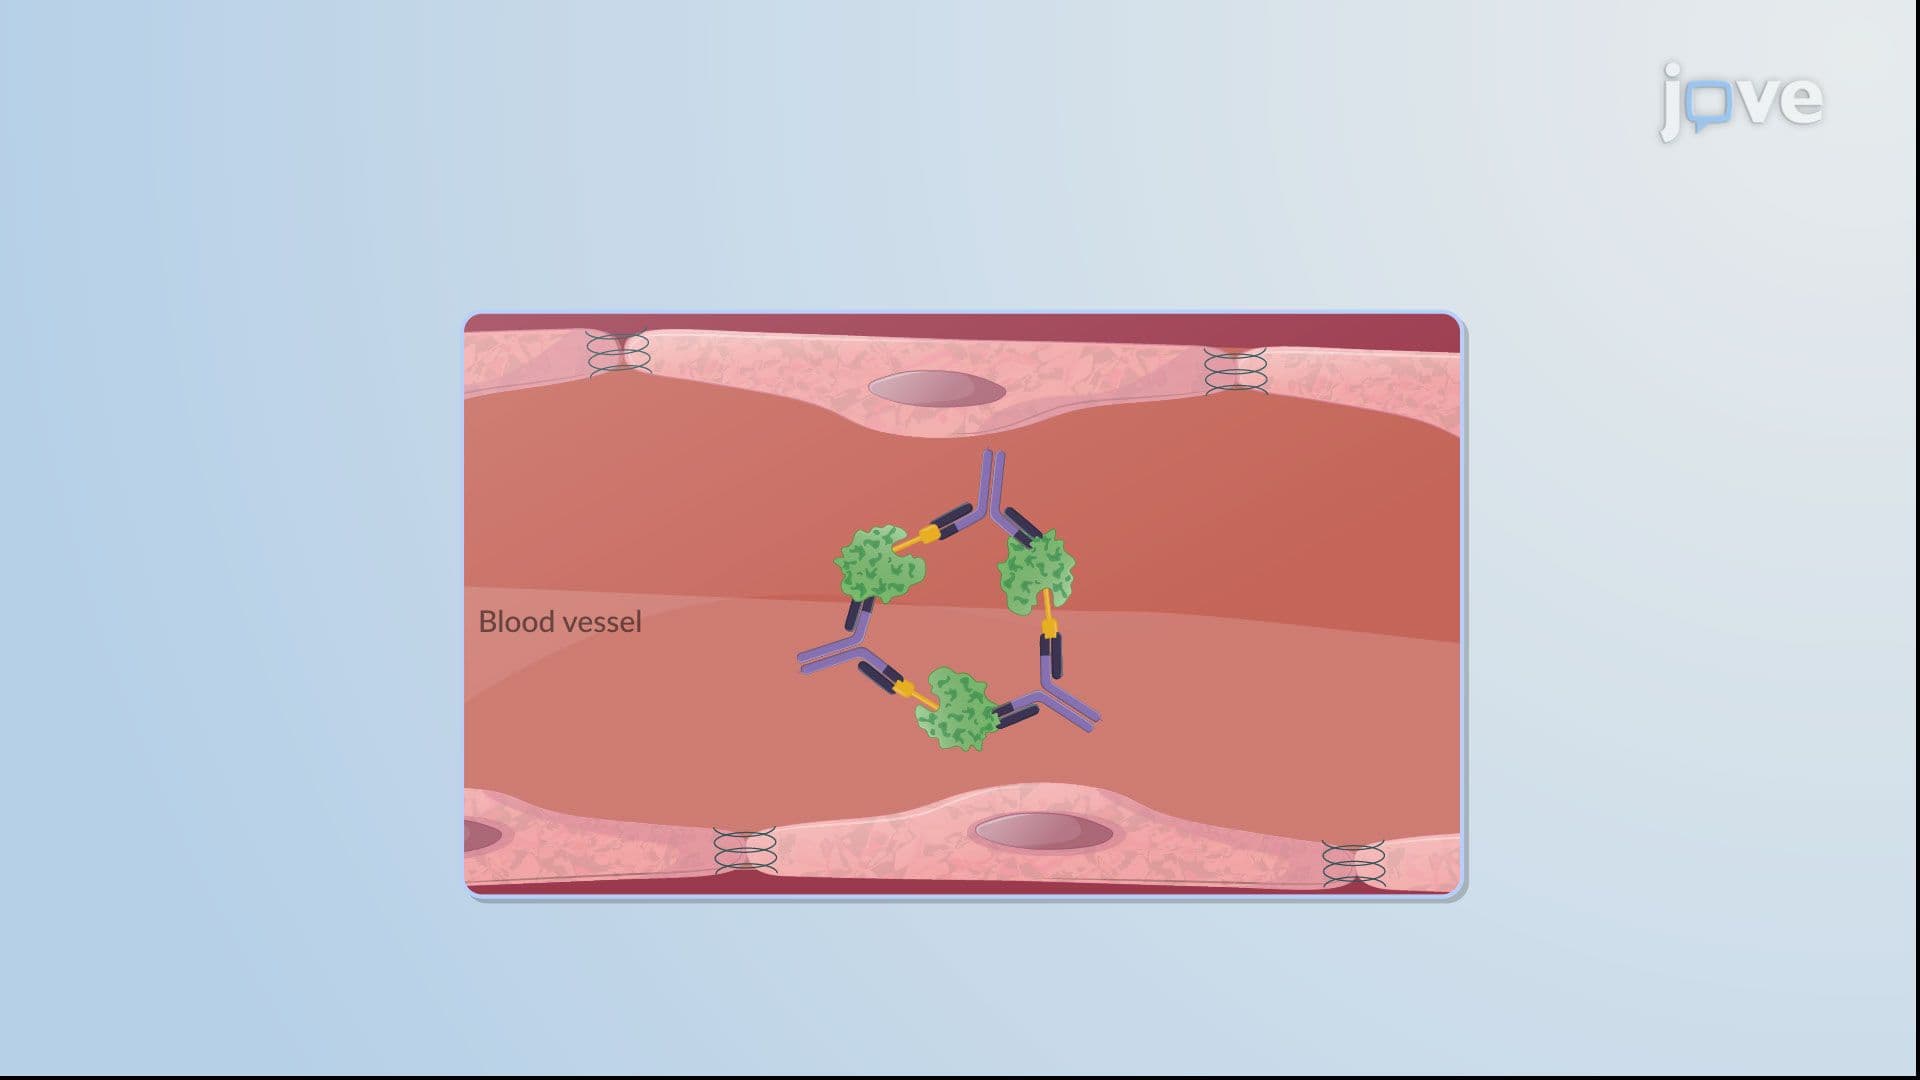
Type III hypersensitivity reactions occur when antigen–antibody complexes form and activate the complement system. Normally, these complexes help the clearance of antigens by phagocytes and red blood cells. However, when large numbers of immune complexes are present, they can deposit in tissues—particularly in the walls of blood vessels—leading to inflammation and tissue injury. These deposits trigger complement activation and neutrophil recruitment, resulting in serum sickness, a systemic...
Nephrotic Syndrome III : Nursing Management01:24

Nephrotic Syndrome III : Nursing Management

Nursing management for nephrotic syndrome adapts as the disease progresses, with strategies evolving to address advancing symptoms and complications.Early-Stage Management In the early stages, nursing interventions for nephrotic syndrome resemble those used in managing acute glomerulonephritis, focusing on symptom monitoring, fluid balance, and managing mild to moderate edema.Vital Signs: Regularly monitor blood pressure, pulse, respiratory rate, and temperature to promptly identify...
Acute Pancreatitis II: Pathophysiology01:21

Acute Pancreatitis II: Pathophysiology

The pathophysiology of acute pancreatitis centers on injury to pancreatic acinar cells, which initiates a cascade of harmful intracellular events.This injury leads to premature activation of trypsinogen to trypsin in the pancreas. Trypsin then activates other digestive enzymes, such as chymotrypsin, elastase, and phospholipase A2, which begin breaking down pancreatic tissue. The resulting autodigestion causes local inflammation, tissue swelling, hemorrhage, and fat necrosis.Injured acinar cells...