Related Experiment Video
Updated: Jun 27, 2026

HPLC-based Assay to Monitor Extracellular Nucleotide/Nucleoside Metabolism in Human Chronic Lymphocytic Leukemia Cells
Published on: July 20, 2016
Selective inhibitory effect of adenosine A1 receptor agonists on the proliferation of human tumor cell lines
Hossein Hosseinzadeh1, Mahmoud R Jaafari1,2, Jamal Shamsara1
1Pharmaceutical Research Center, School of Pharmacy, Mashhad University of Medical Sciences, Mashhad, Iran.

Background:
In this study, the effects of three structural analogues of adenosine upon proliferation of human tumor cells were investigated. Previous research showed a cytotoxic effect of adenosine via A3 receptor and A1 receptor and sometimes this effect was receptor independent. The researches showed a differential cytotoxic effect of adenosine and its A3 agonists on cancerous cells, while other studies demonstrated tumor promoting effect of adenosine and its A1 agonists. The purpose of the present study was the evaluation of the possible selective anti-tumor effect of A1 receptor agonists on cancerous cells.
Methods:
The substances of N6-cyclohexyl-adenosine (CHA, A1 agonist), R-isomer of N6 phenylisopropyladenosine (R-PIA, A1 agonist) and N5-eethylcarboxamido-adenosine (NECA, adenosine A1-A2 non-specific agonist) were tested for their anti-proliferative effect using 3-(4,5-dimethylthiazol-2-yl)-2,5-diphenyltetrazolium bromide (MTT) assay method. Hep G2, Hep2, CACO2, ACHN and L929 cell lines were used in this assay.
Results:
CHA inhibited cell proliferation in three cell lines (in concentration of 5-50 microM) and R-isomer of R-PIA in one cell line (in concentration of 10-50 microM). These effects were inhibited partially by addition of 1,3-Dipropyl-8-cyclopentylxanthine (A1 antagonist). The NECA analogue had no inhibitory effect on the cell proliferations. All of the substances had no cytotoxic effect on L929 cells (mouse connective tissue fibroblast cell line).
Conclusion:
CHA and R-PIA had inhibitory effect on the proliferation of human tumor cell lines partially via A1 receptor, while they didn't show such effect on fibroblast cells. These results suggest that A1 adenosine receptor agonist have a good potential of specific anti-tumor activity.
Insights
A1 adenosine receptor agonists, N6-cyclohexyl-adenosine (CHA) and R-isomer of N6 phenylisopropyladenosine (R-PIA), selectively inhibited human tumor cell proliferation. These findings suggest potential for specific anti-tumor activity via A1 receptors.
Area of Science:
- Pharmacology
- Oncology
- Cell Biology
Background:
- Adenosine exhibits complex effects on cell proliferation, with previous studies showing both cytotoxic and tumor-promoting activities.
- Adenosine's actions are mediated through various receptors, including A1 and A3, with differential effects observed on cancerous versus normal cells.
- The specific role of A1 receptor agonists in cancer warrants further investigation due to conflicting reports on their tumor-promoting or inhibiting effects.
Purpose of the Study:
- To evaluate the selective anti-tumor effects of A1 adenosine receptor agonists on human cancer cell lines.
- To investigate the potential of specific adenosine analogues in inhibiting tumor cell proliferation.
Main Methods:
- Three adenosine analogues were tested: N6-cyclohexyl-adenosine (CHA, A1 agonist), R-isomer of N6 phenylisopropyladenosine (R-PIA, A1 agonist), and N5-eethylcarboxamido-adenosine (NECA, non-specific agonist).
- The anti-proliferative effects were assessed using the MTT assay on human cancer cell lines (Hep G2, Hep2, CACO2, ACHN) and a control fibroblast cell line (L929).
- The involvement of the A1 receptor was confirmed by testing the effects of an A1 antagonist (1,3-Dipropyl-8-cyclopentylxanthine).
Main Results:
- CHA demonstrated significant inhibition of proliferation in three human tumor cell lines at concentrations of 5-50 microM.
- R-PIA inhibited proliferation in one cell line at concentrations of 10-50 microM.
- These inhibitory effects were partially reversed by an A1 antagonist, indicating A1 receptor involvement. NECA showed no inhibitory effect, and none of the compounds were cytotoxic to L929 fibroblasts.
Conclusions:
- A1 adenosine receptor agonists, CHA and R-PIA, exhibit selective inhibitory effects on the proliferation of human tumor cell lines.
- The observed anti-proliferative activity is partially mediated through the A1 receptor.
- These findings highlight the potential of A1 adenosine receptor agonists as agents for specific anti-tumor therapy.

Related Concept Videos
 01:31
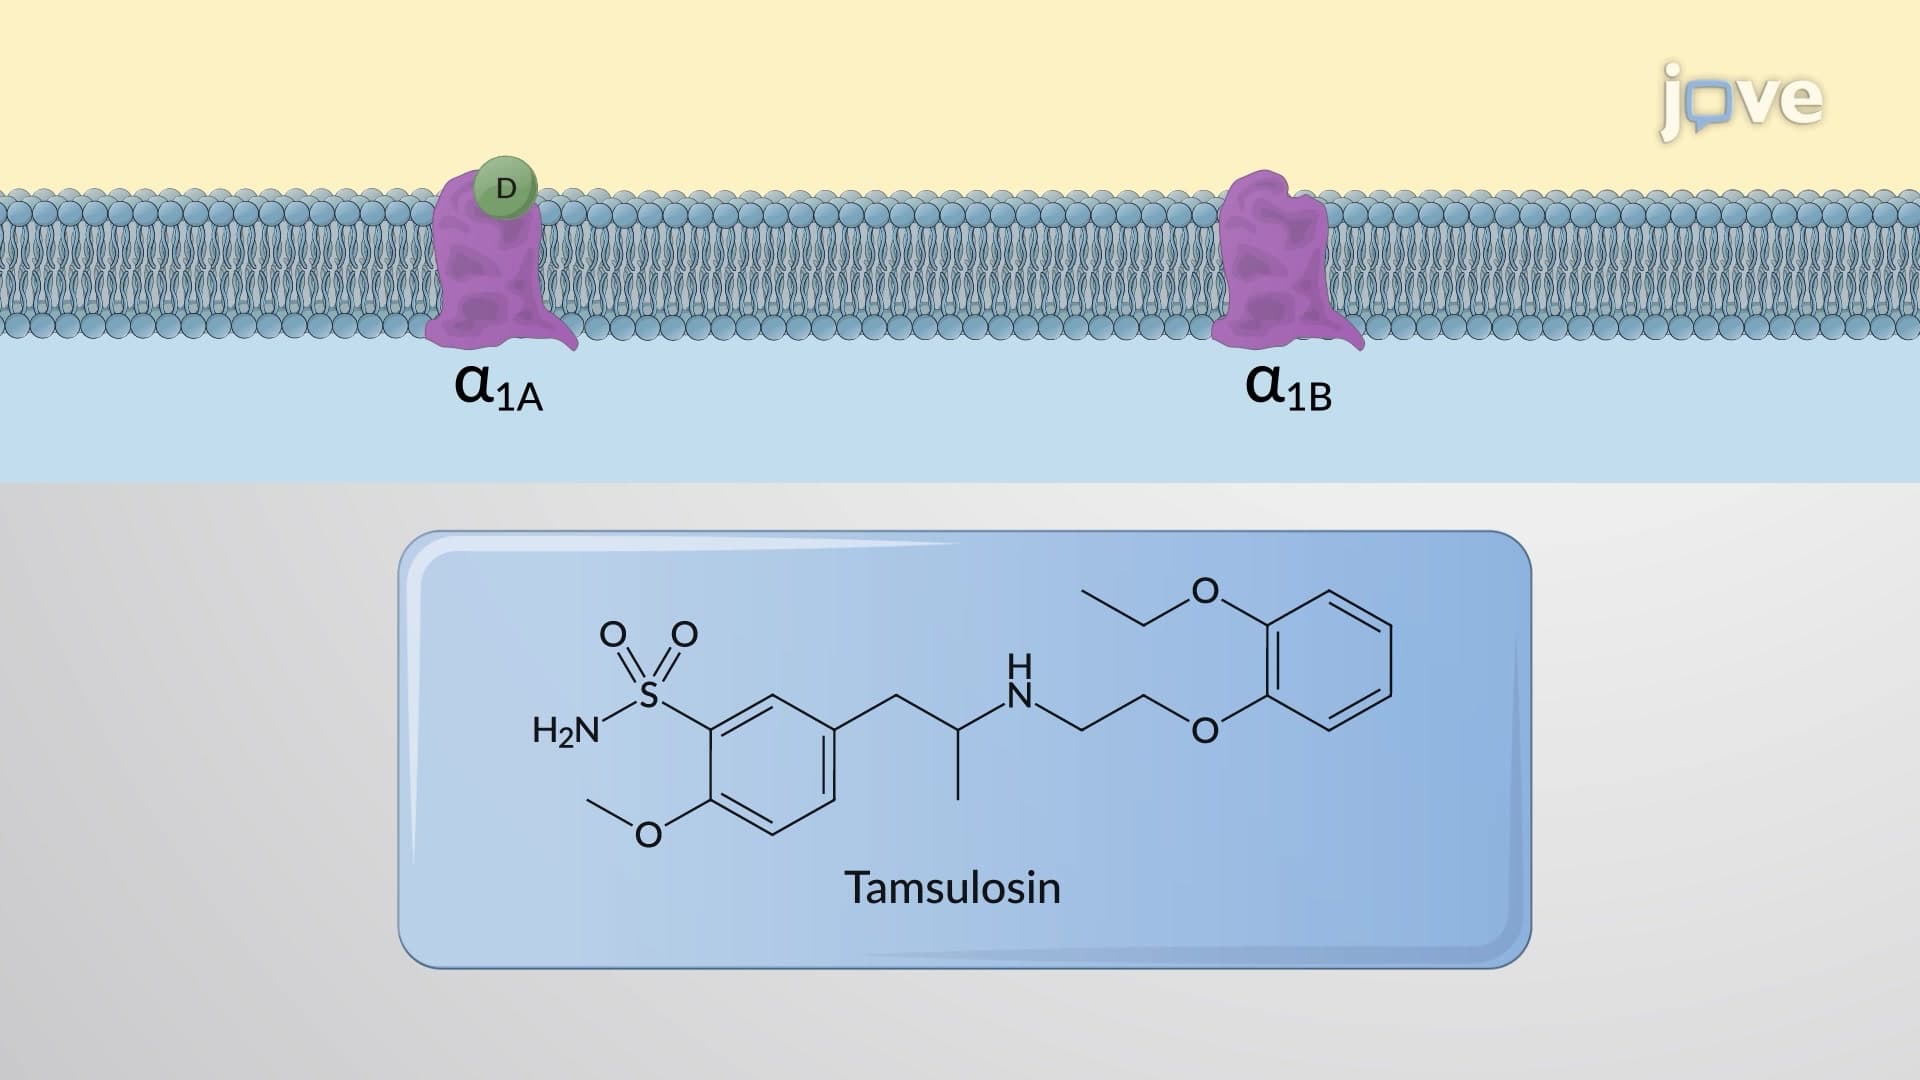
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 02:34
Inhibition of Cdk Activity
 01:17
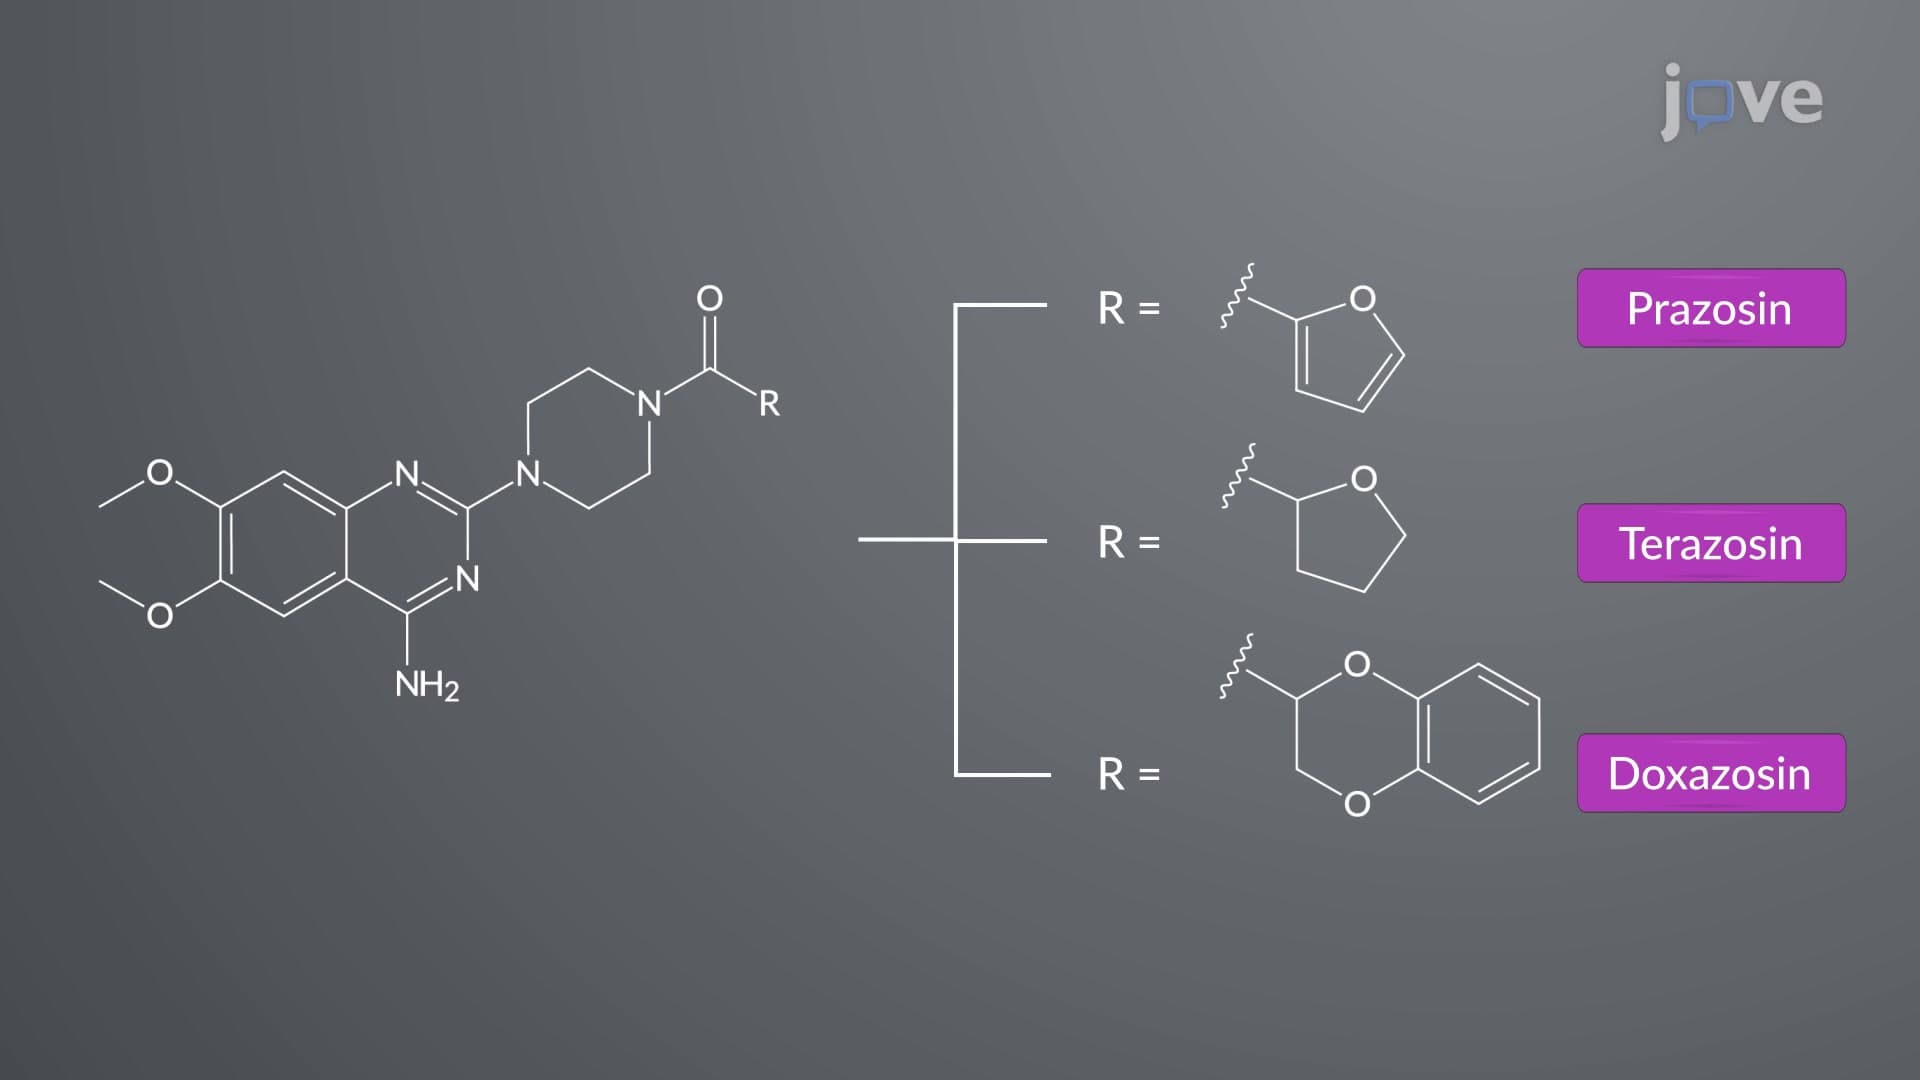
Adrenergic Antagonists: Chemistry and Classification of ɑ-Receptor Blockers
Nonselective α-blockers: Nonselective α-blockers contain haloalkylamine or imidazoline moieties. Phenoxybenzamine, with a haloalkylamine...
 01:22
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...
 01:30
Adrenergic Agonists: Direct-Acting Agents
These agents can be classified...
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers