Related Experiment Video
Updated: Jun 27, 2026


Assessment of Gastric Emptying in Non-obese Diabetic Mice Using a [13C]-octanoic Acid Breath Test
Published on: March 23, 2013
Ghrelin and obestatin levels in type 2 diabetic patients with and without delayed gastric emptying
Igor A Harsch1, Corinna Koebnick, Atingwa M Tasi
1Department of Medicine 1, Division of Endocrinology and Metabolism, Friedrich-Alexander University Erlangen-Nuremberg, Ulmenweg 18, 91054 Erlangen, Germany. igor.harsch@uk-erlangen.de

Abstract:
Alterations in the neurohumoral regulation of the upper intestine may change rhythmicity and pattern of ghrelin and obestatin, the latter presumably antagonizing ghrelin effects. Five nongastroparetic diabetic patients and five with gastroparesis were investigated. Over 390 min including breakfast and lunch, ghrelin was significantly lower in patients with gastroparesis compared with in those without (P = 0.015). Ghrelin subsequent to lunch decreased significantly (P = 0.011) in patients without gastroparesis, but not in gastroparetic patients (P = 0.669). Obestatin was similar in both groups and unchanged. No significant differences in ghrelin-to-obestatin ratio were observed (P = 0.530). Loss of rhythmicity in the ghrelin levels of gastroparetic diabetics highlights the importance of integrity of the neurohumoral-intestinal axis. Stable diurnal obestatin levels do not support the concept of interaction between ghrelin and obestatin in terms of regulation of food intake and gastric emptying.


Related Concept Videos
 01:24
Glucagon-like Receptor Agonists
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by the...
 01:22
Diabetes Mellitus: Type 2 and Gestational
 01:16
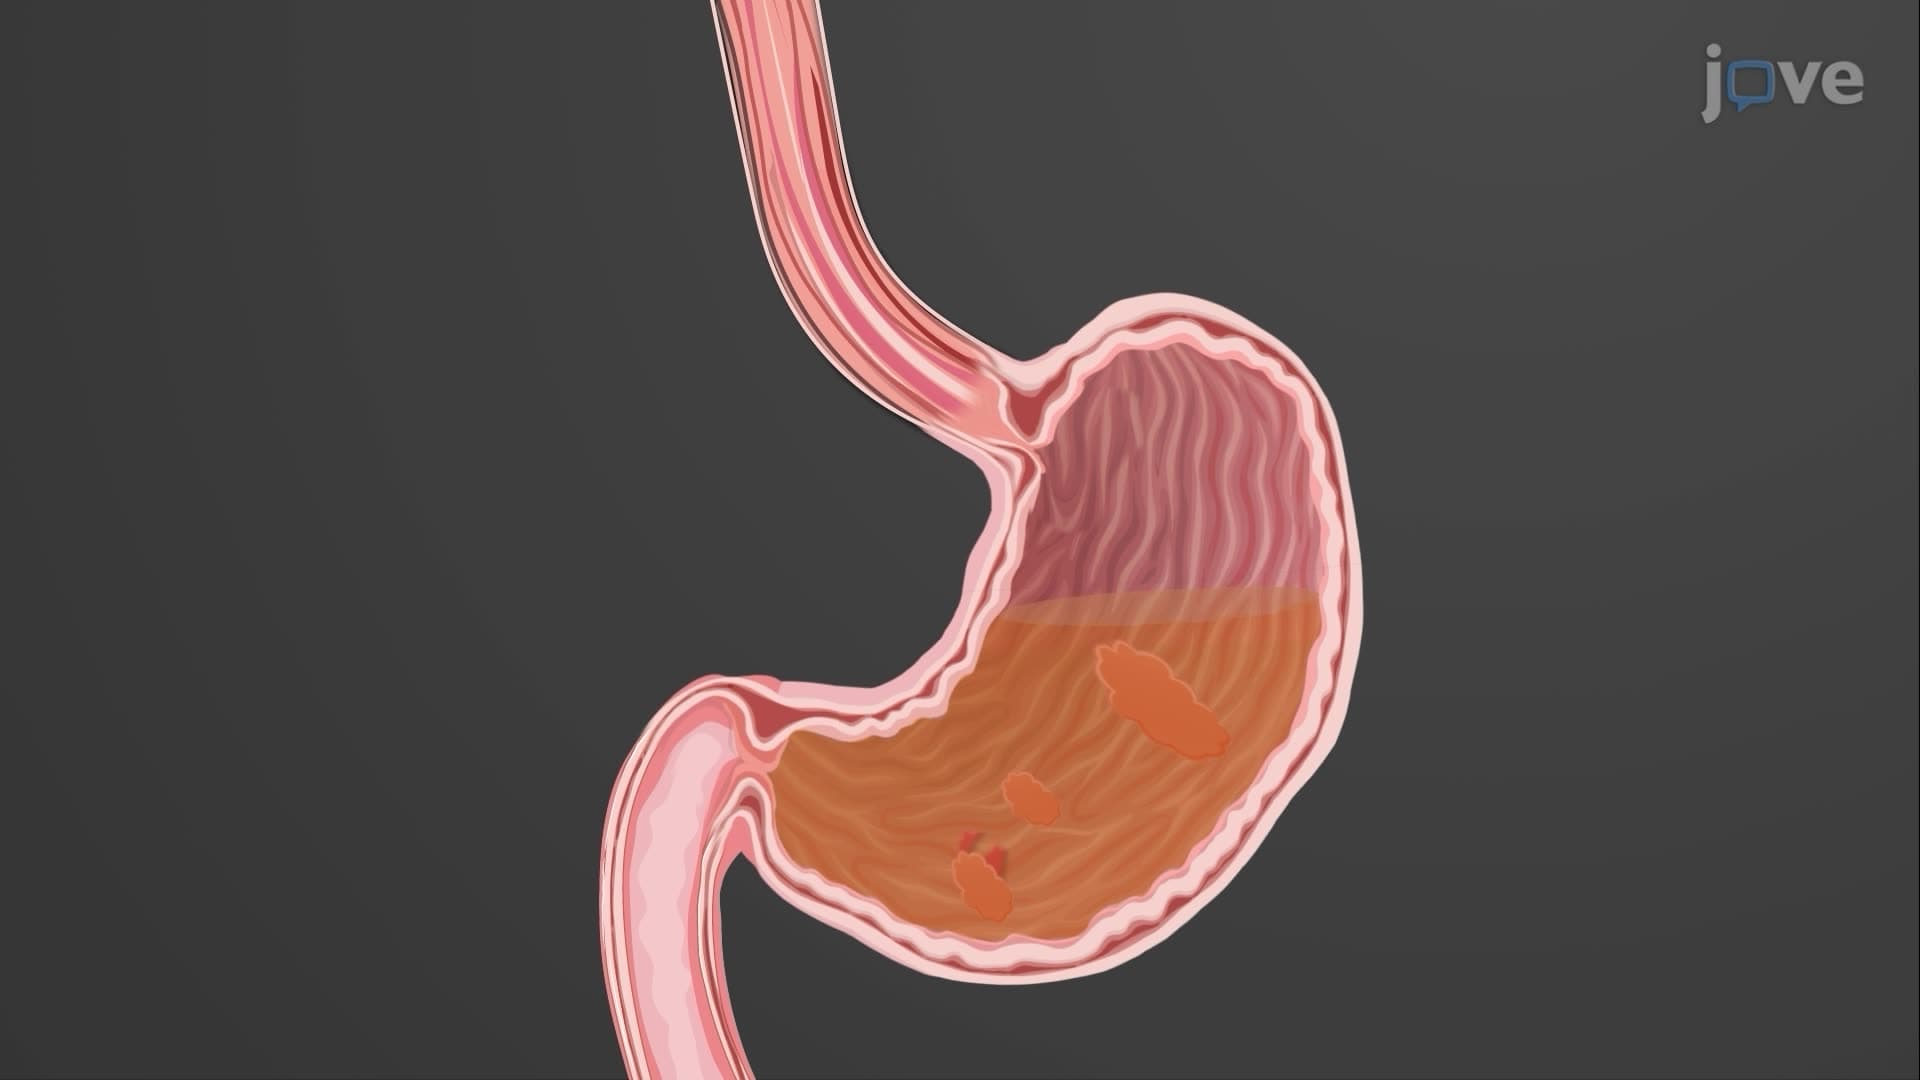
Gastric Emptying
 01:24
Type II Diabetes II: Pathophysiology
 01:15
Hypoglycemia and Glucagon
 01:06
Oral Hypoglycemic Agents: Glinides