Related Experiment Video
Updated: Jun 27, 2026


Assessment of Child Anthropometry in a Large Epidemiologic Study
Published on: February 2, 2017
Differences in left ventricular mass between overweight and normal-weight preadolescent children
Jose Peralta-Huertas1, Kristina Livingstone, Alayna Banach
1Faculty of Applied Health Sciences, Brock University, St. Catharines, ON L2S3A1, Canada.

Insights
Overweight children aged 10 show early cardiovascular changes, including higher left ventricular mass and cardiac output. These findings highlight the need for early intervention in pediatric obesity to prevent long-term heart issues.
Area of Science:
- Pediatric Cardiology
- Cardiovascular Physiology
- Childhood Obesity Research
Background:
- Childhood obesity is a growing public health concern.
- Early identification of cardiovascular risk factors in children is crucial.
- Understanding subclinical cardiovascular changes in overweight youth is essential.
Purpose of the Study:
- To investigate cardiac and arterial differences between overweight and normal-weight preadolescent children.
- To assess cardiovascular adaptations in children as young as 10 years old.
- To explore correlations between cardiovascular parameters and body composition in different weight groups.
Main Methods:
- Compared 20 overweight and 43 normal-weight children (mean age 10.2 years).
- Measured body composition, physical activity (PAME), and sexual maturation.
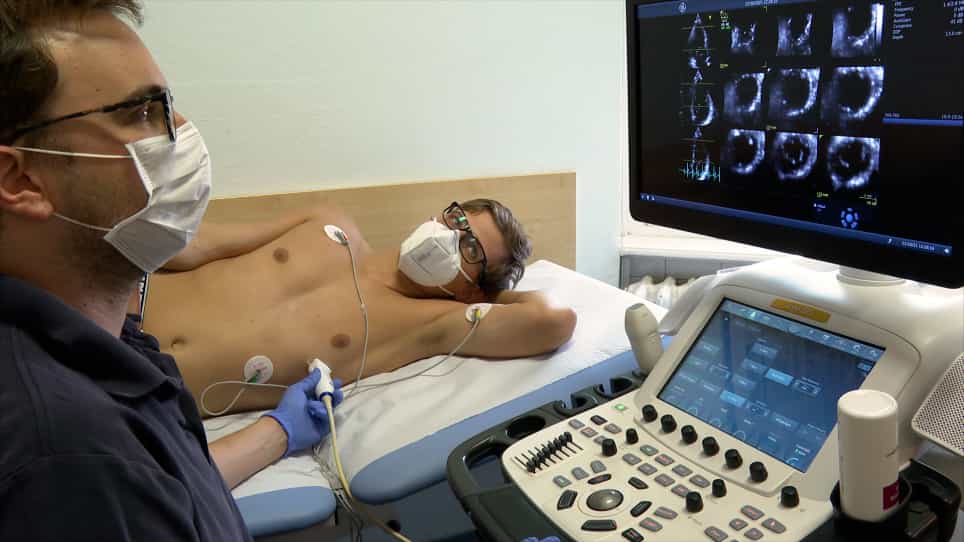
- Assessed cardiac dimensions (echocardiography), arterial stiffness (CaPP), and aerobic power.
- Calculated mean arterial pressure and ejection fraction.
Main Results:
- Overweight children exhibited higher left ventricular mass (LVM) and LVM normalized to height (LVMHT2.7).
- Overweight children had lower carotid artery pulse pressure (CaPP) but higher stroke volume and cardiac output.
- Physical activity metabolic equivalent (PAME) and relative peak aerobic power were higher in boys than girls.
Conclusions:
- Cardiovascular adaptations, including increased left ventricular mass, are evident in preadolescent overweight children.
- These findings suggest that overweight status at a young age is associated with significant cardiovascular alterations.
- Early detection and management of pediatric obesity are vital for mitigating cardiovascular risks.
Abstract:
This study examined cardiac and arterial differences between overweight and normal-weight preadolescent children. Twenty children (10.2 +/- 0.4 years of age) classified as overweight, on the basis of age-appropriate body mass index (BMI) cutoffs, were compared with 43 normal-weight controls. Height, mass, and body surface area were measured. Relative body fat and lean body mass were estimated from skinfold thickness. Each child's weekly physical activity metabolic equivalent (PAME) was calculated using a standardized questionnaire, and his or her sexual maturation was self-assessed using the Tanner scale. Peak aerobic power was assessed using a cycle ergometer and normalized to lean body mass. Mean arterial pressure was calculated from systolic and diastolic blood pressure (DBP) measurements taken with a Finapres. Cardiac dimensions were measured, using Mu-mode 2-dimensional echocardiography, and normalized to body surface area and height2.7. Left carotid artery pulse pressure (CaPP) was assessed with applanation tomometry. Overweight boys and girls had a higher left ventricular mass (LVM) and LVMHT2.7 than normal-weight boys and girls. CaPP was signficantly lower in the overweight than in the normal-weight groups, whereas PAME and relative peak aerobic power were significantly higher in the boys than the girls. Although overweight children had significantly higher stroke volumes and cardiac outputs than normal-weight children, ejection fraction was similar in the weight groups. Adjusted LVMHT2.7 was associated with cardiac volume measurements, BMI, and DBP in normal-weight children, whereas in the overweight children LVMHT2.7 did not significantly correlate with any variable. In conclusion, we found that cardiovascular adaptations can be seen in prepubescent overweight children as young as 10 years of age.

Related Concept Videos
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send blood...
 01:27
Regulation of Stroke Volume
Preload refers to the degree of stretch on the heart before it contracts. It's analogous to the stretching of a rubber band; the more it's stretched, the more forcefully it snaps back. This concept is encapsulated in the Frank-Starling law of the...