Related Experiment Video
Updated: Jun 27, 2026

Transcorporal Artificial Urinary Sphincter Cuff Placement in a Case Requiring Revision for Urethral Atrophy
Published on: June 16, 2022
Managing the urethra at transvaginal pelvic organ prolapse repair: a urodynamic approach
Katie N Ballert1, Grace Y Biggs, Anthony Isenalumhe
1Department of Urology, New York University, New York, New York 10016, USA.

Purpose:
We evaluated the protocol that we use to determine whether a mid urethral synthetic sling will be placed at transvaginal pelvic organ prolapse repair.
Materials And Methods:
A total of 140 patients underwent transvaginal repair for stage 2 to 4 pelvic organ prolapse, of whom 105 were treated according to the protocol and had a minimum 3 months of followup or required earlier intervention. Urodynamics were performed without prolapse reduction. When stress urinary incontinence was not identified, a pessary was placed and the study was repeated. Patients were designated as having urodynamic, occult or no stress urinary incontinence. Patients with urodynamic or occult stress urinary incontinence underwent a simultaneous mid urethral synthetic sling procedure, while those without urodynamic or occult stress urinary incontinence did not. Charts were reviewed to determine whether further intervention was required for stress urinary incontinence or obstruction.
Results:
The risk of intervention due to obstruction after receiving a mid urethral synthetic sling was 8.5%. The risk of intervention for stress urinary incontinence in patients with no clinical, urodynamic or occult stress urinary incontinence and no mid urethral synthetic sling was 8.3%. The risk of intervention for stress urinary incontinence in patients with clinical stress urinary incontinence but no urodynamic or occult stress urinary incontinence and no mid urethral sling was 30%.
Conclusions:
Using our urodynamic protocol to manage the urethra at transvaginal pelvic organ prolapse repair the risk of intervention due to obstruction is essentially equal to the risk of intervention due to stress urinary incontinence when no clinical, urodynamic or occult stress urinary incontinence was present and no mid urethral synthetic sling was placed. In patients who report clinical stress urinary incontinence preoperatively despite no urodynamic or occult stress urinary incontinence there is a much higher rate of further intervention for stress urinary incontinence.

Related Concept Videos
 01:19
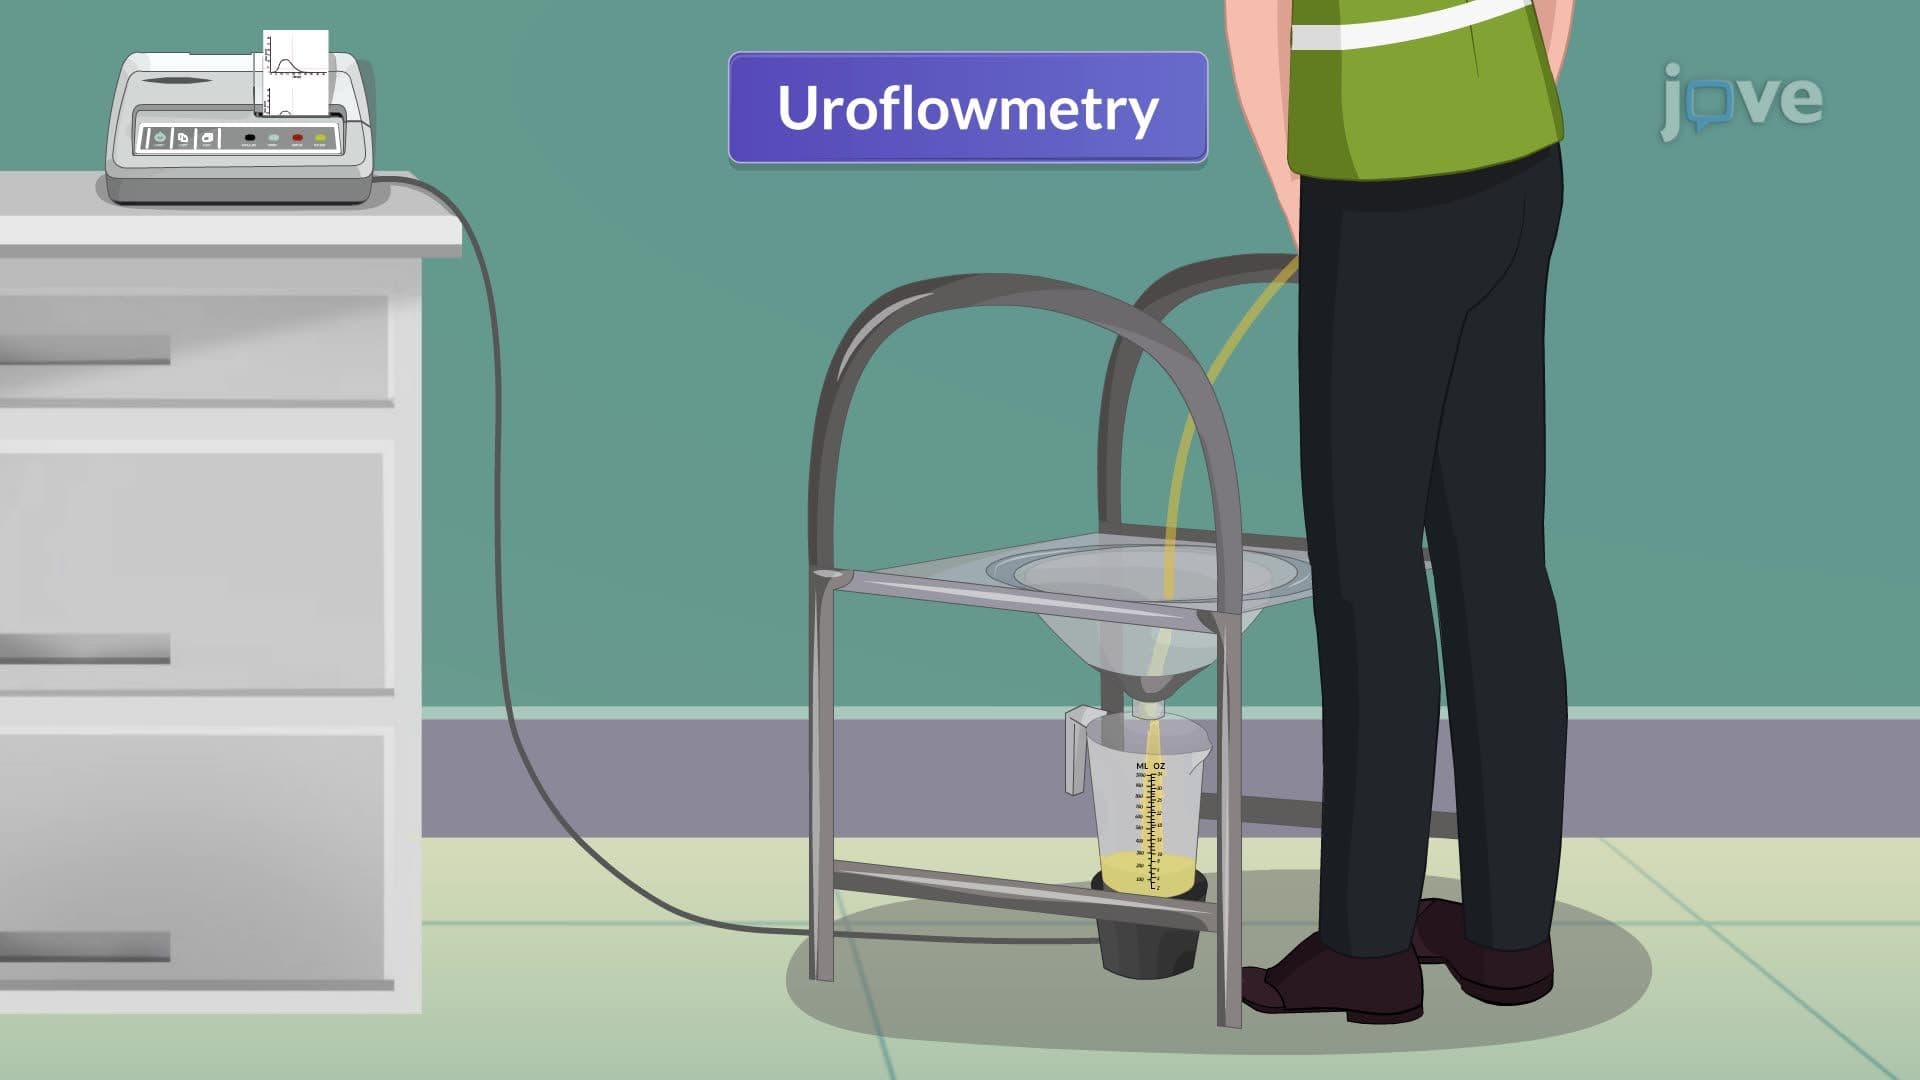
Urodynamic Studies: Uroflowmetry
 01:19
Anatomy of the Genitourinary System II: Bladder and Urethra
 01:25
Urinary Tract Calculi VI: Surgical Management
 01:28
Urologic Endoscopic Procedure: Cystoscopic Examination
 01:28
Urinary Tract Calculi V: Nursing Management
 01:30
Urinary Tract Calculi III: Medical Management