Related Experiment Video
Updated: Jun 27, 2026
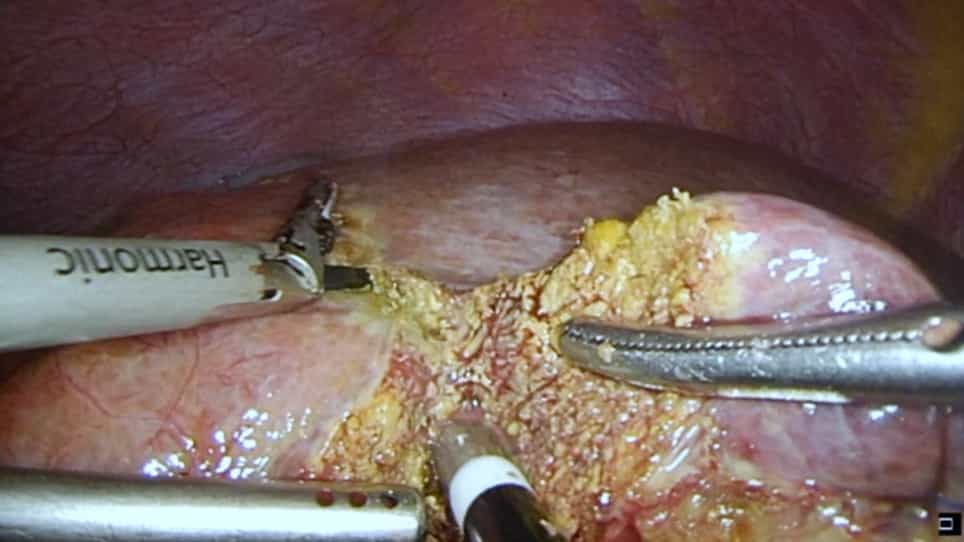

Application of Hemostatic Devices in Laparoscopic Hepatectomy
Published on: April 19, 2022
[Laparoscopic hepatectomy for hepatocellular carcinoma]
Ming-Gen Hu1, Rong Liu, Ying Luo
1Department of Hepatobiliary Surgery, the People's Liberation Army General Hospital, Beijing 100853, China.

Insights
Laparoscopic hepatectomy (LH) is a safe and feasible surgical option for treating hepatocellular carcinoma (HCC). This minimally invasive approach offers good outcomes for HCC patients.
Area of Science:
- Hepatobiliary Surgery
- Minimally Invasive Surgery
- Surgical Oncology
Context:
- Hepatocellular carcinoma (HCC) is a primary liver malignancy.
- Surgical resection is a key treatment modality for HCC.
- Laparoscopic hepatectomy (LH) offers potential benefits over open surgery.
Purpose:
- To evaluate the safety and feasibility of laparoscopic hepatectomy (LH) for treating hepatocellular carcinoma (HCC).
Summary:
- A study involving 123 HCC patients who underwent LH between 2002 and 2007.
- The procedure demonstrated acceptable operative times, blood loss, and short postoperative hospital stays.
- Complications included biliary fistula and ascites, with low recurrence rates and no port metastasis observed.
Impact:
- Laparoscopic hepatectomy (LH) is confirmed as a safe and viable treatment for hepatocellular carcinoma (HCC).
- This minimally invasive technique can achieve favorable short-term outcomes for HCC management.
- Further research may explore long-term oncological control and expanded indications for LH in HCC.
Objective:
To discuss the value of laparoscopic hepatectomy (LH) for hepatocellular carcinoma (HCC).
Methods:
From April 2002 to December 2007, 123 cases of HCC, included 82 males and 41 females, with a mean age of 53.8 years (range 31 - 69 years) underwent LH.
Results:
Ninety-three cases underwent total laparoscopic hepatectomies (included regular hepatectomies in 52 cases). Twenty-six cases underwent laparoscopy assisted hepatectomies (included regular hepatectomies in 12 cases). Four cases converted to open hepatectomies because of massive bleeding of hepatic vein. The operative time was (205.5 +/- 92.5) min (range 115 - 290 min). The median intraoperative blood loss was 250 ml (rang 100 - 1500 ml). The postoperative hospital stay was (5.8 +/- 1.6) days (range 3 - 15 days). The biggest size of the resections was 18 cm x 16 cm x 12 cm. One patient died of gas embolism during the operation. Biliary fistula occurred in 5 cases and ascites in 8 cases postoperatively, which were cured for several days. By 4 - 61 months of follow up, recurrence in liver occurred in 5 cases. There was no peritoneum and port metastasis.
Conclusion:
LH is a safe and feasible method for the treatment of HCC.