Related Experiment Video
Updated: Jun 27, 2026


Quantification of the Immunosuppressant Tacrolimus on Dried Blood Spots Using LC-MS/MS
Published on: November 8, 2015
Urine metabolites reflect time-dependent effects of cyclosporine and sirolimus on rat kidney function
Jost Klawitter1, Jamie Bendrick-Peart, Birgit Rudolph
1Departments of Anesthesiology and Nephrology, University of Colorado, Denver, Colorado, USA.

Abstract:
The clinical use of the immunosuppressant calcineurin inhibitor cyclosporine is limited by its nephrotoxicity. This is enhanced when combined with the immunosuppressive mTOR inhibitor sirolimus. Nephrotoxicity of both drugs is not yet fully understood. The goal was to gain more detailed mechanistic insights into the time-dependent effects of cyclosporine and sirolimus on the rat kidney by using a comprehensive approach including metabolic profiling in urine ((1)H NMR spectroscopy), kidney histology, kidney function parameters in plasma, measurement of glomerular filtration rates, the oxidative stress marker 15-F(2t)-isoprostane in urine, and immunosuppressant concentrations in blood and kidney. Male Wistar rats were treated with vehicle (controls), cyclosporine (10/25 mg/kg/day), and/or sirolimus (1 mg/kg/day) by oral gavage once daily for 6 and 28 days. Twenty-eight day treatment led to a decrease of glomerular filtration rates (cyclosporine, -59%; sirolimus, -25%). These were further decreased when both drugs were combined (-86%). Histology revealed tubular damage after treatment with cyclosporine, which was enhanced when sirolimus was added. No other part of the kidney was affected. (1)H NMR spectroscopy analysis of urine (day 6) revealed time-dependent changes of 2-oxoglutarate, citrate, and succinate concentrations. In combination with increased urine isoprostane concentrations, these changes indicated oxidative stress. After 28 days of cyclosporine treatment, urine metabonomics shifted to patterns typical for proximal tubular damage with reduction of Krebs cycle intermediates and trimethylamine-N-oxide concentrations, whereas acetate, lactate, trimethylamine, and glucose concentrations increased. Again, sirolimus enhanced these negative effects. Our results indicate that cyclosporine and/or sirolimus induce damage of the renal tubular system. This is reflected by urine metabolite patterns, which seem to be more sensitive than currently used clinical kidney function markers such as creatinine concentrations in serum. Metabolic profiling in urine may provide the basis for the development of toxicodynamic monitoring strategies for immunosuppressant nephrotoxicity.
Insights
Calcineurin inhibitors like cyclosporine and mTOR inhibitors like sirolimus cause kidney damage, particularly in the tubules. Urine metabolite analysis offers a sensitive method for monitoring this immunosuppressant nephrotoxicity.
Area of Science:
- Nephrology
- Pharmacology
- Toxicology
Background:
- Cyclosporine (immunosuppressant calcineurin inhibitor) and sirolimus (mTOR inhibitor) are vital in transplantation but limited by nephrotoxicity.
- Combined use of cyclosporine and sirolimus exacerbates nephrotoxicity, with underlying mechanisms requiring further elucidation.
Purpose of the Study:
- To investigate the time-dependent effects of cyclosporine and sirolimus on rat kidneys.
- To gain mechanistic insights into immunosuppressant-induced nephrotoxicity using a multi-faceted approach.
Main Methods:
- Rats received cyclosporine and/or sirolimus for 6 and 28 days.
- Evaluated kidney function (GFR), histology, oxidative stress (urine isoprostane), and blood/kidney drug levels.
- Utilized urine metabolic profiling via (1)H NMR spectroscopy.
Main Results:
- Combined treatment significantly reduced glomerular filtration rates and induced tubular damage.
- Urine metabolite analysis revealed oxidative stress and proximal tubular damage patterns.
- Urine metabonomics showed greater sensitivity to drug-induced kidney injury than serum creatinine.
Conclusions:
- Cyclosporine and sirolimus induce renal tubular damage, with sirolimus potentiating cyclosporine's effects.
- Urine metabolic profiling provides sensitive, early detection of immunosuppressant nephrotoxicity.
- This approach may enable development of novel toxicodynamic monitoring strategies.

Related Concept Videos
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:17
Factors Affecting Renal Clearance: Renal Impairment
One condition associated with renal failure is uremia. Uremia is characterized by impaired glomerular filtration and fluid accumulation in the body. This condition hinders the renal clearance of drugs, resulting in drug accumulation and potential...
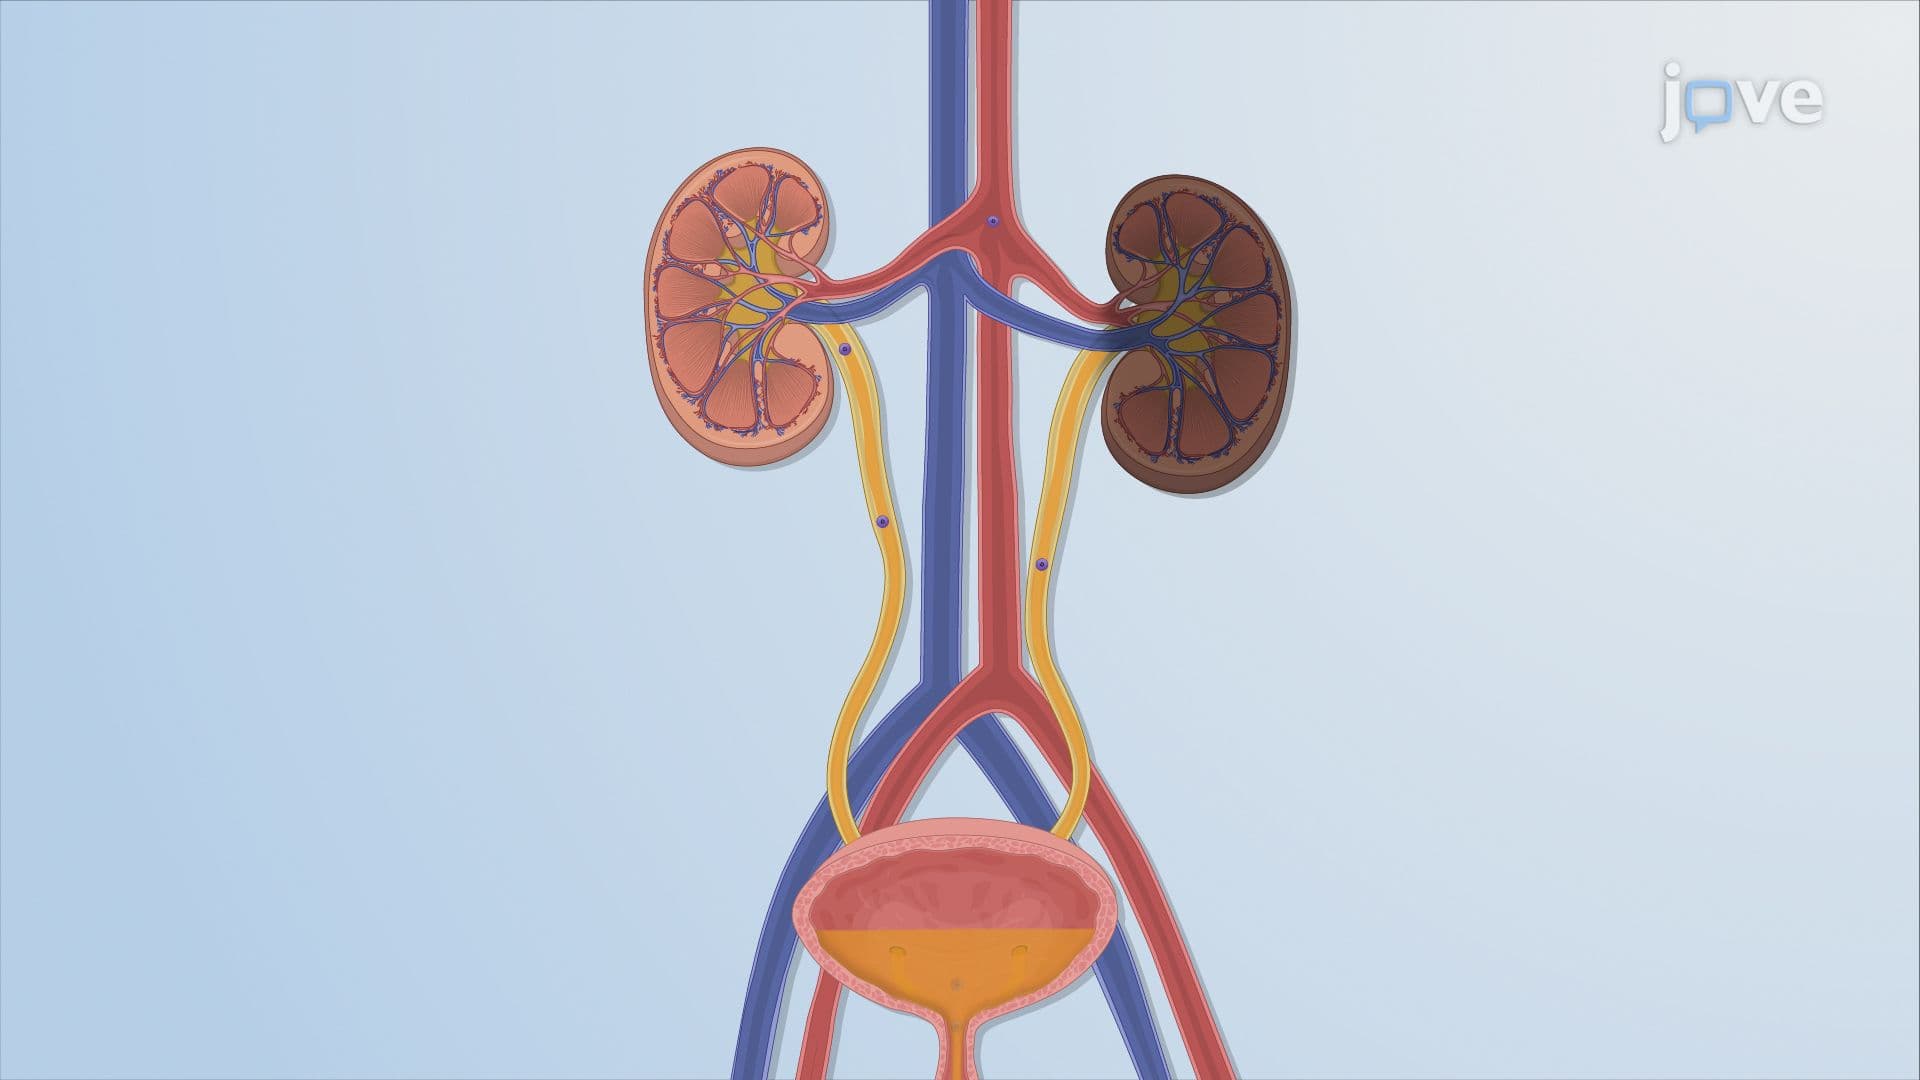 01:25
Drug Dosing in Renal Diseases: Measurement of Glomerular Filtration Rate
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:25
Renal Drug Excretion: Tubular Reabsorption
 01:14
Effect of Hepatic Disease on Pharmacokinetics: Active Drug, Metabolite and Fraction of Metabolized Drug