Related Experiment Video
Updated: Jun 26, 2026


Microbial Control and Monitoring Strategies for Cleanroom Environments and Cellular Therapies
Published on: March 17, 2023
Skin and surface lead contamination, hygiene programs, and work practices of bridge surface preparation and painting
M Abbas Virji1, Susan R Woskie, Lewis D Pepper
1Department of Work Environment, University of Massachusetts Lowell, Lowell, Massachusetts, USA. MVirji@cdc.gov

Abstract:
A 2005 regulatory review of the lead in construction standard by the Occupational Safety and Health Administration (OSHA) noted that alternative pathways of exposure can be as significant as inhalation exposure and that noncompliance with the standard pertaining to hygiene facilities and practices was the second most commonly violated section of the standard. Noncompliance with provisions of the standard and unhealthy work and hygiene practices likely increase the likelihood of take-home lead via contaminated clothing, automobiles, and skin, thus contributing to elevated blood lead levels (BLL) among construction workers and their family members. We performed a cross-sectional study of bridge painters working for small contractors in Massachusetts to investigate causes of persistent elevated BLLs and to assess lead exposures. Thirteen work sites were evaluated for a 2-week period during which surface and skin wipe samples were collected and qualitative information was obtained on personal hygiene practices, decontamination and hand wash facilities, and respiratory protection programs. Results showed lead contamination on workers' skin, respirators, personal automobiles, and the decontamination unit, indicating a significant potential for take-home lead exposure. Overall, the geometric mean (GM) skin lead levels ranged from 373 microg on workers' faces at end of shift to 814 microg on hands at break time. The overall GM lead level inside respirators was 143 microg before work and 286 microg after work. Lead contamination was also present inside workers' personal vehicles as well as on surfaces inside the clean side of the decontamination unit. Review of the respiratory protection programs, work site decontamination and hand wash facilities, and personal hygiene practices indicated that these factors had significant impact on skin and surface contamination levels and identified significant opportunities for improving work site facilities and personal practices. Elevated lead exposure and BLL can be minimized by strict adherence to the OSHA provisions for functioning decontamination and hygiene facilities and healthy personal hygiene practices.


Related Concept Videos
 01:26
Standard Precaution
Hand hygiene is the most crucial means to prevent the transmission of disease. Employers are legally required to provide their workers with personal protective equipment (PPE) to minimize exposure or contact with...
 01:19
Handwashing II: Pre-procedure and Initial Procedure Steps
The hand washing procedure itself includes the following steps. First, cover cuts, if any, on hands with a waterproof dressing. Cuts and abrasions can become contaminated with bacteria hindering the ability to clean the area thoroughly. In addition, repeated hand washing can worsen an injury. The nails must be short and clean, without nail paint...
 01:23
Hand hygiene
Hand washing...
 01:15
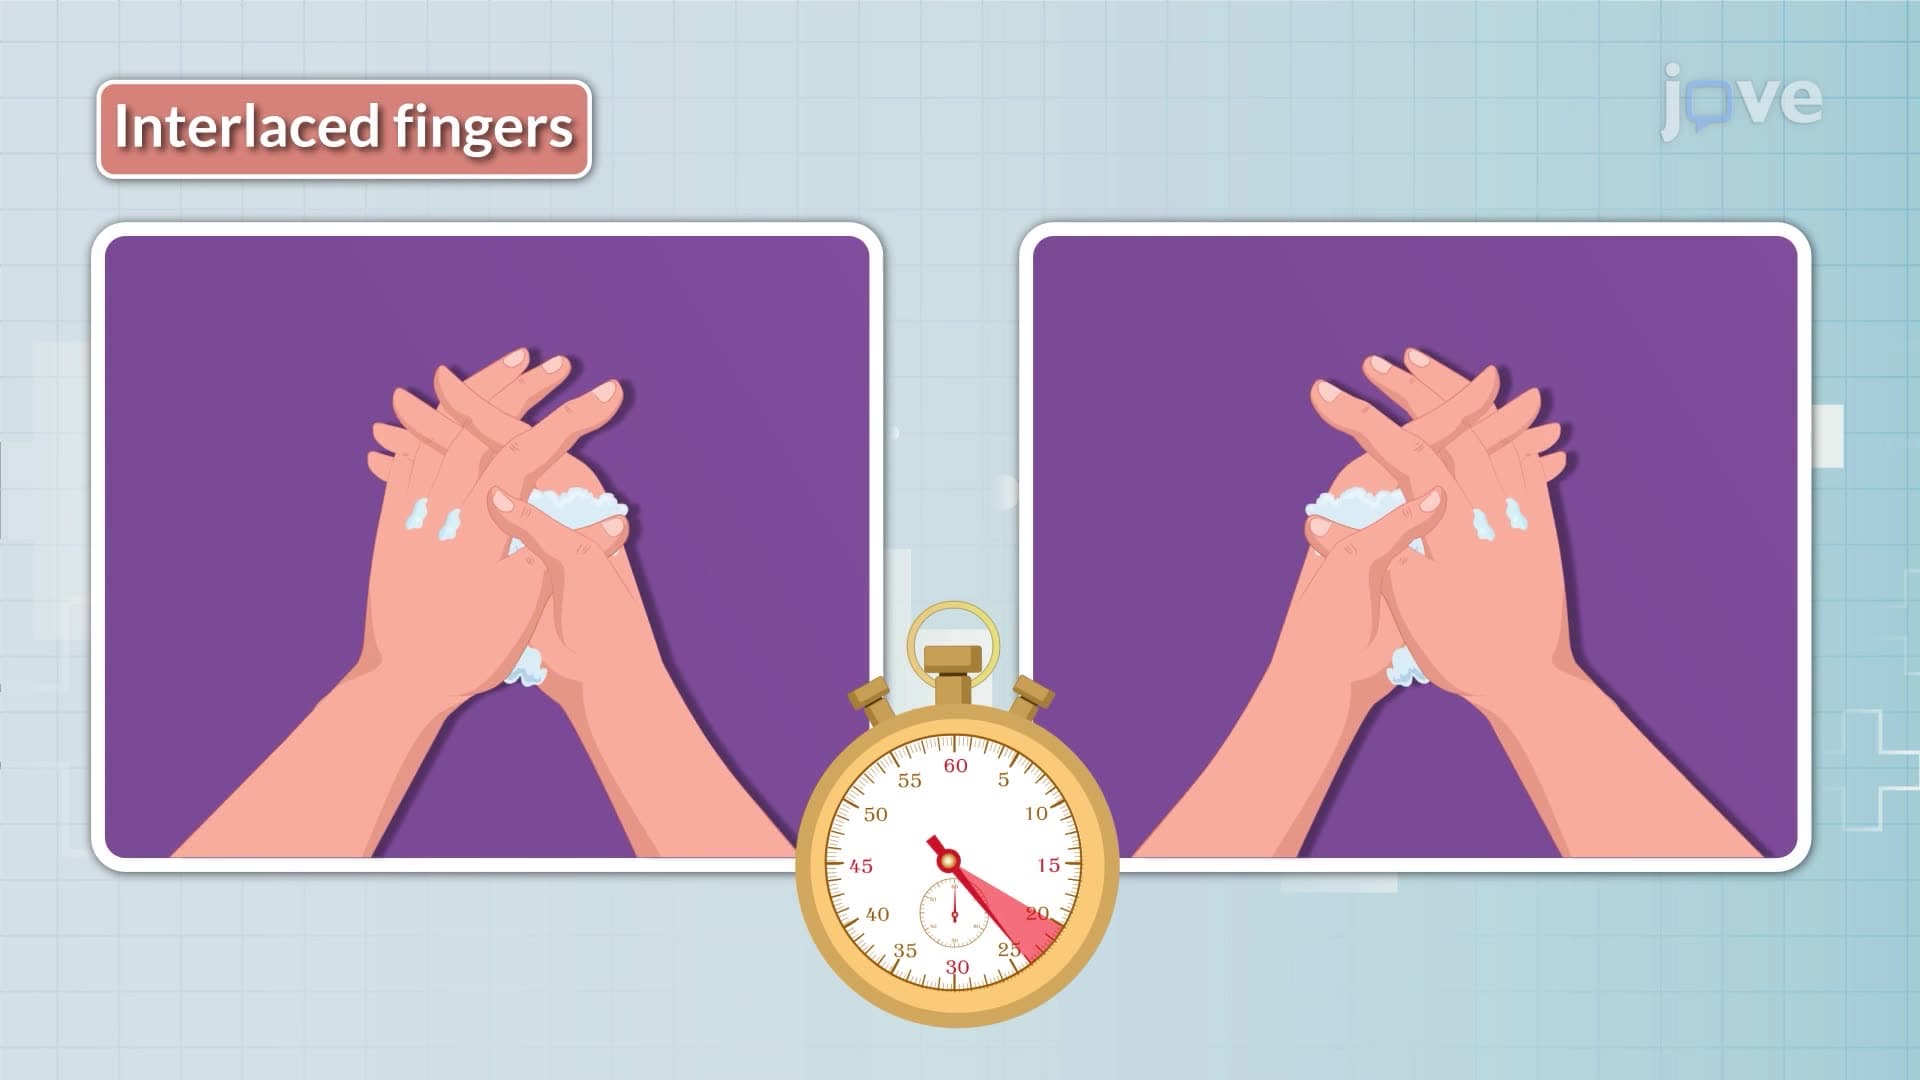
Handwashing III: During the Procedure and Post-Procedure Steps
 01:22
Waterproofing and Anti-Bacterial Admixtures in Concrete
Waterproofing admixtures render concrete hydrophobic,...
 01:14
Wood Surfacing
The equipment used in the surfacing process is a plane equipped with rotating blades. This tool efficiently smoothens the wood surface and can...