Related Experiment Video
Updated: Jun 26, 2026


Cecal Ligation Puncture Procedure
Published on: May 7, 2011
The vasopressin and copeptin response to infection, severe sepsis, and septic shock
Stefan Jochberger1, Jakob Dörler, Günter Luckner
1Department of Anaesthesiology and Critical Care Medicine, Innsbruck Medical University, Innsbruck, Austria.

Objective:
To compare the course of arginine vasopressin (AVP) and copeptin plasma concentrations between patients with infection, severe sepsis, and septic shock.
Design:
Prospective, closed-cohort study.
Setting:
Twelve-bed general and surgical intensive care unit and 33-bed internal medicine ward in a university hospital.
Patients:
Ten patients with infection, 22 with severe sepsis, and 28 with septic shock.
Interventions:
None.
Measurements And Main Results:
Hemodynamic, laboratory and clinical data were recorded daily during the first 7 days after intensive care unit or hospital admission. Parallel thereto, blood was withdrawn to determine plasma AVP (radioimmunoassay) and copeptin (immunoluminometric assay) concentrations. Standard tests, a mixed effects model, and a linear regression analysis were used for statistical analysis. The AVP response was different between the three study groups (p < 0.001) but did not change over time (p = 0.12). Although patients with severe sepsis and septic shock had higher AVP levels than did patients with infection (both p < 0.001), no difference in AVP concentrations was seen between severe sepsis and septic shock patients (p = 0.98). No difference in AVP was observed between survivors and nonsurvivors at day 28 (p = 0.87). In patients with severe sepsis, serum osmolarity (p < 0.001), arterial pH (p = 0.001), lactate (p < 0.001), and Pao2 (p = 0.04) were associated with the course of AVP plasma levels, whereas it was serum osmolarity alone in patients with septic shock (p = 0.03). Plasma AVP concentrations correlated with copeptin (r = .614, p < 0.001), but this correlation was influenced by continuous veno-venous hemofiltration (p = 0.002).
Conclusions:
Severe sepsis induced a stronger AVP response than infection without systemic inflammation. However, the lack of a difference in AVP plasma concentrations between patients with and without shock indicates that the AVP system does not function normally in severe sepsis. Our data support the hypothesis that impaired AVP response is at least partially responsible for the failure to restore vascular tone in septic shock.

Related Concept Videos
 01:25
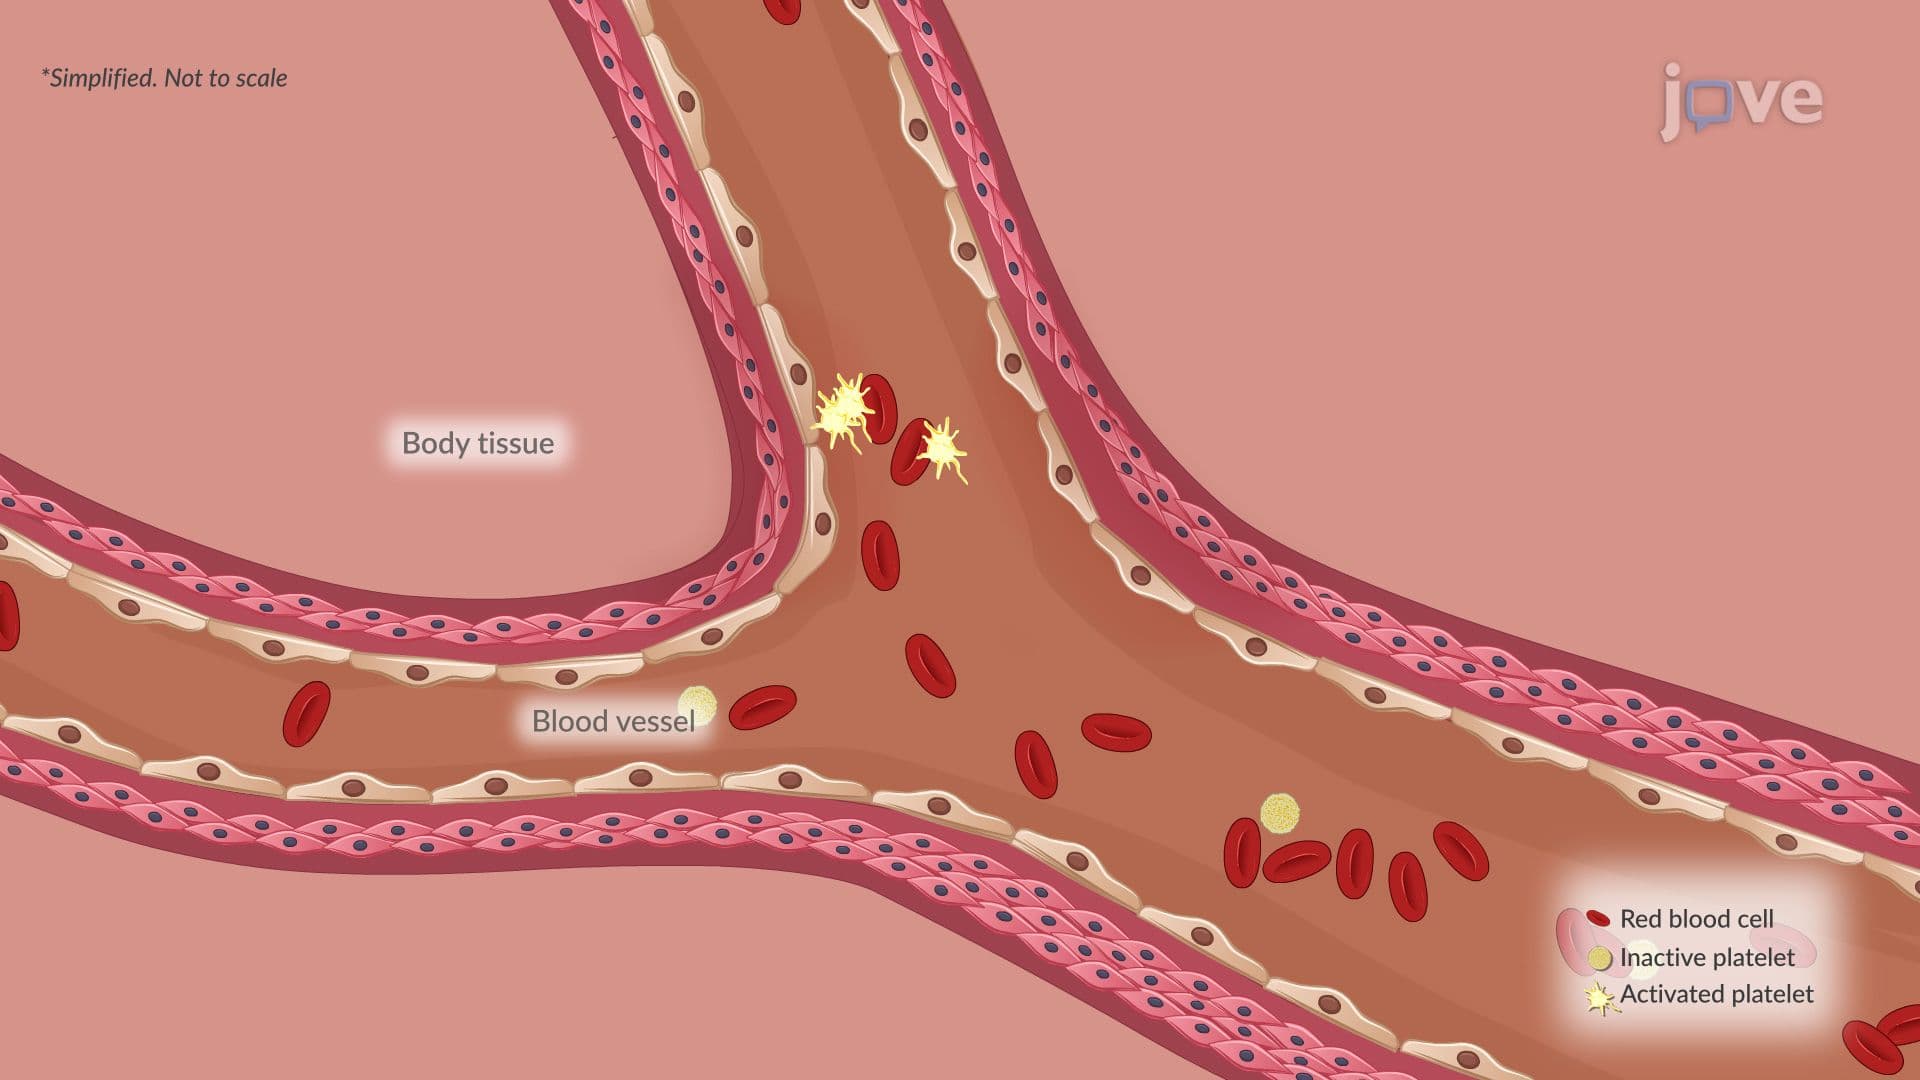
Acute Inflammation III: Local and Systemic Effects
 01:24
Blood Pressure Imbalances and Circulatory Shock
Blood Pressure: Hypertension and Hypotension
Normal blood pressure is 120/80 mm Hg. Elevated blood pressure is 120-129/under 80 mm Hg. Hypertension, warranting treatment at 130/80 mm Hg, is often asymptomatic and can lead to severe cardiovascular events, aneurysms, peripheral arterial disease, chronic renal disease, or cardiac...
 01:26
Bacterial Meningitis II: Pathophysiology
 01:27
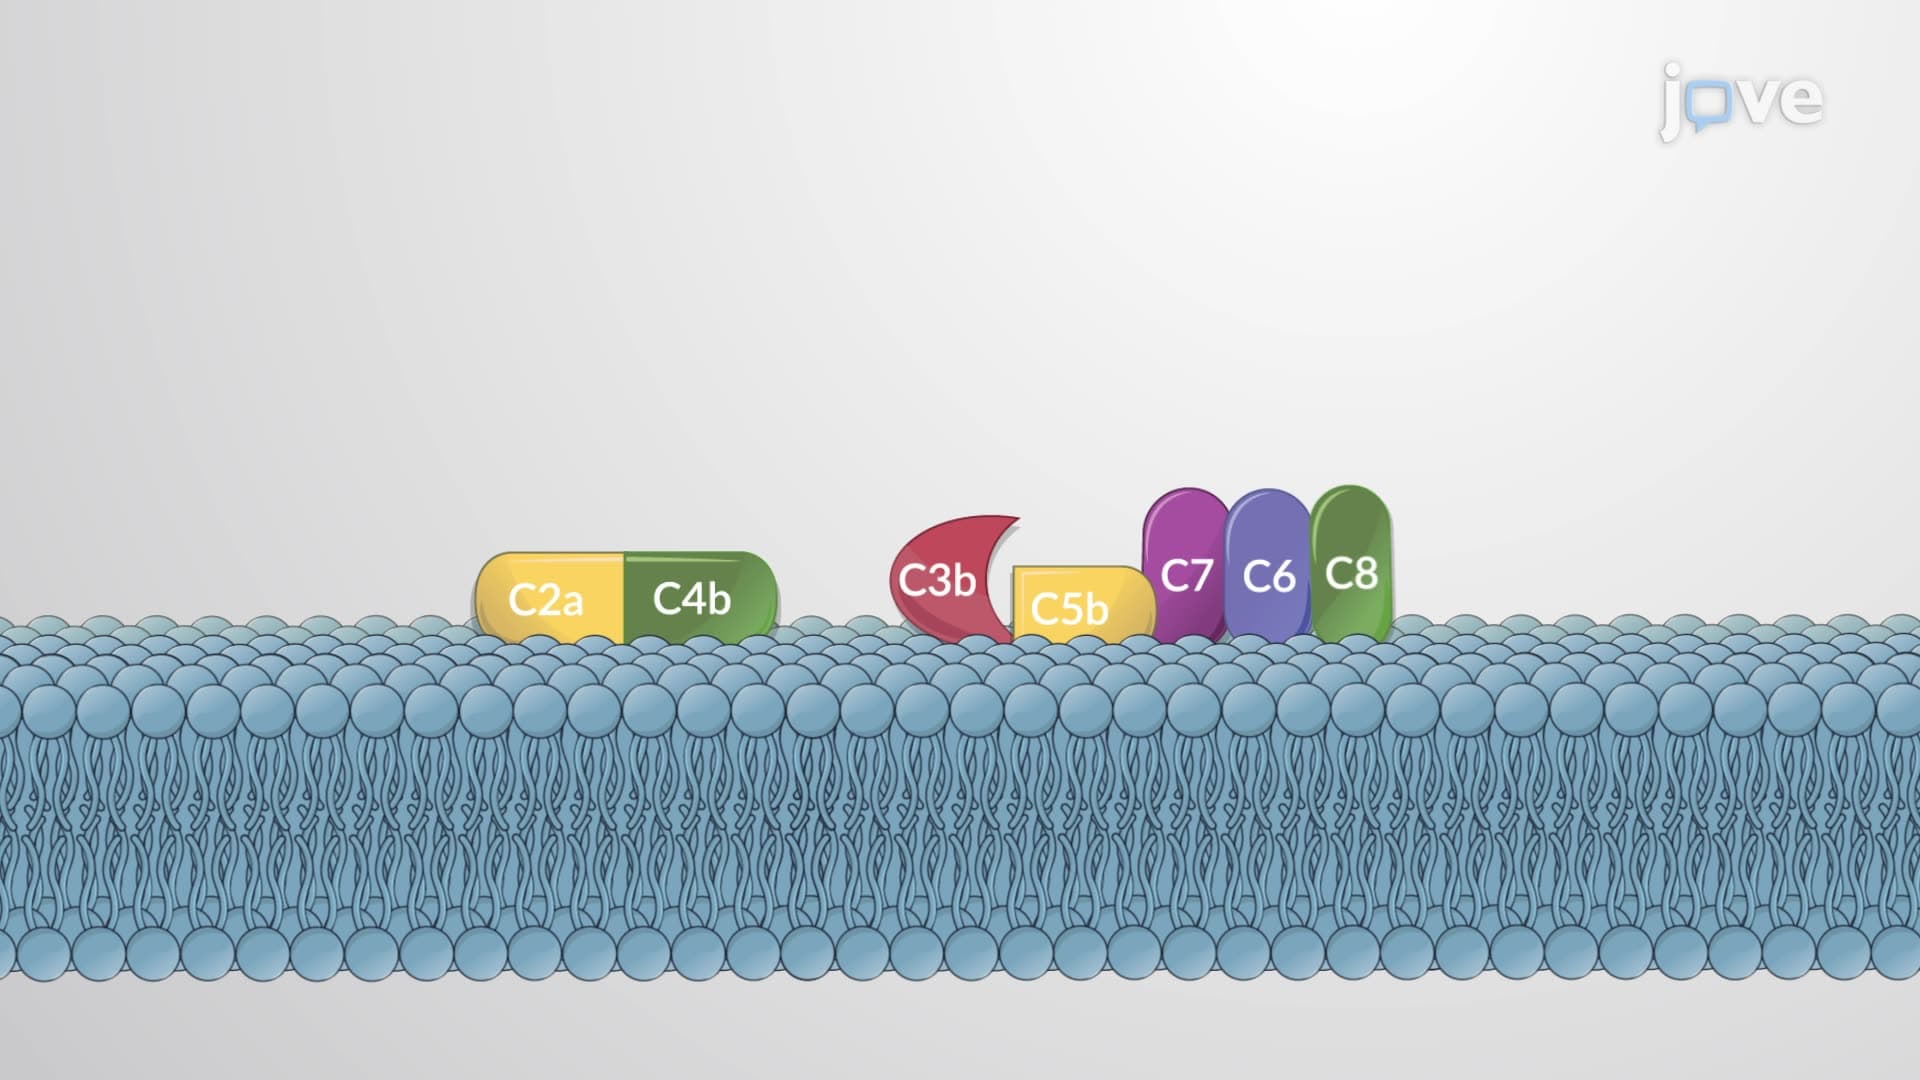
Complement System
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management