Gastric outlet obstruction possibly secondary to ulceration in a 2-year-old girl: a case report

Manabu Okawada1, Tadaharu Okazaki, Tsubasa Takahashi

  • 1Department of Pediatric General and Urogenital Surgery, Juntendo University School of Medicine, 2-1-1 Hongo, Bunkyo-ku, Tokyo 113-8421, Japan. okazakit@juntendo.ac.jp.

Cases Journal
|January 7, 2009
PubMed

Related Concept Videos

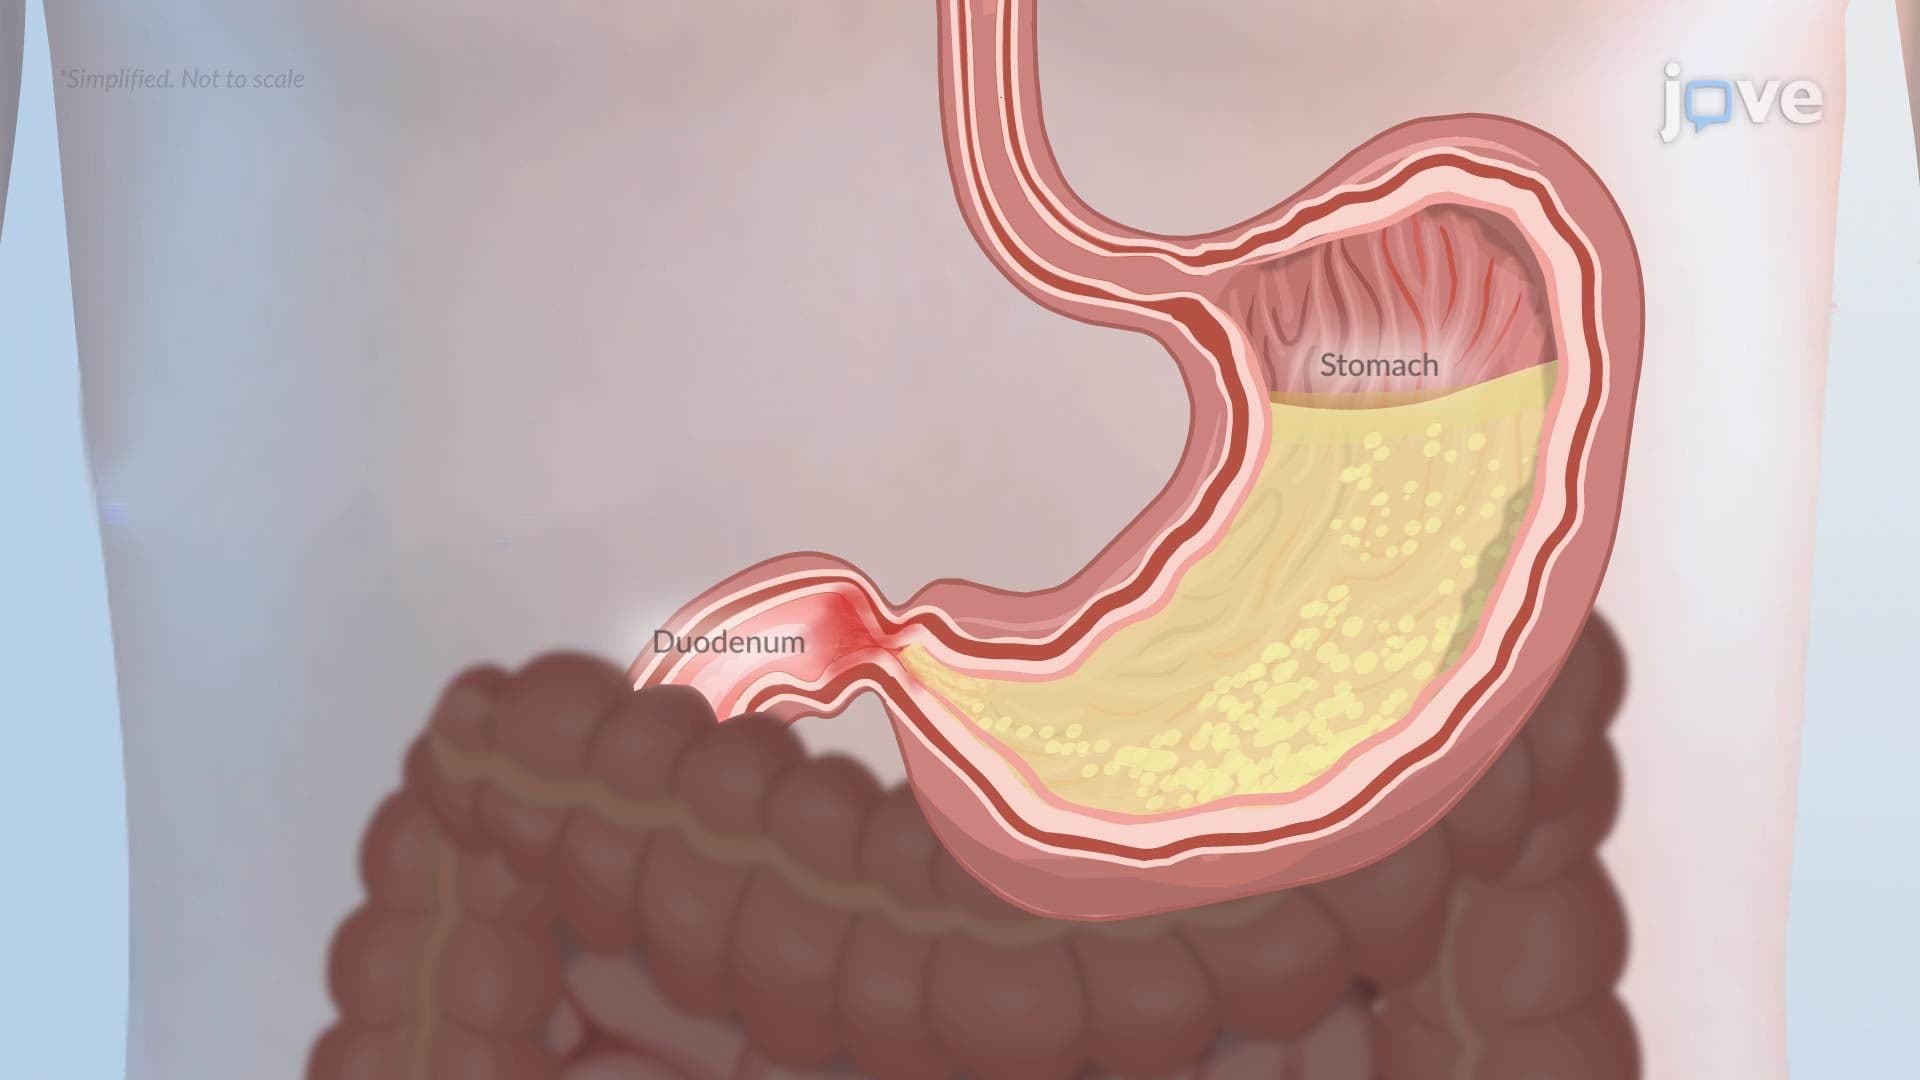
Pyloric Obstruction01:11

Pyloric Obstruction

Pyloric obstruction, also referred to as gastric outlet obstruction, is a condition characterized by narrowing or blockage at the pylorus—the muscular valve regulating the flow of stomach contents into the duodenum. When this passage becomes impaired, the stomach cannot effectively empty its contents into the small intestine. This disruption leads to a range of gastrointestinal symptoms, including early satiety, bloating, epigastric pain, postprandial nausea, persistent vomiting, and...
Peptic Ulcer Disease V: Surgical Management and Nursing Care01:25

Peptic Ulcer Disease V: Surgical Management and Nursing Care

Surgical management and nursing care are crucial in treating Peptic Ulcer Disease (PUD). Here is an organized and enhanced overview of the surgical interventions and the associated nursing care for PUD:
Surgical Interventions for Peptic Ulcer Disease
Peptic Ulcer Disease III: Clinical Manifestations and Complications01:25

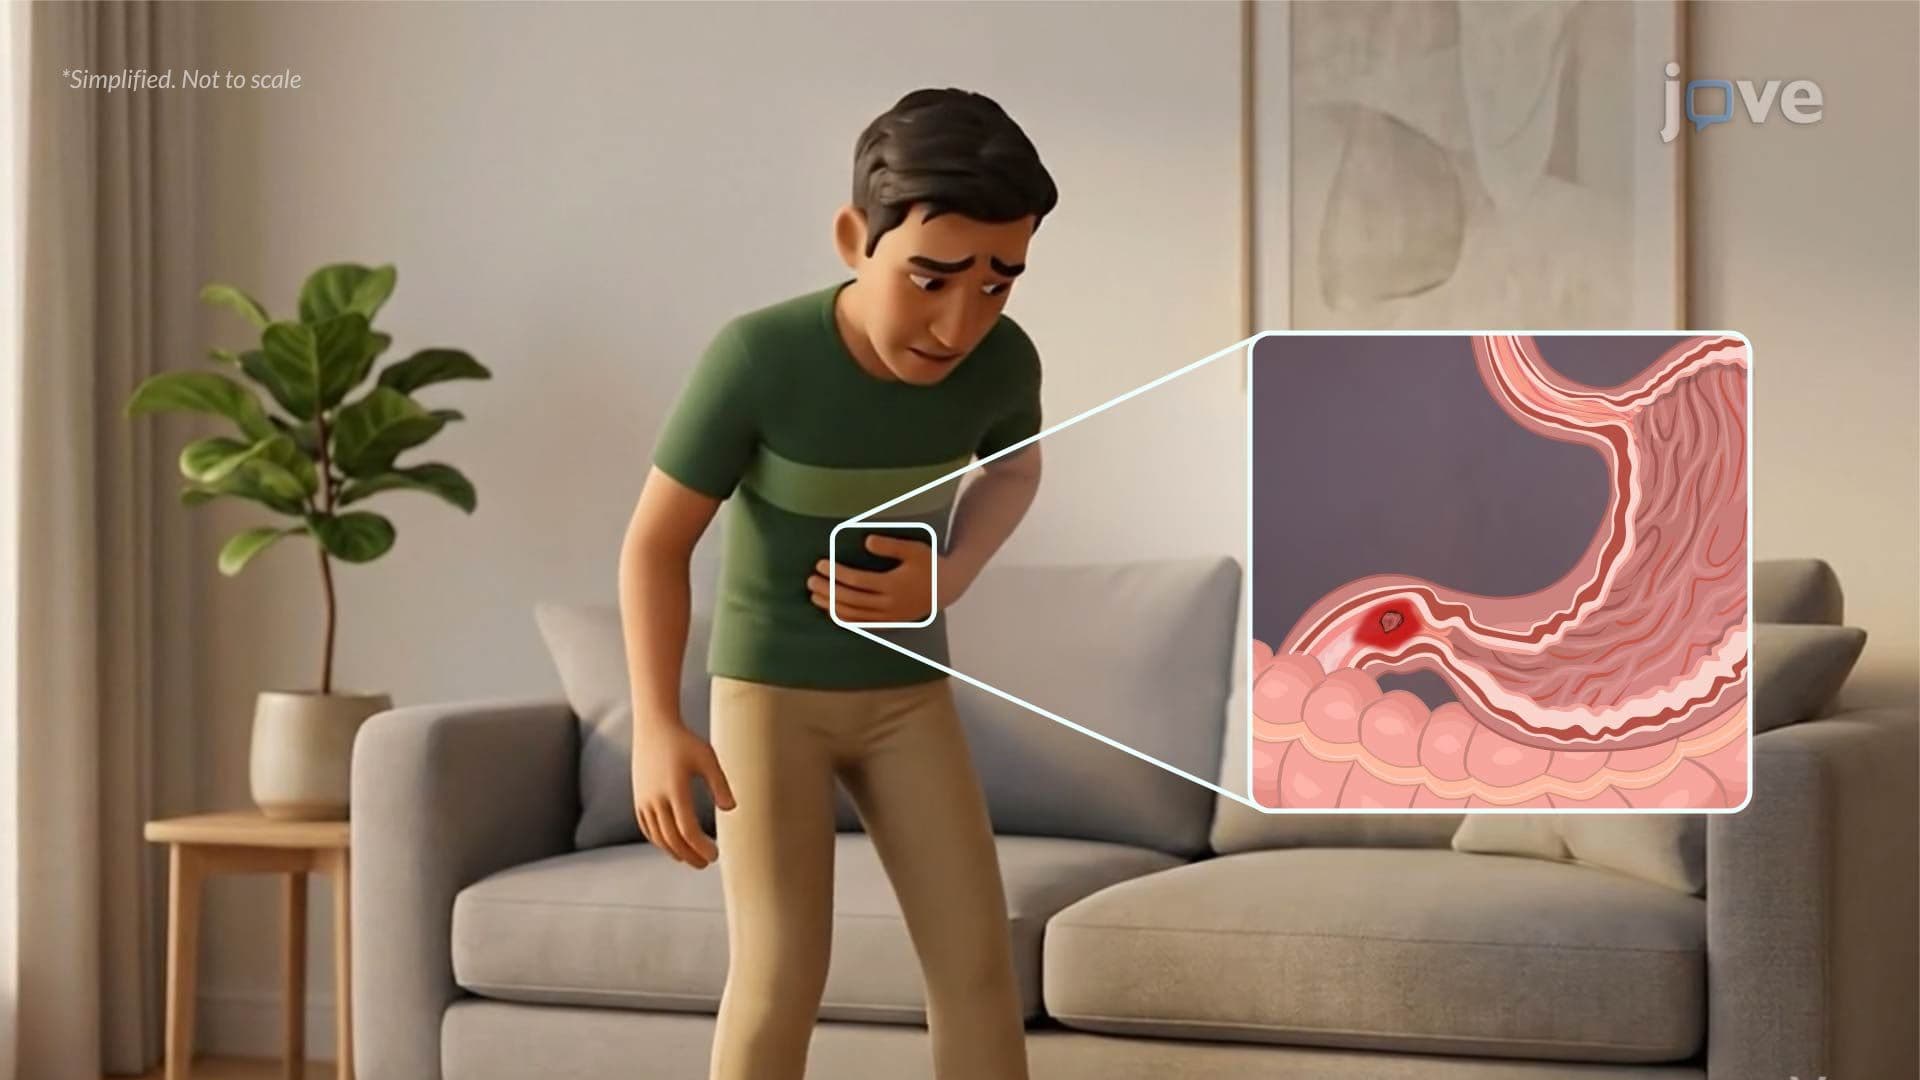
Peptic Ulcer Disease III: Clinical Manifestations and Complications

Duodenal UlcersDuodenal ulcers are the most common form of peptic ulcer disease, presenting with chronic, intermittent epigastric pain. Pain typically appears 2–3 hours after meals, especially when the stomach is empty, often waking patients at night. It is characteristically relieved by food or antacids (“pain–food–relief”). Some patients remain asymptomatic until complications like bleeding or perforation emerge, particularly with NSAID or anticoagulant use.Gastric UlcersGastric ulcers share...
Intestinal Obstruction II: Pathophysiology01:07

Intestinal Obstruction II: Pathophysiology

Intestinal obstruction triggers a series of physiological responses, starting with gas and fluid accumulation in the bowel segment proximal to the obstruction, leading to distension. This distended intestine compresses the diaphragm, hindering lung expansion and potentially leading to reduced respiratory effort, atelectasis, and pneumonia.To overcome the blockage, the gut intensifies contractions, causing colicky abdominal pain, nausea, and vomiting, which reduces fluid and food intake and...
Esophageal Strictures-II: Clinical Features and Management01:26

Esophageal Strictures-II: Clinical Features and Management

Patients with esophageal strictures often experience a range of symptoms. Initially, they may have difficulty swallowing solid foods, which can progress to include liquids. Additional symptoms may involve chest pain or discomfort, regurgitating food and fluids, heartburn, unintentional weight loss, coughing or choking during meals, and hoarseness.
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
Peptic Ulcer01:27

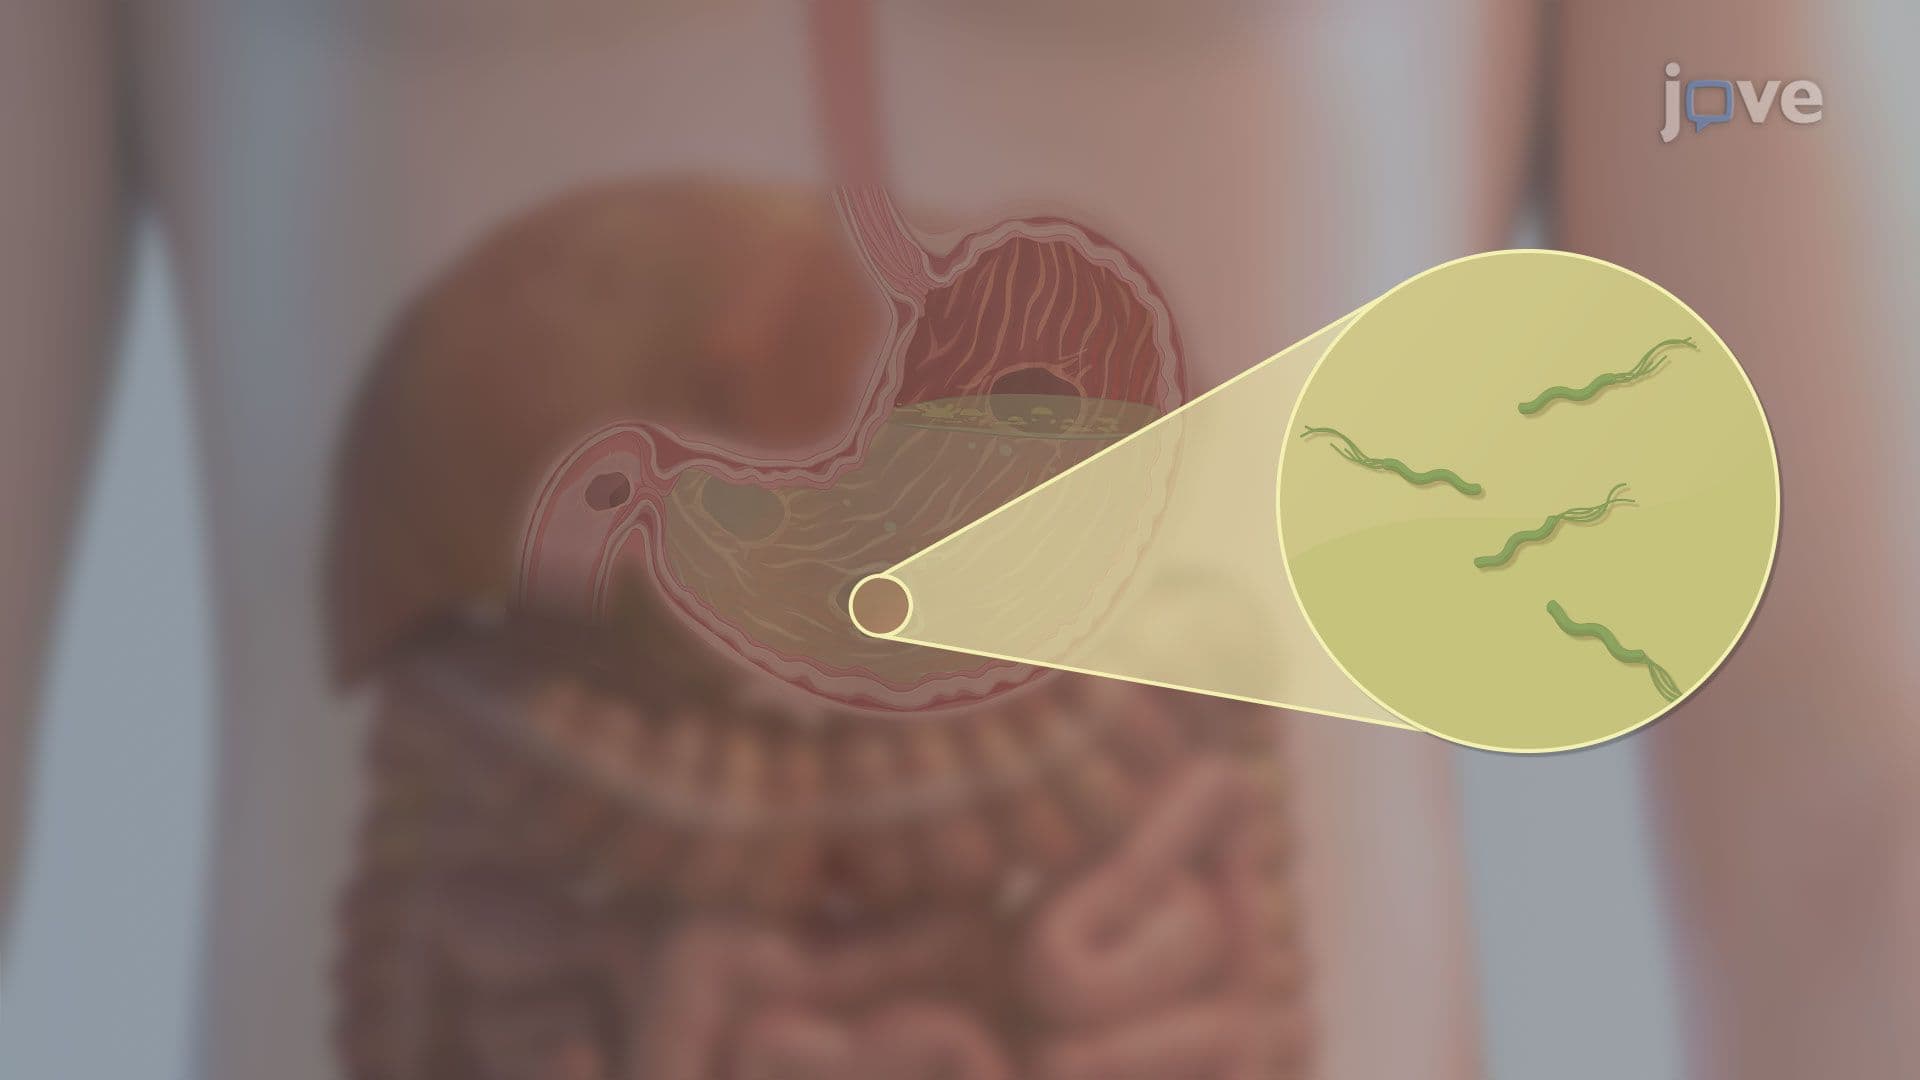
Peptic Ulcer

Peptic ulcers are erosive lesions of the gastric or duodenal lining, most commonly caused by Helicobacter pylori infection. This Gram-negative, helical bacterium has adapted to survive the stomach’s acidic environment by producing urease, which converts urea into ammonia and carbon dioxide. The ammonia neutralizes gastric acid in the bacterium’s immediate environment, allowing colonization of the gastric mucosa. H. pylori attaches to mucus-secreting epithelial cells, penetrates the mucus...