Related Experiment Video
Updated: Jun 26, 2026


Endoscopic Endonasal Trans-sphenoidal Approach: Minimally Invasive Surgery for Pituitary Adenomas
Published on: January 17, 2018
Coexpression of dopamine and somatostatin receptor subtypes in corticotroph adenomas
Christiaan de Bruin1, Alberto M Pereira, Richard A Feelders
1Department of Internal Medicine, Division of Endocrinology, Erasmus Medical Center, Rotterdam, The Netherlands. c.debruin@erasmusmc.nl

Context:
Previous studies have demonstrated the expression of somatostatin receptor subtypes (mainly sst(5)) and dopamine (DA) receptor subtypes (mainly D(2)) in smaller series of human corticotroph adenomas. In line with these findings, sst(5) and D(2)-targeting agents have already been used clinically in patients with Cushing's disease (CD) and have shown promising results in subsets of patients. To what extent these receptor subtypes are coexpressed within individual adenomas, is not known however.
Objective:
The aim of the study was to investigate the (co-)expression of both sst and DA receptors in a large series of human corticotroph adenomas.
Design:
We performed in vitro analysis of corticotroph adenoma tissue obtained via transsphenoidal adenomectomy.
Setting:
The study was conducted at two university medical centers.
Patients:
Adenoma tissue from 30 patients with CD was analyzed in this study.
Results:
Analyzed by quantitative RT-PCR, D(2) and sst(5) were significantly (co-) expressed in the majority (60%) of adenomas, whereas 23% of adenomas only expressed D(2), but not sst(5). The remaining 17% of adenomas did not significantly express either sst(5) or D(2). Overall, expression of sst(1-4) and D(4) was low to nondetectable. Corticotroph adenomas with invasive growth invariably showed loss of sst(5) and D(2) expression. Autoradiography revealed clear D(2) and/or SS-14 binding in a subset of cases, which correlated well with their respective mRNA data.
Conclusions:
Sst(5) and especially D(2) are highly expressed in the majority of human corticotroph adenomas, with coexpression of sst(5) and D(2) being a common phenomenon. These findings support the current studies with sst(5) and D(2)-targeting agents in patients with CD and highlight the rationale behind sst(5)-D(2) combination therapy.
Insights
Somatostatin receptor subtype 5 (sst5) and dopamine (DA) receptor D2 are frequently coexpressed in human corticotroph adenomas. This finding supports combination therapies targeting both sst5 and D2 receptors for Cushing's disease.
Area of Science:
- Endocrinology
- Molecular Biology
- Oncology
Background:
- Previous research indicated somatostatin receptor subtype 5 (sst5) and dopamine (DA) receptor D2 expression in human corticotroph adenomas.
- Clinical trials with sst5 and D2 targeting agents show promise for Cushing's disease (CD).
- The extent of coexpression of these receptors within individual adenomas remains unclear.
Purpose of the Study:
- To investigate the coexpression of somatostatin (sst) and dopamine (DA) receptors in a large cohort of human corticotroph adenomas.
- To determine the prevalence of sst5 and D2 receptor coexpression in these tumors.
Main Methods:
- In vitro analysis of human corticotroph adenoma tissue obtained from 30 patients with CD via transsphenoidal adenomectomy.
- Quantitative RT-PCR and autoradiography were utilized to assess receptor expression and binding.
Main Results:
- Dopamine (DA) receptor D2 and somatostatin receptor subtype 5 (sst5) were significantly coexpressed in 60% of adenomas.
- 23% of adenomas expressed D2 but not sst5, while 17% expressed neither.
- Invasive adenomas showed a loss of sst5 and D2 expression; receptor binding correlated with mRNA data.
Conclusions:
- Somatostatin receptor subtype 5 (sst5) and particularly dopamine (DA) receptor D2 are highly expressed in most human corticotroph adenomas.
- Coexpression of sst5 and D2 receptors is a common finding, supporting combination therapy for Cushing's disease.
- These results provide a strong rationale for developing sst5-D2 combination therapies for patients with CD.

Related Concept Videos
 01:19
Cushing Syndrome II: Pathophysiology
 01:26
Cushing Syndrome I: Introduction
 01:15
Receptor Downregulation in MVBs
The EGFR can initiate signaling pathways that lead to cell proliferation, migration, and differentiation. Overexpression of EGFR stimulates cells to proliferate. Excessive EGFR activation may...
 01:29
Chemotherapy-Induced Nausea and Vomiting: Dopamine Receptor Antagonists
Phenothiazines, such as prochlorperazine...
 01:31
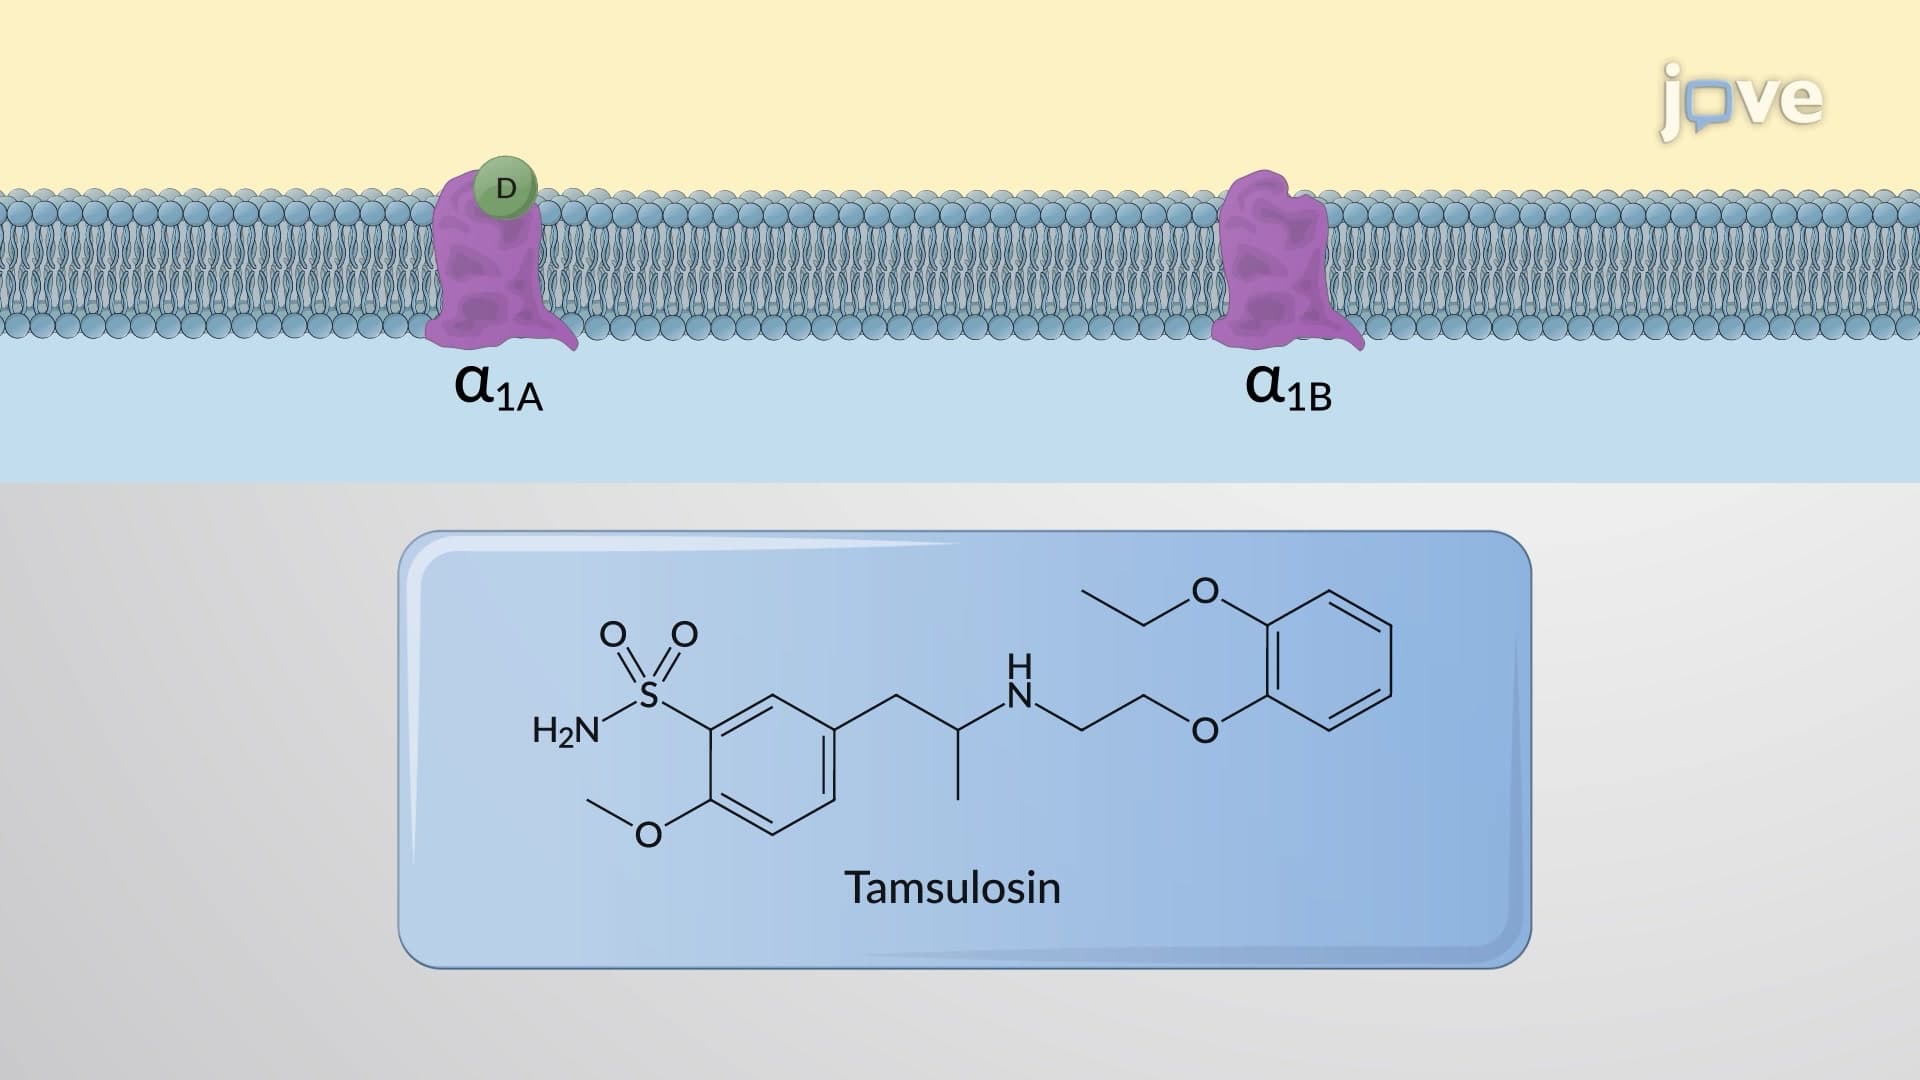
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:28
Drugs Affecting GI Tract Motility: Dopamine Receptor Antagonists