Related Experiment Video
Updated: Jun 26, 2026
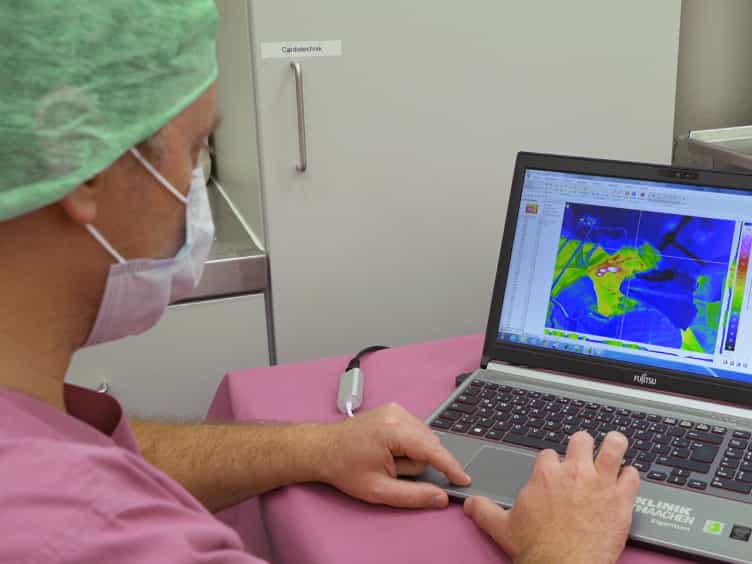
Assessment of Plasma Coagulation on Liver Tissue in a Large Animal Model In Vivo
Published on: August 4, 2018
Blood products, volume control, and renal support in the coagulopathy of liver disease
Curtis K Argo1, Rasheed A Balogun2
1University of Virginia, Department of Medicine, Division of Gastroenterology and Hepatology, Box 800708, Charlottesville, VA, USA.

Plasma-based products are commonly used in patients who have chronic liver disease to treat perceived coagulopathy despite unproven efficacy and potentially severe risks, such as transfusion-related acute lung injury, which carries a high mortality rate. Moreover, volume expansion may acutely worsen portal hypertension and increase bleeding from the collateral portal vascular bed. Although factor replacement therapy may be warranted in selected situations, its use should be restricted because of the limitations of target tests, such as international normalized ratio, which poorly reflects presence of bleeding diatheses in patients who have cirrhosis. Renal replacement therapies are frequent adjuncts in patients who have cirrhosis and are acutely decompensated, and may correct uremia-related bleeding diathesis and assist in controlling vascular volume, although they are generally limited to use as a bridge to liver transplantation. Novel extracorporeal therapies are emerging and may also have significant interaction with the hemostatic system. Volume contraction and blood conservation therapies are relatively new and promising approaches to reduce use of blood products in liver transplantation.
Plasma-based products are commonly used in patients who have chronic liver disease to treat perceived coagulopathy despite unproven efficacy and potentially severe risks, such as transfusion-related acute lung injury, which carries a high mortality rate. Moreover, volume expansion may acutely worsen portal hypertension and increase bleeding from the collateral portal vascular bed. Although factor replacement therapy may be warranted in selected situations, its use should be restricted because of the limitations of target tests, such as international normalized ratio, which poorly reflects presence of bleeding diatheses in patients who have cirrhosis. Renal replacement therapies are frequent adjuncts in patients who have cirrhosis and are acutely decompensated, and may correct uremia-related bleeding diathesis and assist in controlling vascular volume, although they are generally limited to use as a bridge to liver transplantation. Novel extracorporeal therapies are emerging and may also have significant interaction with the hemostatic system. Volume contraction and blood conservation therapies are relatively new and promising approaches to reduce use of blood products in liver transplantation.
Related Concept Videos
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 02:45
Blood Transfusion and Agglutination
History
The history of blood transfusion dates back to the 17th century, when early attempts were made in animals. In 1818 James Blundell, a British doctor, performed the first successful human blood transfusion. Later in 1900, Karl...
 01:30
Venous Thrombosis IV: Nursing Management
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...