Related Experiment Video
Updated: Jun 26, 2026
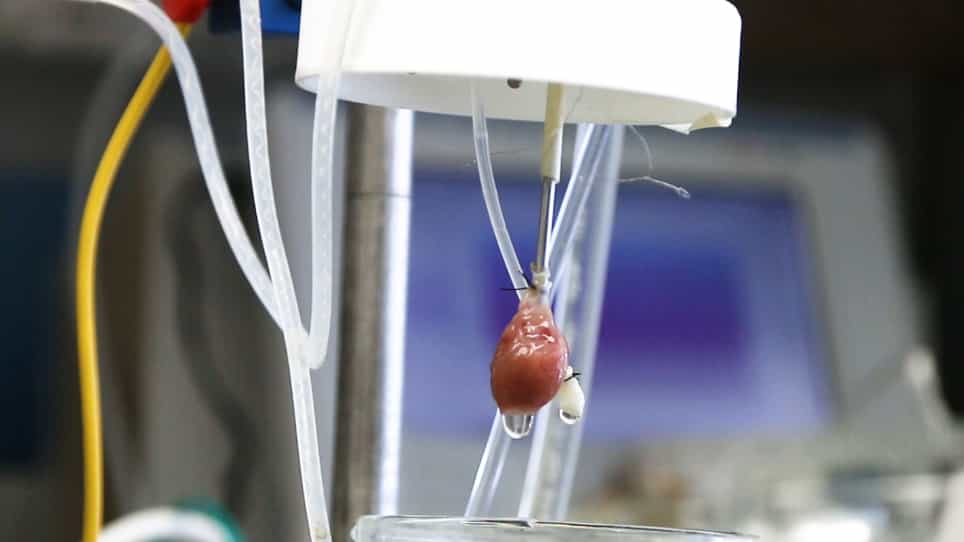

Pre-clinical Model of Cardiac Donation after Circulatory Death
Published on: August 2, 2019
Is repeated administration of blood-cardioplegia really necessary?
Tamer Ghazy1, Omar Allham, Ahmed Ouda
1Department of Cardiac Surgery, Dresden Heart Center, Dresden Technical University, Germany. tamer_ghazy@hotmail.com

Insights
Single-shot warm blood cardioplegia may be sufficient for cardiac surgery, potentially eliminating the need for repeated doses. This approach showed benefits in reducing postoperative myocardial infarction but had drawbacks in intraoperative inotropic support and postoperative dialysis.
Area of Science:
- Cardiovascular Surgery
- Cardioplegia
- Cardiac Anesthesia
Background:
- Repeated administration of warm blood cardioplegia is a standard in cardiac surgery.
- The necessity of repeated doses every 20 minutes is questioned.
- Advancements in surgical techniques may alter cardioplegia requirements.
Purpose of the Study:
- To evaluate the necessity of repeated warm blood cardioplegia administration.
- To compare outcomes between single-shot and repeated cardioplegia.
- To analyze the safety and efficacy of single-shot cardioplegia in cardiac procedures.
Main Methods:
- Retrospective analysis of 4014 cardiac surgery patients (2001-2006).
- Modified Calafiore warm blood-cardioplegic solution utilized.
- Multivariate logistic regression analysis comparing single-shot (1708 patients) vs. repeated cardioplegia.
Main Results:
- No significant difference in mortality, intraoperative/postoperative IABP, or postoperative arrhythmia.
- Single-shot cardioplegia associated with reduced postoperative myocardial infarction (P=0.003).
- Increased need for intraoperative inotropics (P=0.038) and postoperative dialysis (P=0.015) observed with single-shot.
Conclusions:
- The initial dose of warm blood cardioplegia may provide adequate protection beyond 20 minutes.
- Single-shot cardioplegia may be sufficient given decreasing cross-clamp times.
- Further research needed to balance benefits and risks of single-shot cardioplegia.
Abstract:
The aim of this work was to question the necessity of repeated administration of warm blood cardioplegia in modern cardiac surgery. A consecutive series of 4014 patients underwent cardiosurgical procedures in the period from January 2001 to December 2006 in our centre, where modified Calafiore warm blood-cardioplegic solution was used. 1708 patients received a single shot of cardioplegia instead of repeated blood cardioplegia (every 20 min). A multivariate analysis was performed using logistic regression models to reveal the statistical significance of the effect of single-shot cardioplegia on the occurrence of: death, intraoperative need of inotropics, intraoperative intra-aortic balloon pump (IABP), postoperative infarction, arrhythmia, postoperative need for inotropics and postoperative IABP. The results showed statistical insignificance concerning mortality (P=0.704), intraoperative IABP (P=0.247), postoperative inotropics (P=0.273), postoperative IABP (P=0.678), postoperative arrhythmia (P=0.661). Single-shot cardioplegia showed a positive effect concerning postoperative myocardial infarction (P=0.003). However, it showed an unfavourable effect concerning intraoperative inotropics (P=0.038) and postoperative dialysis (P=0.015). The clinical safety of the first shot of warm blood cardioplegia might be exceeding 20 min. In the light of increasingly short cross-clamping time, the safety of the first shot might be long enough to cover the whole cross-clamping time.

Related Concept Videos
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:29
Cardiomyopathy V: Interprofessional Care
 01:23
Cardiopulmonary Resuscitation III: AED Use
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:21
Cardiopulmonary Resuscitation I: Adult
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management