Related Experiment Video
Updated: Jun 26, 2026
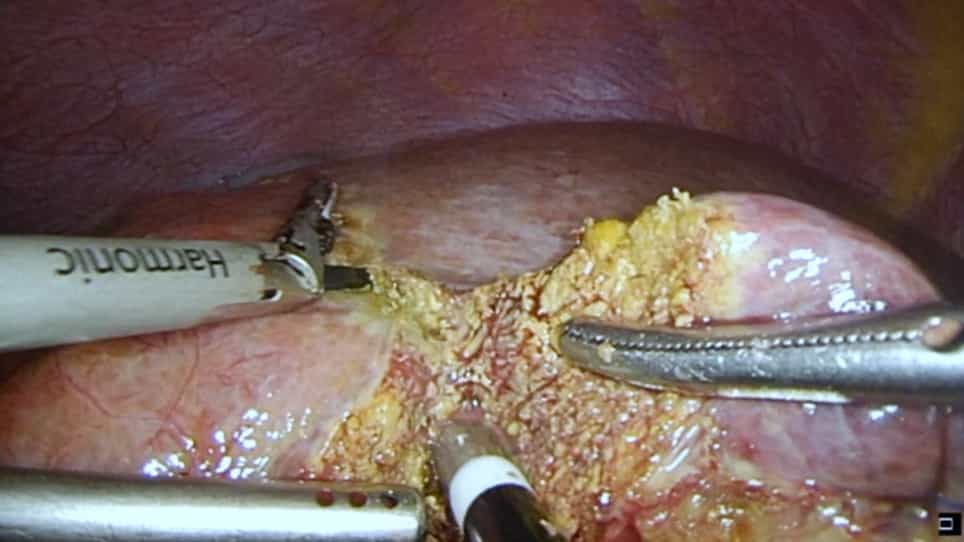
Application of Hemostatic Devices in Laparoscopic Hepatectomy
Published on: April 19, 2022
Beyond NOTES: randomized controlled study of different methods of flexible endoscopic hemostasis of artificially
A Fritscher-Ravens1, A Ghanbari, C Holland
1Department of Academic Medical and Surgical Gastroenterology, Homerton University Hospital, London, UK. fri.rav@btopenworld.com

Background And Study Aim:
Significant hemorrhage is a likely complication during natural orifice transluminal endoscopic surgery (NOTES) procedures. We tested three different prototype devices (involving endoscopic suturing, monopolar forceps, and forced argon plasma coagulation [FAPC]) for treatment of acute bleeding in a survival animal model.
Method:
Using transgastric access (TGA) or transvaginal access (TVA), the endoscope was introduced into the peritoneal cavity and the first side-branch of the gastroepiploic artery (1aGE) was cut before the different hemostatic methods were applied.
Results:
Sutures could not be placed quickly enough before vision was inhibited. With monopolar forceps via TGA, the time to control bleeding was 10 - 140 s (mean 58 +/- 41 s) and with TVA it was 25 - 115 s (mean 57 +/- 26 s) (P = 0.54). It was not possible to stop the bleeding in 4/6 animals with TGA access and in 3/6 with TVA, and FAPC was needed to entirely stop it, taking a further 10 - 280 s (TGA mean 126 +/- 90 s, 34 - 242 s; TVA mean 152 +/- 61 s; P = 0.42). Using FAPC with TGA took 4 - 72 s (mean 28 +/- 20 s) to stop the bleeding, and 16 - 41 s (mean 24 +/- 9.4 s) with TVA ( P = 0.64). As the FAPC technique was relatively so much better, additional treatment of bleeding from the main gastroepiploic artery (aGe) was added in four cases for each method of access; this was successful but took significantly longer, with TGA at 10 - 260 s and with TVA at 30 - 172 s (means 98 +/- 82, 117 +/- 54 s, respectively; not significant).
Conclusion:
Regarding the three methods tested, the new prototype FAPC device allowed hemostasis of notable bleeding from a major vessel even more quickly than forceps coagulation of a bleeding side branch. More studies are needed to further explore this potentially very valuable tool.
