Related Experiment Video
Updated: Jun 26, 2026
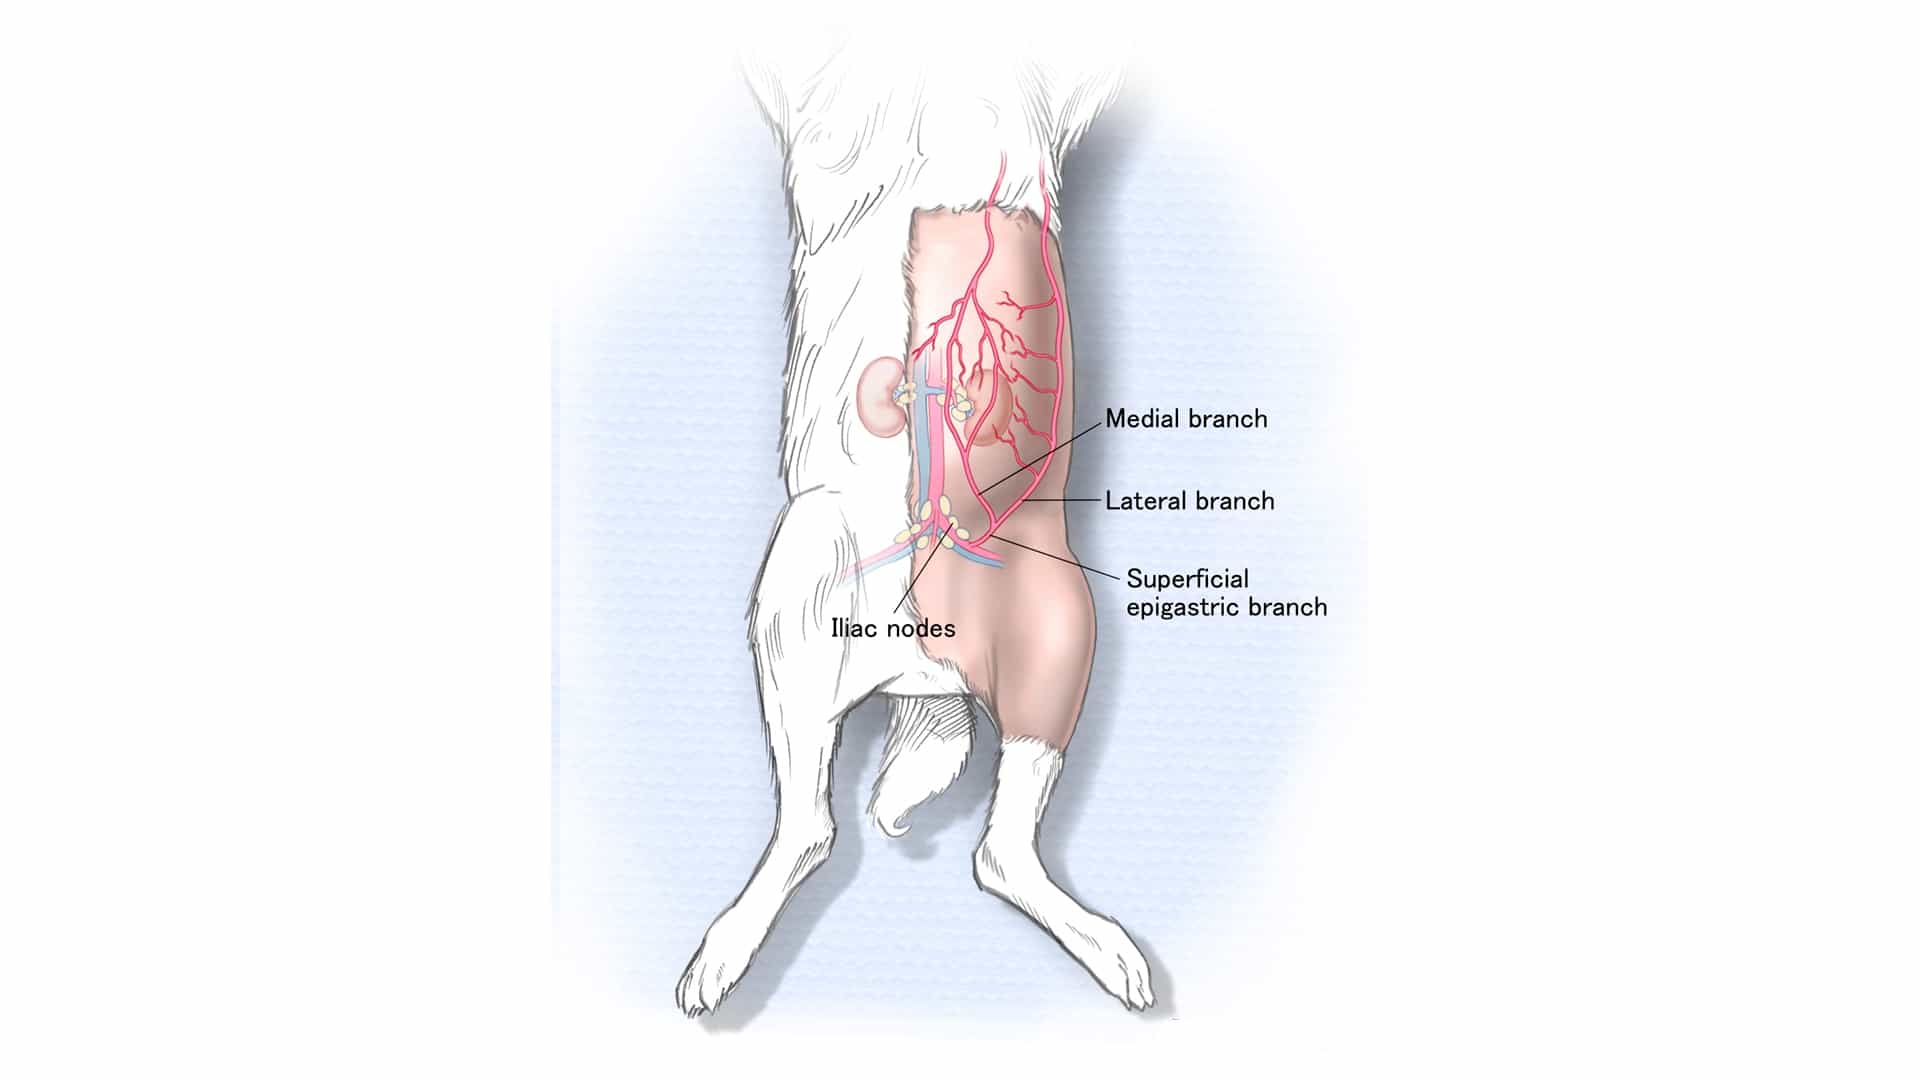
The Superficial Inferior Epigastric Artery Fascia Flap for Nerve Reconstruction in Rabbits
Published on: June 13, 2025
[The distally based sural neurocutaneous island flap for coverage of soft-tissue defects on the distal lower leg,
Lothar L J Rudig1, Erol Gercek, Martin H Hessmann
1Klinik für Unfall-, Hand- und Wiederherstellungschirurgie, GPR-Klinikum Rüsselsheim, Rüsselsheim. rudig@gp-ruesselsheim.de

Objective:
Stable coverage of soft-tissue defects in the critical regions of the distal lower leg, ankle and heel by avoidance of a microsurgically transplanted free flap.
Indications:
Soft-tissue defects < or = 10 cm in diameter--either by trauma or complications (skin necrosis, infection)--on the distal lower leg, ankle or heel with exposed osseous, tendinous or articular structures including high-risk patients (diabetes mellitus type 1/2 and/or arterial vascular disease including stage IIb, not capable of improvement).
Contraindications:
Relative: diameter of defect > 10 cm. Absolute: critical ischemia (arterial vascular disease stages III and IV).
Surgical Technique:
Outlining of the sural island flap directly over the small saphenous vein. Fasciocutaneous flap elevation proceeding in a proximal-distal direction. Lipofascial dissection of the 3 cm wide and up to 15 cm long neurovascular pedicle after longitudinal skin incision starting at the distal border of the island flap and running distally. Point of pedicle rotation 5 cm above the tip of the fibula. Flap passage into the defect through subcutaneous tunnel or after incision of the soft tissue between defect and donor site. Skin closure over region of pedicle dissection, meshed skin grafting of donor site.
Postoperative Management:
Immobilization of the lower leg in a well-padded cast over a period of about 10 days.
Results:
In a retrospective study, eleven out of twelve patients (including six high-risk patients) with a distally based sural neurocutaneous flap were examined on average 3.7 years postoperatively. The mean age was 54.9 years (28-80 years). A stable coverage of the defect was achieved in all twelve patients. In ten of twelve sural flaps the defect site was closed by primary wound healing, additional procedures were necessary in two cases (meshed skin grafting of flap border, excision of skin necrosis). All patients examined were satisfied with the result of the primary operative target, the stable coverage of the defect. Stated disadvantages were loss of sensation in the area of sural nerve function (four times), aesthetic impairment (twice), and pain resulting from sural nerve neuroma above donor site (once).
Related Concept Videos
 01:31
Diabetic Foot Ulcer
 01:11
Pulse Assessment Sites
 01:22
Burn Injuries
The damage results in the death of skin cells, which can lead to a massive loss of fluid. Dehydration, electrolyte imbalance, and renal and circulatory failure follow, which can be fatal. Burn patients are treated with intravenous fluids to offset...
 01:19
Clinical Applications of Epidermal Stem Cells