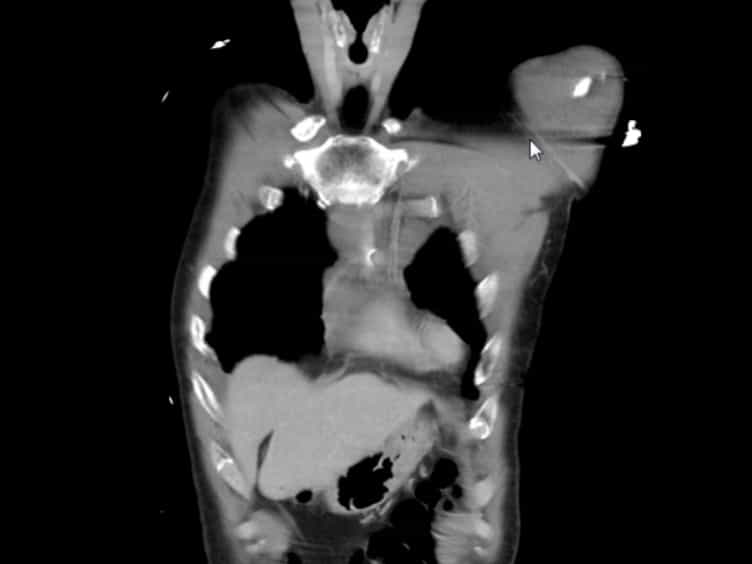

[Fractures of sternal end of the clavicle--current concept review]
J Bartonícek1, V Fric, L Lunácek
1Ortopedicko-traumatologická klinika 3. LF UK a FNKV, Praha-Vinohrady. bartonic@fnkv.cz

Insights
Medial clavicle fractures require careful diagnosis, often needing CT scans. Non-displaced fractures are treated non-operatively, while displaced fractures may benefit from cerclage fixation.
Area of Science:
- Orthopedic Surgery
- Traumatology
Context:
- Medial clavicle fractures present diagnostic challenges.
- Accurate diagnosis necessitates advanced imaging like CT scans with 3D reconstruction.
Purpose:
- To review diagnostic and treatment strategies for medial clavicle fractures.
- To highlight optimal fixation methods and contraindications.
Summary:
- Non-displaced medial clavicle fractures are managed non-operatively.
- Displaced fractures, especially in active individuals, warrant consideration for operative treatment.
- Cerclage fixation is recommended; K-wires are contraindicated.
Impact:
- Improved diagnostic accuracy through advanced imaging.
- Guidance on surgical intervention for displaced fractures.
- Emphasis on cerclage for optimal fixation outcomes.
Abstract:
Fractures of the medial end of the clavicle are still an outstanding issue with only minimum information available. Their diagnosis requires a special care both in isolated fractures of the clavicle and in polytrauma. An accurate diagnosis is impossible without CT scanning, preferably with a 3D reconstruction. Non-displaced fractures are indicated for non-operative treatment. In displaced fractures, sustained particularly by younger or active individuals, operative treatment should be considered. Best suitable for fixation is a cerclage, K-wires are strictly contraindicated. Formulation of a more specific opinion on the method of treatment, long-term outcomes and complications will be possible only on the basis of a greater number of reported cases.

Related Concept Videos
 01:24
Flail Chest-I
Flail chest is a severe and potentially life-threatening condition characterized by the fracture of three or more adjacent ribs in multiple places. It is most commonly caused by direct impacts and trauma, such as motor vehicle accidents or injuries from a steering wheel impact. It can also occur due to falls in elderly individuals with osteoporosis, or assaults involving sharp objects.
Pathophysiology
The pathophysiology of flail chest is complex, involving fractures of...
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the procedure...
 01:17
The Thoracic Cage: Sternum
The sternum is the elongated bony structure on the anterior side of the thoracic cage. It consists of three parts: the manubrium, the body, and the xiphoid process.
 01:27
Growth of Cartilage and Bone Tissue
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...