A weight-based formula for tracheal tube size in children
Related Experiment Video
Updated: Jun 26, 2026

A Novel Rescue Technique for Difficult Intubation and Difficult Ventilation
Published on: January 17, 2011
Naveen Eipe1, Nicholas Barrowman, Hilary Writer
1Department of Anesthesiology, Children's Hospital of Eastern Ontario, Ottawa, Ontario, Canada. neipe@cheo.on.ca

Insights
The age-based formula (ABF) is more accurate than the weight-based formula (WBF) for predicting tracheal tube (TT) size in children. However, the WBF may be useful for a specific subset of patients where the ABF is inaccurate.
Area of Science:
- Pediatric Anesthesiology
- Medical Device Sizing
- Clinical Formula Validation
Background:
- Accurate tracheal tube (TT) size selection is critical for pediatric airway management.
- Conventional formulas for estimating TT size are primarily age-based.
- The efficacy of alternative weight-based formulas (WBF) requires further investigation.
Purpose of the Study:
- To evaluate a weight-based formula (WBF) for uncuffed oral tracheal tube (TT) sizing in children.
- To compare the predictive accuracy of the WBF against the conventional age-based formula (ABF).
Main Methods:
- Retrospective analysis of pediatric patient data, recording age, weight, and actual TT size used.
- Comparison of actual TT sizes with predicted sizes derived from both ABF and WBF.
- Statistical analysis using Pearson's correlation coefficient and measures of agreement.
Main Results:
- The age-based formula (ABF) demonstrated higher accuracy (51.3%) compared to the weight-based formula (WBF) (44.8%) in predicting tracheal tube sizes (P=0.01).
- Pearson's correlation coefficients indicated moderate agreement between age and actual TT size (0.77) and weight and actual TT size (0.70).
- Measures of agreement were higher for ABF (0.35) than for WBF (0.27), with statistically significant differences.
Conclusions:
- The conventional age-based formula (ABF) is statistically superior to the weight-based formula (WBF) for estimating tracheal tube size in this pediatric cohort.
- The WBF may offer accurate predictions for a specific subset of patients for whom the ABF is less effective.
- Further research may explore hybrid or refined formulas for improved tracheal tube sizing accuracy.
Objective:
Age (in years) of the child has conventionally been used in formulae to estimate the tracheal tube (TT) size. The objective of this retrospective study was to test a weight-based formula (WBF) for uncuffed oral TT in children and compare it with the conventional age-based formula (ABF).
Methods:
The patient's age, weight, and size of TT internal diameter (ID) were recorded. For comparative analysis, the actual TT size used was compared with predicted TT size, calculated using both the standard ABF [ID = age (years)/4 + 4 mm] and the WBF [ID = weight (kg)/10 + 3.5 mm].
Results:
The Pearson's correlation coefficient for age and actual TT size used was 0.77 (95% CI: 0.74-0.80) and between weight and actual TT used was 0.70 (95% CI: 0.66-0.74). The ABF correctly predicted 51.3% of TT sizes while the WBF correctly predicted 44.8% of TT sizes (P = 0.01). The measures of agreement between the actual and predicted TT size were 0.35 and 0.27 for the ABF and WBF respectively. The difference between the percentages of paired predictions for the ABF and WBF was statistically significant (P < 0.001) suggesting that, when correctly predicting the actual tube size used, the WBF functions for a different subset of the patient cohort than the ABF.
Conclusions:
This study suggests that in this patient cohort, the WBF is statistically inferior to the conventional ABF. However, our findings also suggest that the WBF may correctly predict TT sizes in a subset of patients in whom the ABF is inaccurate.
Related Concept Videos
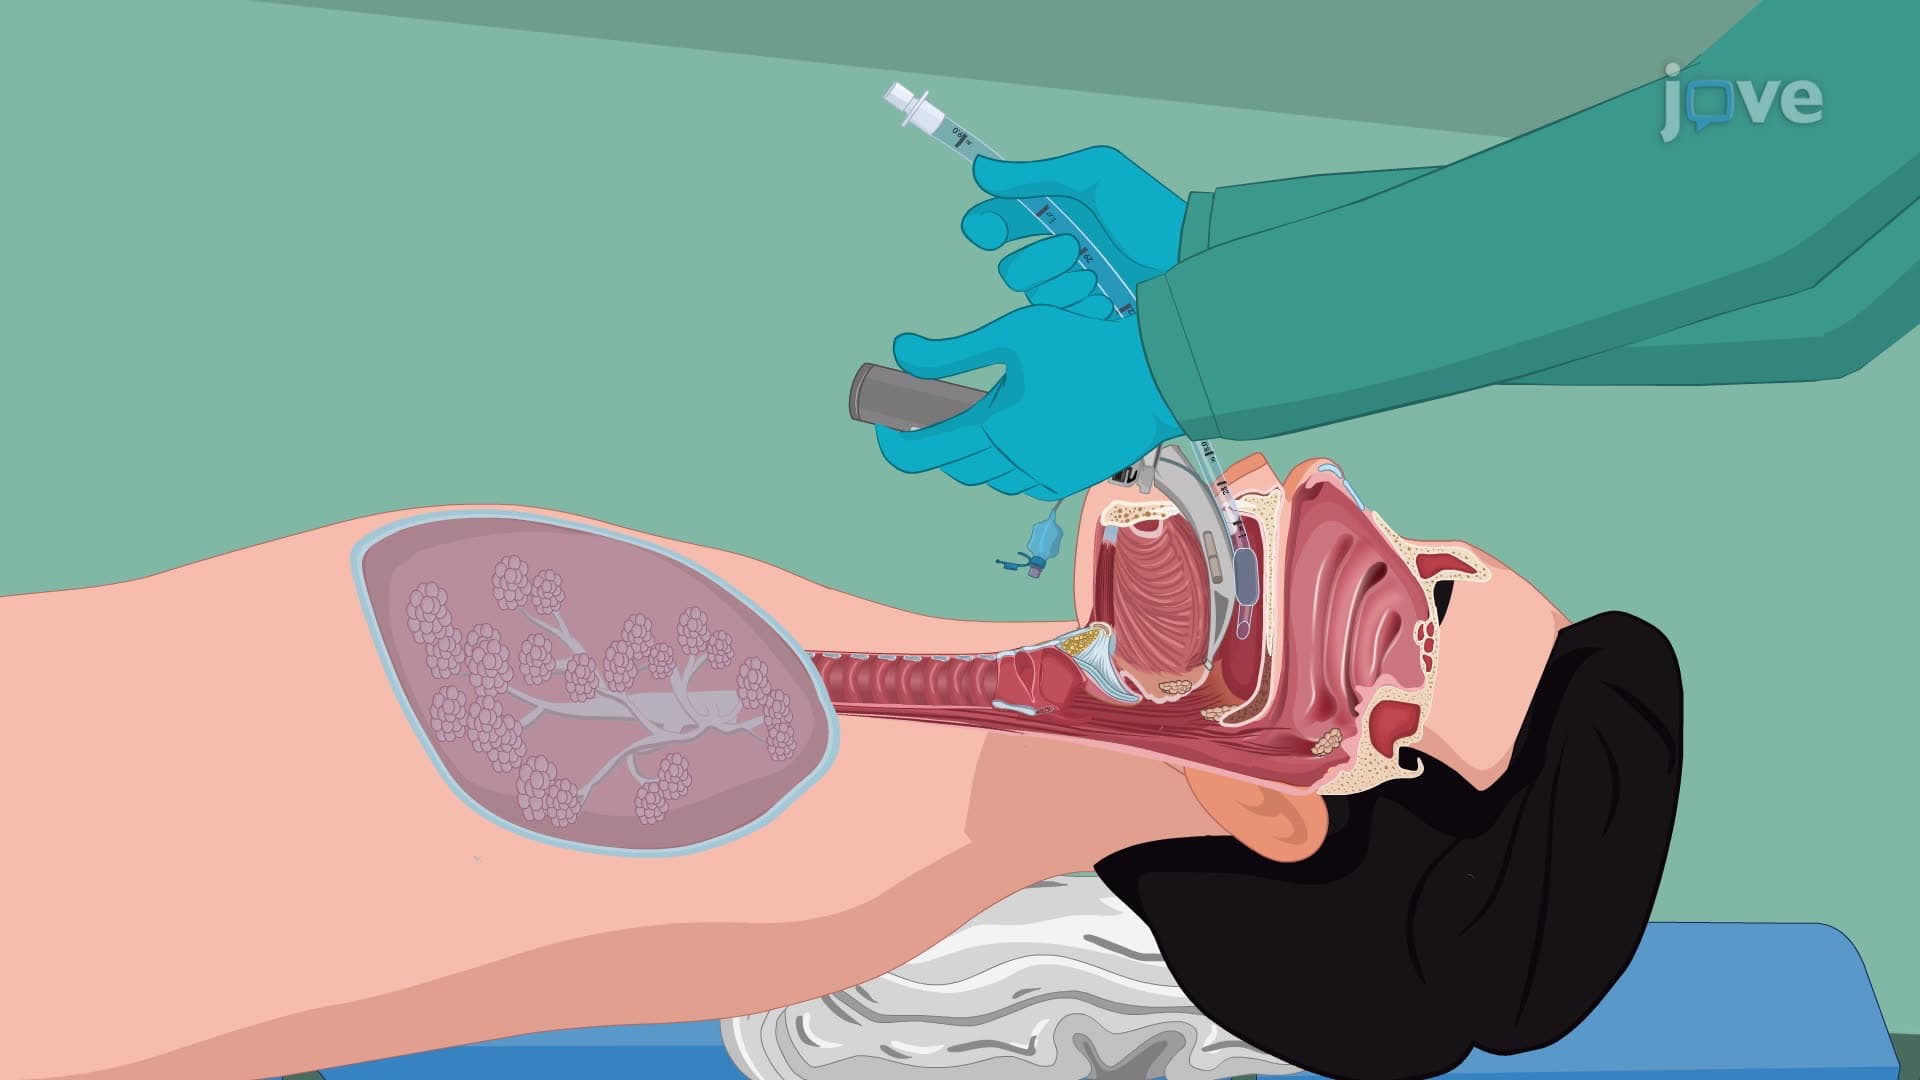 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
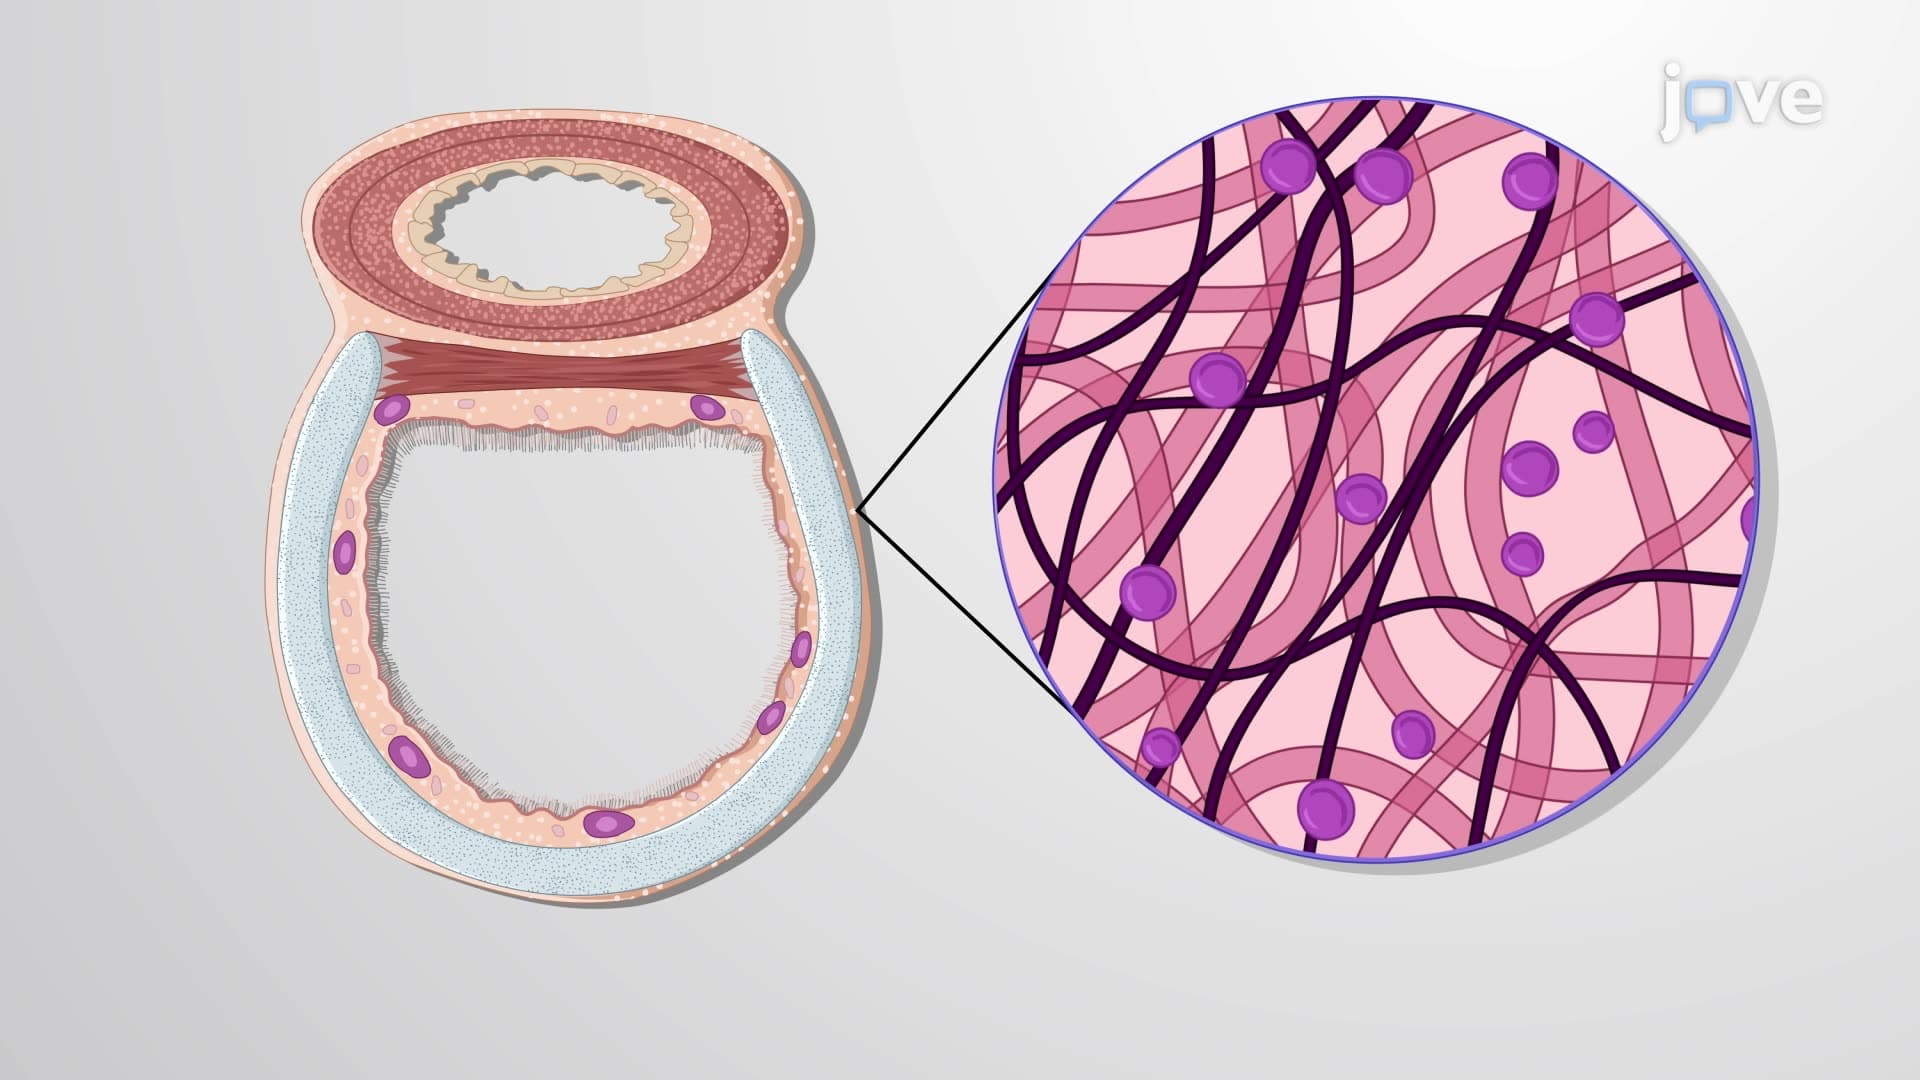 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of the...
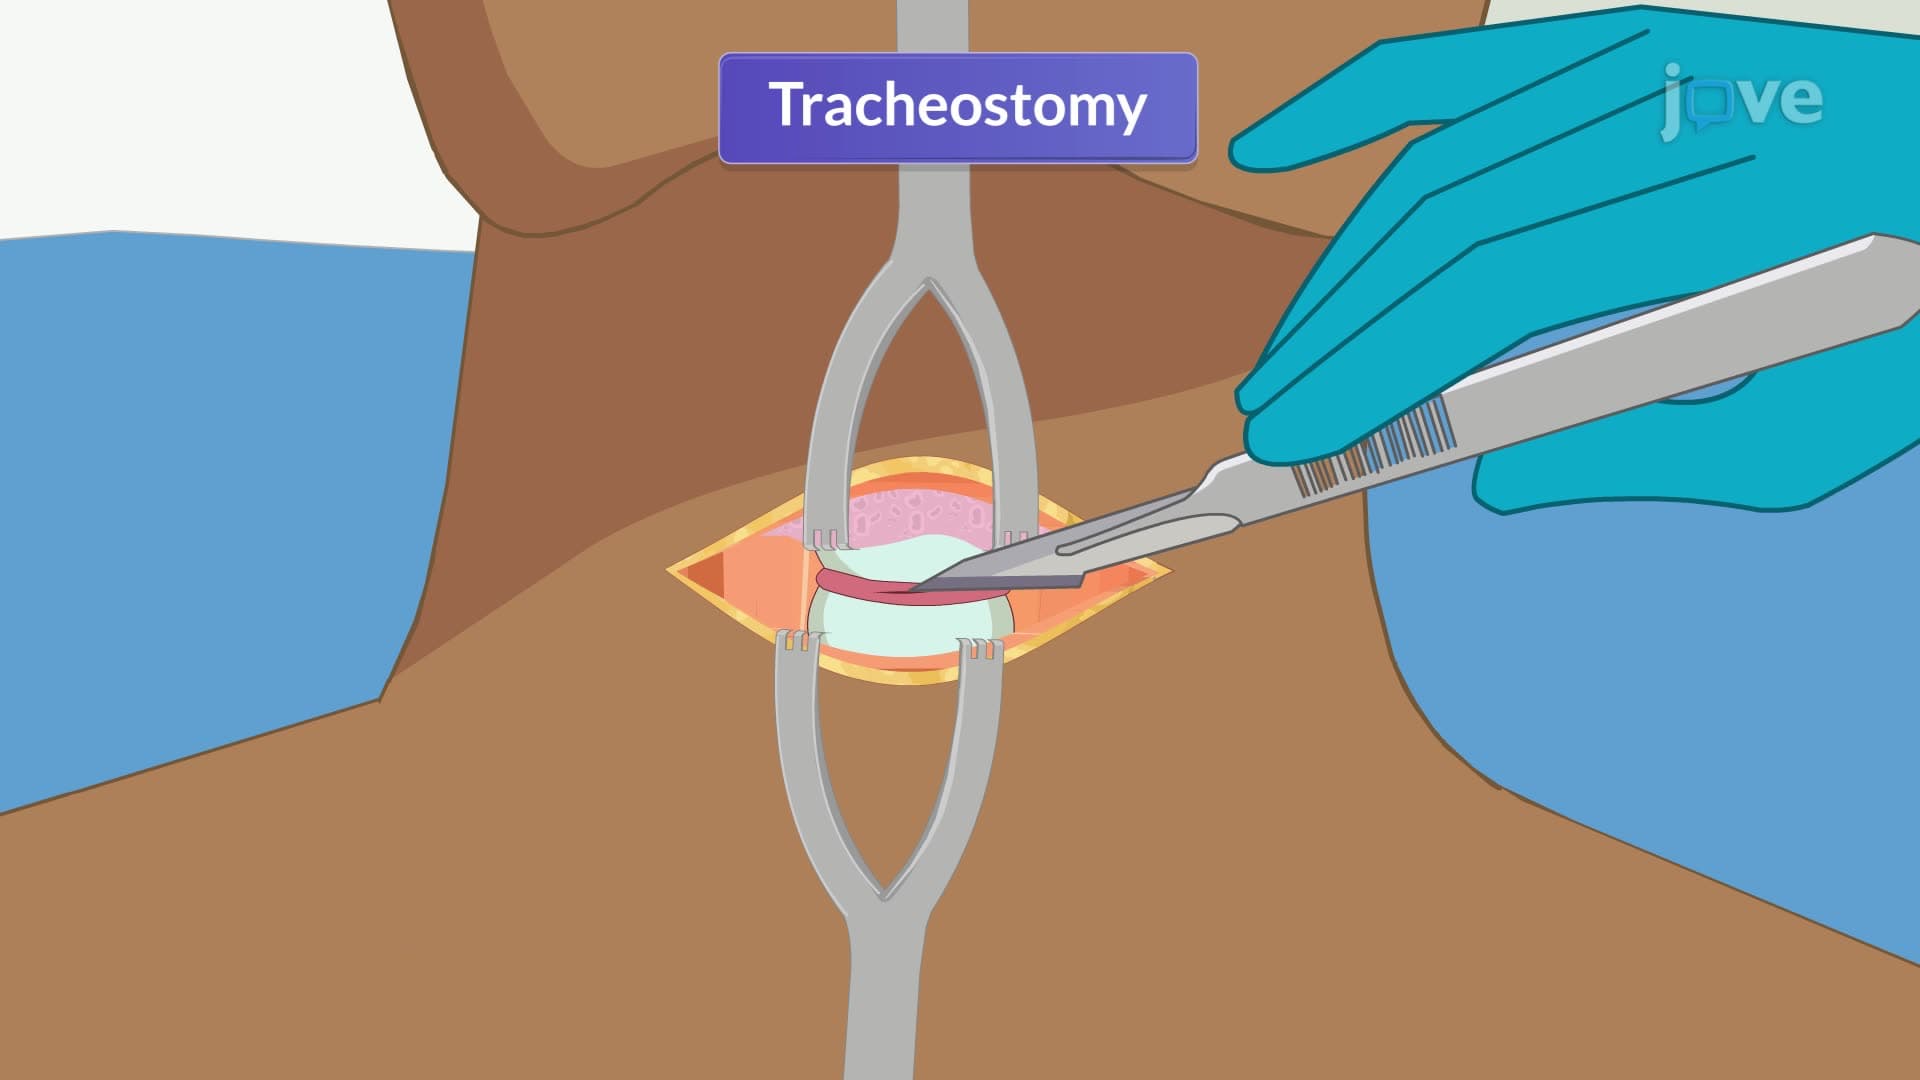 01:23
Oxygen Delivering System III: Tracheostomy and T-piece
Tracheostomy
A tracheostomy is a surgically created opening (stoma) in the anterior part of the trachea. It is used to establish a patient airway, bypass an upper airway obstruction, simplify the removal of secretions, permit long-term...
 01:16
Oxygen Delivering System II: Venturi Mask and Transtracheal Oxygen
Venturi Mask
The Venturi mask, named after the Venturi effect, is designed to deliver precise oxygen concentrations. It consists of a large tube with an oxygen inlet that narrows down, causing a pressure drop that pulls air in through adjustable side ports. The mask is a lightweight,...
 01:29
Drug Dosing: Infants and Children