Related Experiment Video
Updated: Jun 26, 2026

Cell-based Calcium Assay for Medium to High Throughput Screening of TRP Channel Functions using FlexStation 3
Published on: August 17, 2011
The impact of the assay for measuring albumin on corrected ('adjusted') calcium concentrations
Laura Labriola1, Pierre Wallemacq, Béatrice Gulbis
1Department of Nephrology, Cliniques Universitaires St-Luc, Université Catholique de Louvain, Belgium. laura.labrioloa@uclouvain.be

Background:
The K/DOQI guidelines recommend the use of albumin-corrected calcium (Ca), phosphate, parathyroid hormone (PTH) and calcium-phosphate product as therapeutic targets. The two most common assays for measuring albumin yield discordant results in uraemic patients, the Bromcresol purple (BCP) method providing lower albumin values than the Bromcresol green one (BCG). The aim of this study was to assess the impact of the assay on corrected Ca and, thus, on reaching recommended K/DOQI targets for corrected Ca and CaxP product.
Methods:
We measured plasma albumin (both by BCG and BCP), total Ca and phosphate in all our chronic hemodialysis (HD) patients. Total Ca was corrected ("adjusted") for albumin level by a formula proposed by the K/DOQI.
Results:
89 patients were included, aged 71.2 +/- 11.5 years, on chronic hemodialysis for 29 (1-362) months. Albumin level was 3.78 +/- 0.24 g/dL by BCG and 3.12 +/- 0.27 by BCP ( p < 0.0001). Based on BCG albumin levels there were 12 cases of "hypocalcaemia" (<8.6 mg/dL), 3 cases of "hypercalcaemia" (>10 mg/dL) and 74 cases with "normal" Ca. The corresponding albumin levels were 3.9 +/- 0.2; 3.1 +/- 0.6 and 3.8 +/- 0.2 g/dL, respectively. According to BCP albumin levels, only one patient was labelled as hypocalcaemia , 21 as hypercalcaemia et 67 as "normal" adjusted Ca (albumin 3.1; 3 +/- 0.3 and 3.2 +/- 0.3 g/dL, respectively). Depending on the use of BCG or BCP, a discrepancy was thus observed in 29 cases (32.6%): 18 cases were classified as hypercalcaemia when albumin was measured by BCP but were considered normal using BCG, whereas 11 cases classified as hypocalcaemia with BCG had normal adjusted Ca with BCP. Concerning CaxP product, 7 discrepancies were detected.
Discussion And Conclusion:
The choice of either BCG or BCP has a major impact on albumin-adjusted Ca and thus on reaching K/DOQI targets for Ca and CaxP product. Clinicians should take this fact into account for the interpretation of laboratory values and the prescription of drugs related to mineral metabolism and dialysate calcium concentration. The type of assay used for the measurement of albumin should also be recorded and its impact taken into account (or corrected) in multicentric studies and registries.
Related Concept Videos
 01:21
Skeleton and Calcium Homeostasis
 01:26
EDTA: Auxiliary Complexing Reagents
 01:29
Drug Distribution: Plasma Protein Binding
 01:20
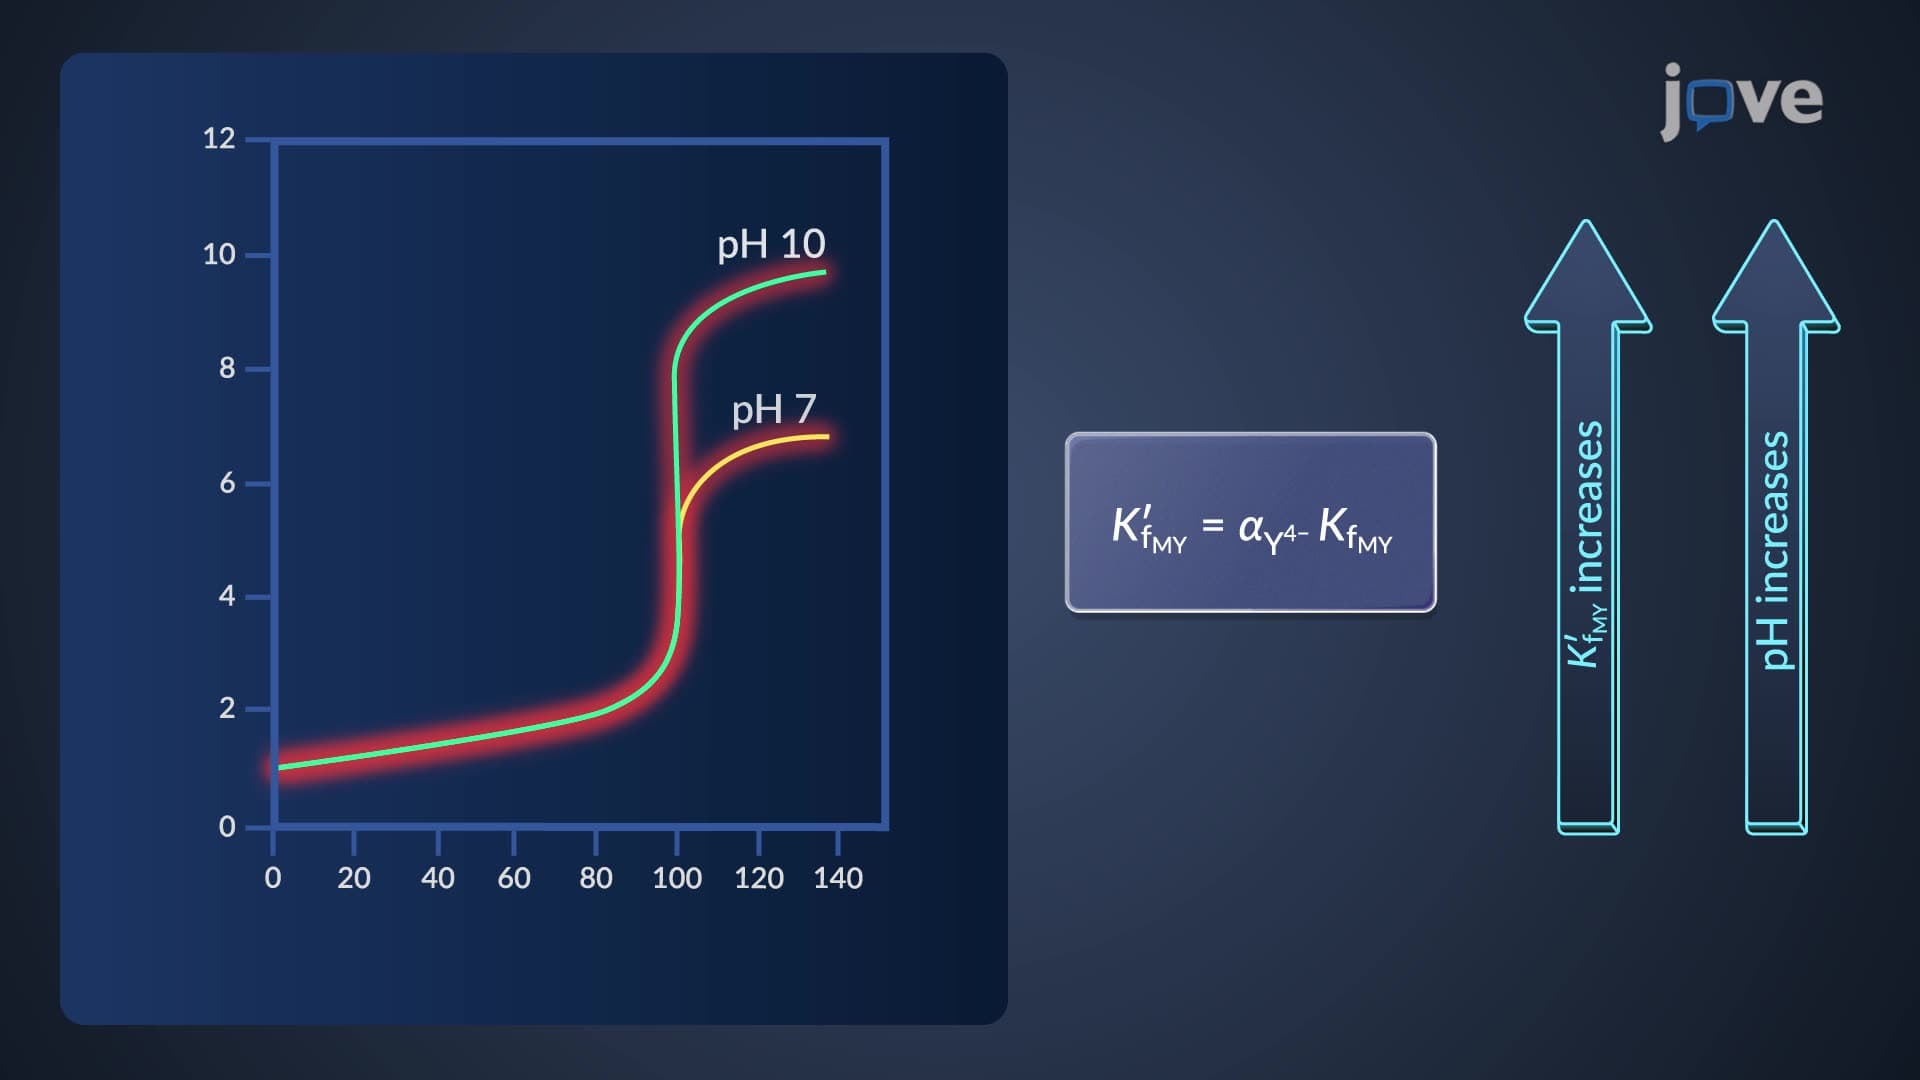
Complexometric EDTA Titration Curves
 01:29
Factors Affecting Protein-Drug Binding: Patient-Related Factors
Age stands as a key determinant in protein-drug binding. Neonates, characterized by low albumin content, experience heightened concentrations of unbound drugs such as phenytoin and...
 01:27
Feedback Regulation of Calcium Concentration
Various transmembrane receptors, such as G protein-coupled receptors (GPCRs), elicit a response to extracellular signals by increasing cytosolic calcium. Activated GPCRs...