Related Experiment Videos
Prevalence and risk factors associated with decreased bone mineral density in patients with haemophilia
G Gerstner1, M L Damiano, A Tom
1Arizona Hemophilia and Thrombosis Center, Arizona Cancer Center, Tucson, AZ 85724-5024, USA.

Osteoporosis in adult males is an under-recognized problem. Patients with haemophilia have several predisposing factors for developing decreased bone mineral density (BMD) including prolonged periods of immobility, reduced weight bearing and co-morbidities associated with bone loss. To establish prevalence and risk factors associated with decreased BMD in patients with haemophilia. Adults with moderate or severe haemophilia A or B underwent dual-energy X-ray absorptiometry (DXA). BMD was correlated to laboratory values, joint mobility measurements and physical activity questionnaires. Thirty patients completed evaluations. The median age was 41.5 years (range 18-61). Median lowest T-score by DXA was -1.7 (range: -5.8 to +0.6), with the femoral neck being the site of the lowest T-scores. Based on World Health Organization criteria, 70% of patients had decreased BMD. Twenty-seven per cent of the participants (n = 8) had osteoporosis and 43% (n = 13) had osteopenia. Variables associated with increased bone loss included lower serum 25-hydroxyvitamin D levels (P = 0.03), lower body mass index (P = 0.047), lower activity scores (P = 0.02), decreased joint range of motion (P = 0.046), HIV (P = 0.03), HCV (P = 0.02), history of inhibitor (P = 0.01) and age (P = 0.03). Adults with haemophilia are at increased risk for developing osteoporosis. A history of HCV and HIV infections, decreased joint range-of-motion, decreased activity levels, history of an inhibitor and low body weight predict bone loss and suggest a population to target for screening. A high prevalence of vitamin D insufficiency was observed. Future studies should investigate interventions, including vitamin D supplementation, to prevent bone loss and fractures for this at-risk population.
Osteoporosis in adult males is an under-recognized problem. Patients with haemophilia have several predisposing factors for developing decreased bone mineral density (BMD) including prolonged periods of immobility, reduced weight bearing and co-morbidities associated with bone loss. To establish prevalence and risk factors associated with decreased BMD in patients with haemophilia. Adults with moderate or severe haemophilia A or B underwent dual-energy X-ray absorptiometry (DXA). BMD was correlated to laboratory values, joint mobility measurements and physical activity questionnaires. Thirty patients completed evaluations. The median age was 41.5 years (range 18-61). Median lowest T-score by DXA was -1.7 (range: -5.8 to +0.6), with the femoral neck being the site of the lowest T-scores. Based on World Health Organization criteria, 70% of patients had decreased BMD. Twenty-seven per cent of the participants (n = 8) had osteoporosis and 43% (n = 13) had osteopenia. Variables associated with increased bone loss included lower serum 25-hydroxyvitamin D levels (P = 0.03), lower body mass index (P = 0.047), lower activity scores (P = 0.02), decreased joint range of motion (P = 0.046), HIV (P = 0.03), HCV (P = 0.02), history of inhibitor (P = 0.01) and age (P = 0.03). Adults with haemophilia are at increased risk for developing osteoporosis. A history of HCV and HIV infections, decreased joint range-of-motion, decreased activity levels, history of an inhibitor and low body weight predict bone loss and suggest a population to target for screening. A high prevalence of vitamin D insufficiency was observed. Future studies should investigate interventions, including vitamin D supplementation, to prevent bone loss and fractures for this at-risk population.
Related Concept Videos
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:24
Disorders of Hemostasis
Thromboembolic Disorders
Two factors primarily cause thromboembolic conditions.
 01:25
Role of Vitamins in Maintaining Bone Health
Vitamin A
Vitamin A is involved in the process of bone remodeling. Retinoic acid, the active metabolite of Vitamin A, has nuclear receptors in osteoblasts and osteoclasts, which are involved in bone remodeling.
Vitamin B12
Vitamin B12 acts as a cofactor during the formation of osteoblast-related proteins, such as osteocalcin. Vitamin B12 plays a role...
 01:29
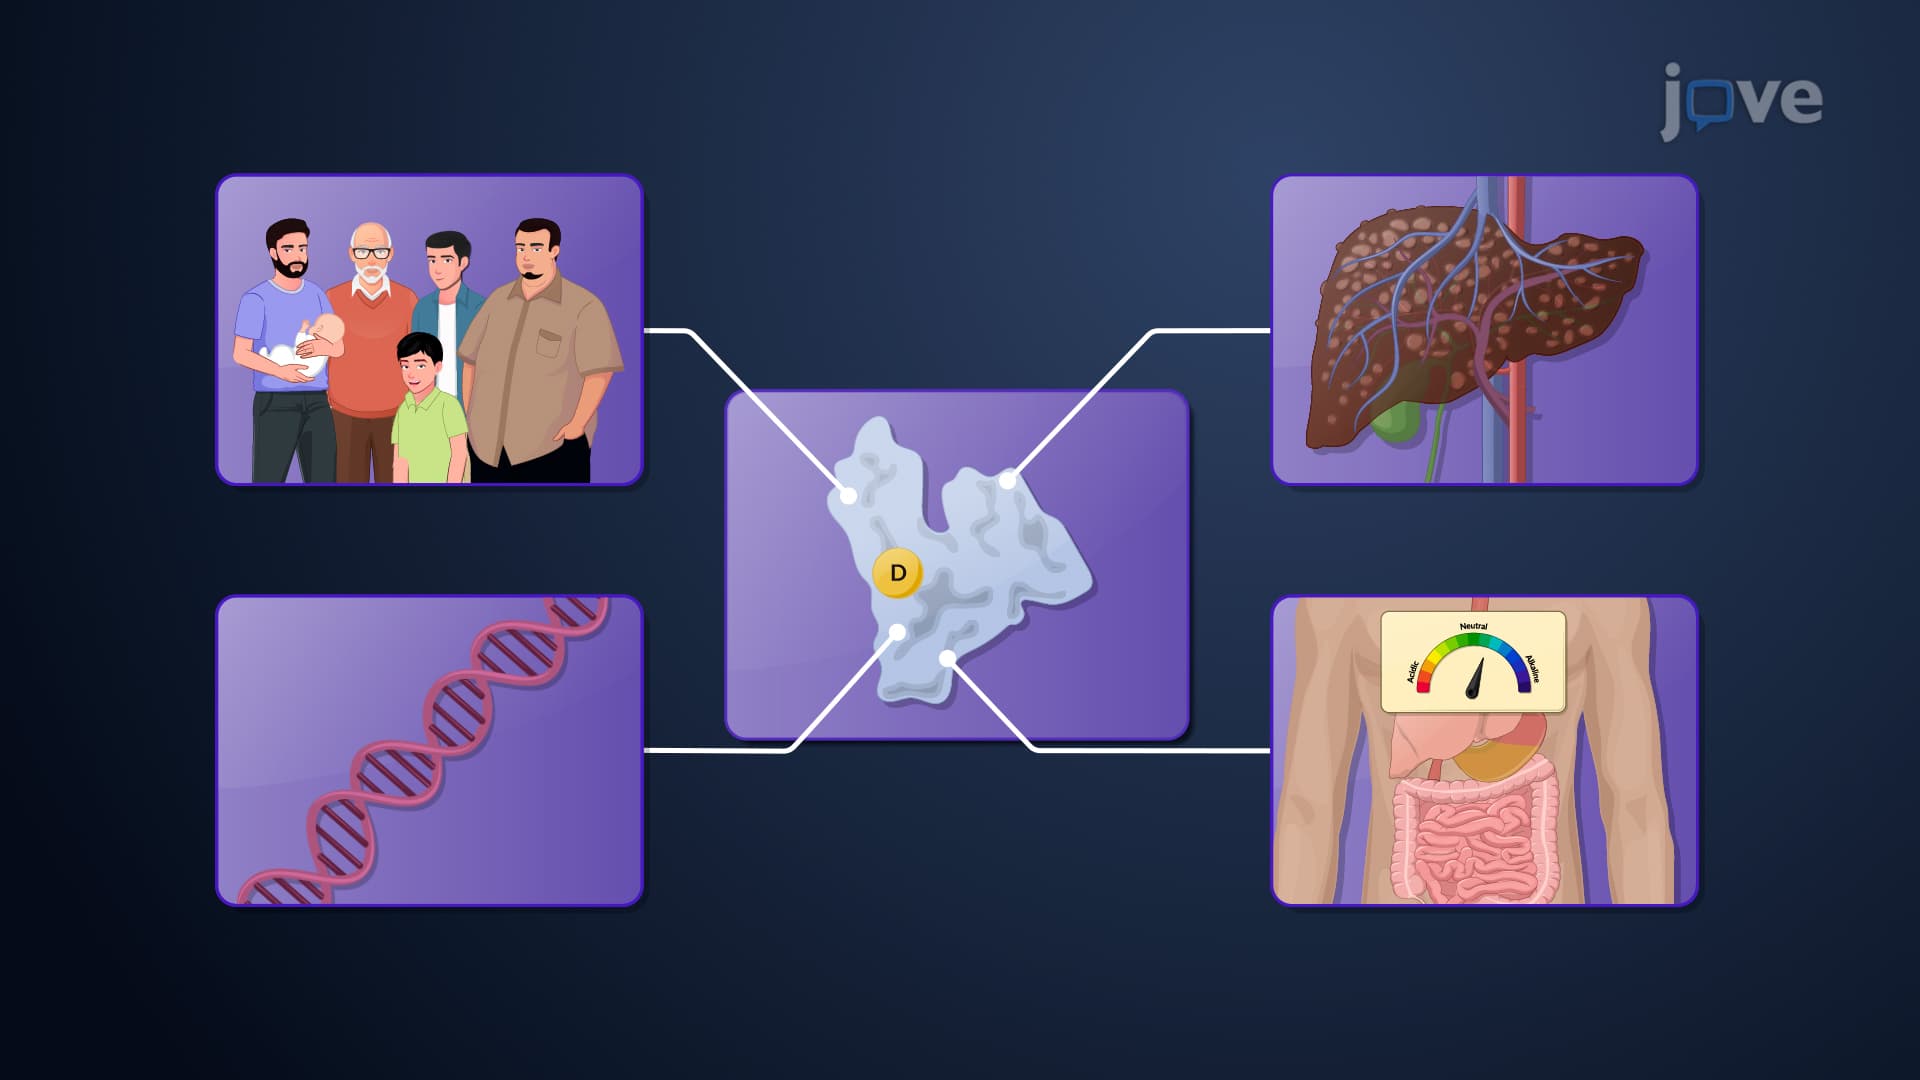
Factors Affecting Protein-Drug Binding: Patient-Related Factors
Age stands as a key determinant in protein-drug binding. Neonates, characterized by low albumin content, experience heightened concentrations of unbound drugs such as phenytoin and...
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:31
Essential Minerals for Bone Health
Calcium and Phosphorus
Calcium is a critical component of bones, especially in the form of calcium phosphate and calcium carbonate. Since the body cannot make calcium, it must be obtained from the diet. However, calcium cannot be absorbed from the small intestine without...