Related Experiment Video
Updated: Jun 25, 2026


Generation of Hypoparathyroid Rats via Carbon-Nanoparticle-Assisted Parathyroidectomy
Published on: July 14, 2023
Cinacalcet reduces vascular and soft tissue calcification in secondary hyperparathyroidism (SHPT) in hemodialysis
1Hospital Ernest Lluch, Calatayud, Spain. maladren@senefro.org

Insights
Cinacalcet effectively managed secondary hyperparathyroidism (SHPT) in a hemodialysis patient, reducing vascular calcification and improving quality of life. This calcimimetic offers a promising treatment for SHPT complications.
Area of Science:
- Nephrology
- Endocrinology
- Cardiovascular Medicine
Background:
- Secondary hyperparathyroidism (SHPT) in chronic kidney disease (CKD) patients on hemodialysis (HD) presents management challenges.
- Conventional treatments for SHPT can exacerbate hypercalcemia and hyperphosphatemia, increasing cardiovascular disease risk due to vascular calcification.
Observation:
- A 40-year-old male on HD with severe SHPT (iPTH > 2,500 pg/ml) exhibited widespread calcium deposits and difficult-to-control metabolic abnormalities.
- The patient had multiglandular parathyroid disease and an ectopic gland, unresponsive to conventional therapies including sevelamer and dietary modifications.
Findings:
- Treatment with cinacalcet, a Type II calcimimetic, led to a significant reduction in vascular and soft tissue calcification over two years.
- Radiological assessments showed decreased calcium deposits in the chest and hands, improved bone morphology, and reduced left ventricular hypertrophy.
- Cinacalcet helped normalize intact parathyroid hormone (iPTH), phosphorus (P), and calcium (Ca) levels, maintaining them within Kidney Disease Outcomes Quality Initiative targets.
Implications:
- Cinacalcet demonstrates efficacy in reducing calcification and improving cardiovascular parameters in SHPT patients on HD.
- The observed improvements in bone morphology and quality of life suggest a comprehensive benefit beyond metabolic control.
- This case highlights cinacalcet as a valuable therapeutic option for managing complex SHPT cases refractory to standard treatments.
Abstract:
Management of secondary hyperparathyroidism (SHPT) in chronic kidney disease patients on hemodialysis (HD) can be challenging. Conventional treatments can lead to hypercalcemia and hyperphosphatemia, both of which are associated with vascular and soft tissue calcification and increased risk of cardiovascular disease. We report the effect of treatment with the Type II calcimimetic cinacalcet on vascular calcification in a HD patient with SHPT. A 40-year-old male with a 24-year history of kidney failure secondary to mesangial proliferative glomerulonephritis, commenced HD in October 2004 following chronic graft dysfunction. The patient was admitted to hospital with renal insufficiency and metabolic abnormalities. An anatomopathological study showed calcium (Ca) deposits in the alveolar septa, bronchial wall and pulmonary arterioles. Parathyroid methoxy isobutyl isonitrile (MIBI) scintigraphy revealed multiglandular parathyroid disease and an ectopic gland behind the sternal notch. Serum intact parathyroid hormone (iPTH) was repeatedly found to be > or = 2,500 pg/ml, and was accompanied by significant abnormalities in phosphorus (P) and Ca metabolism which were difficult to control. The patient was initially treated with sevelamer, low dose calcium carbonate, a low P and reduced protein diet and high doses of intravenous erythropoietin. In addition, he received HD with a high efficiency membrane for 4.5 hours, 4-times weekly. Treatment with cinacalcet was initiated at 30 mg/day and adjusted to achieve National Kidney Foundation Kidney Disease Outcomes Quality Initiative targets for iPTH, P, Ca and Ca-P product. One year following cinacalcet treatment, a chest x-ray showed a moderate reduction in Ca deposits, a bone X-ray showed a significant reduction in vascular calcifications, and parathyroid MIBI scintigraphy showed a disappearance of ectopic focus and minimal remains of glands. Significant reductions in calcemia were controlled by concomitant modifications to oral Ca supplementation, Ca concentration in the dialysis liquid, and administration of paricalcitriol. In the second year of treatment, iPTH was maintained within the target range, with moderate rises in P and stabilization of serum Ca. An echocardiogram showed an improvement in left ventricular hypertrophy. Chest and hand X-rays showed a progressive reduction in calcifications. Radiology showed an improvement in bone morphology, with reduced trabeculation and better cortical definition in the phalanx bones. In conclusion, the changes in iPTH, P and Ca associated with cinacalcet treatment were accompanied by reduced vascular and soft tissue calcification in this patient. There were no cardiovascular events and the patient experienced a marked improvement in quality of life.

Related Concept Videos
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 00:51
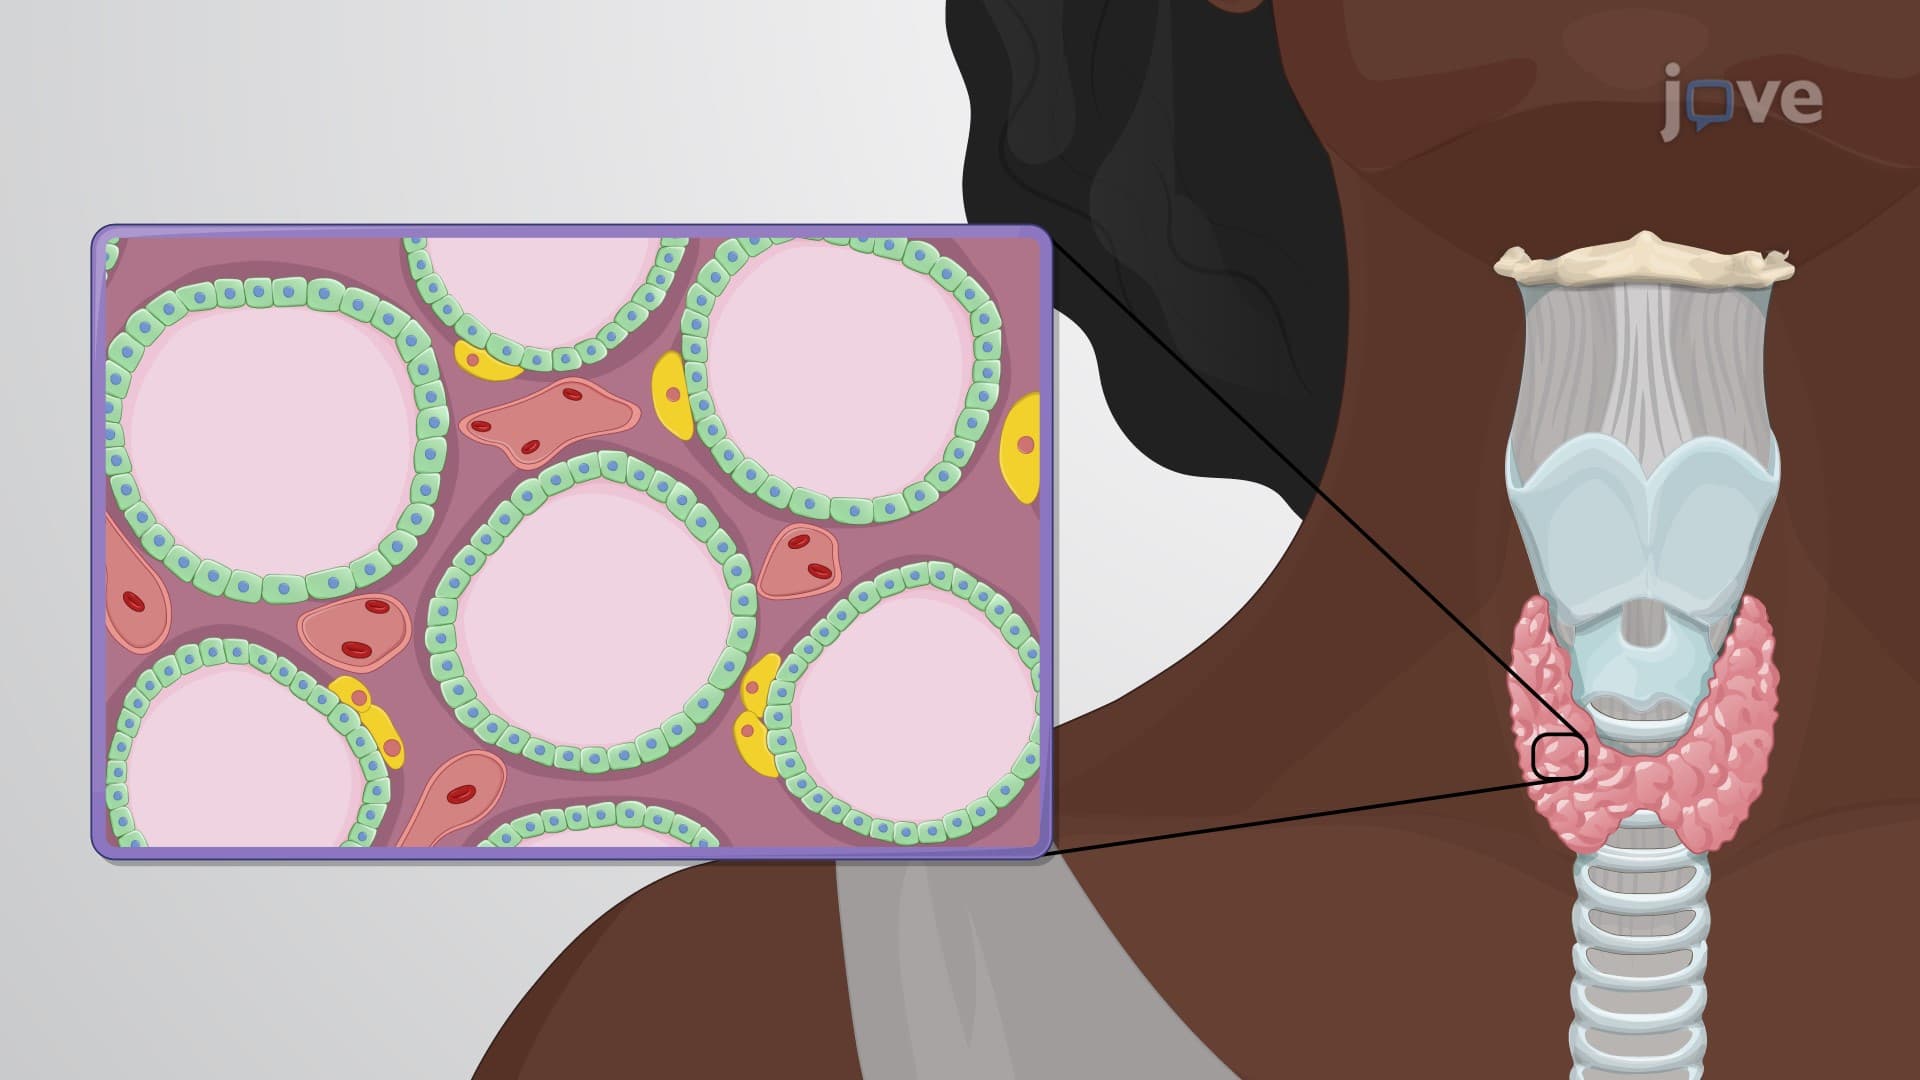
Synthesis and Functions of Calcitonin
The exact mechanisms by which calcitonin operates in calcium homeostasis remain elusive, but its significance is evident in several vital...
 01:21
Skeleton and Calcium Homeostasis
 01:27
Urinary Tract Calculi IV: Nutrition Therapy and Prevention
 01:26
Urinary Tract Calculi II: Pathophysiology and Clinical Manifestations
 01:30
Urinary Tract Calculi III: Medical Management