Feasibility of simultaneous pre- and postfilter transcranial Doppler monitoring during carotid artery stenting
Related Experiment Video
Updated: Jun 25, 2026
Optimized System for Cerebral Perfusion Monitoring in the Rat Stroke Model of Intraluminal Middle Cerebral Artery Occlusion
Published on: February 17, 2013
Zsolt F Garami1, Jean Bismuth, Kristofer M Charlton-Ouw
1Department of Cardiovascular Surgery, Methodist DeBakey Heart and Vascular Center, The Methodist Hospital, Houston, Texas 77030, USA. zgarami@tmhs.org

Insights
Embolic protection devices (EPDs) reduce but do not eliminate brain emboli during carotid artery stenting (CAS). Dual-probe transcranial Doppler (TCD) monitoring can assess EPD efficacy in preventing distal embolization during CAS procedures.
Area of Science:
- Interventional Cardiology
- Neurology
- Biomedical Engineering
Background:
- Carotid artery stenting (CAS) is an alternative to surgery for carotid artery stenosis.
- Cerebral embolization is a major risk of CAS, potentially causing stroke.
- Embolic protection devices (EPDs) are used to prevent emboli, but their efficacy in preventing smaller emboli is unclear.
Purpose of the Study:
- To quantify microemboli reaching the brain during CAS with EPDs in place.
- To evaluate the in vivo efficacy of EPDs in preventing distal embolization.
- To describe a novel application of dual-probe transcranial Doppler (TCD) for monitoring emboli.
Main Methods:
- Six patients undergoing CAS were monitored using simultaneous dual-probe TCD.
- TCD probes were placed proximal and distal to the EPD to quantify microemboli.
- Two EPDs were evaluated: FilterWire EZ System (FW) and GORE Neuro Protection System (NPS).
Main Results:
- Both FW and NPS EPDs significantly reduced microemboli compared to baseline.
- Microemboli were detected both before and after the EPD, indicating incomplete protection.
- NPS showed a trend towards fewer microemboli during stent placement compared to FW.
Conclusions:
- EPDs reduce, but do not eliminate, microemboli during CAS.
- Dual-probe TCD monitoring is a valuable tool for assessing EPD efficacy and technique.
- Further research with larger sample sizes is needed to compare EPDs.
Objective:
Carotid artery stenting (CAS) is emerging as an acceptable treatment alternative to surgery for patients with carotid artery stenosis. The major risk of CAS is cerebral embolization of plaque and thrombus causing stroke or asymptomatic brain infarction. Use of embolic protection devices (EPD) to trap emboli before they reach the brain is now standard practice in CAS. The pore size of the currently available filters is >100 microns and emboli smaller than the EPD pores can still reach the brain. While the use of EPD is widespread, little evidence exists of their in vivo efficacy in preventing distal embolization. Our aim was to quantify the number of emboli reaching the brain with the device in place. Therefore, the expected value of this report is in its description of a novel application of transcranial Doppler (TCD). Due to the limited number of cases, it is not intended to support the use of one EPD over another.
Methods:
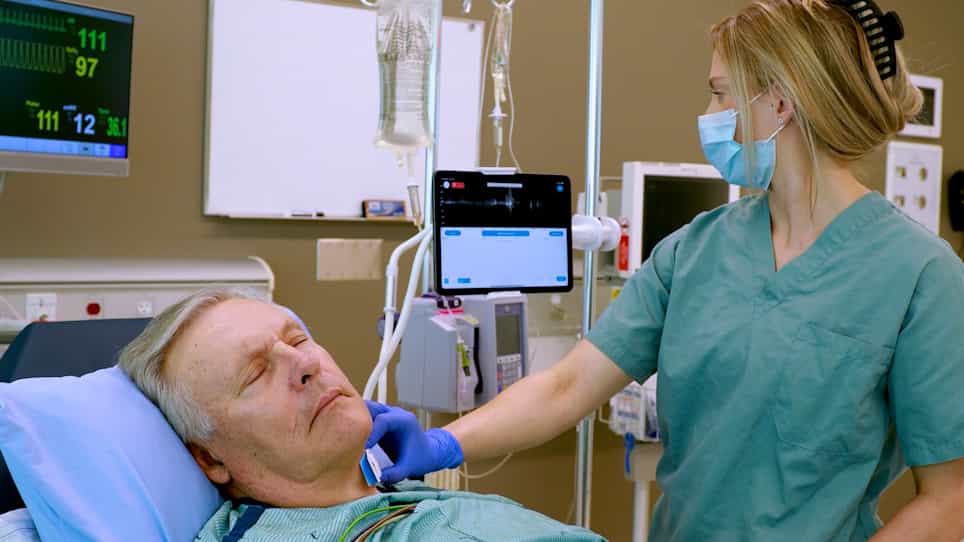
Six patients were monitored with ipsilateral simultaneous dual probe TCD during CAS. Two types of cerebral protection systems were evaluated: FilterWire EZ System (FW; Boston Scientific, Santa Clara, Calif) and GORE Neuro Protection System (NPS; W.L. Gore and Associates, Flagstaff, Ariz). By placing TCD probes both proximal and distal to the filterwire EPD, we quantified the microembolic signals before the EPD as well as those, which reached the intracranial circulation after the EPD. One probe was placed submandibularly to monitor the ICA (SICA), while another was placed transtemporally to monitor the middle and anterior cerebral artery (MCA + ACA). We compare the number of extracranial emboli prior to the EPD with the number of intracranial emboli after the EPD.
Results:
Dual probe monitoring was successful during the five stages of the CAS: lesion crossing (LC), predilatation (PreD), stent placement (SP), postdilatation (PostD), and filter/device removal (FR/DR). Using FW during LC by probe 1 (SICA)/probe 2 (MCA + ACA): (18 [range, 15-22]/15 [range, 11-20]), PreD (111 [range, 101-121]/101 [range, 90-111]), SP (68 [range, 60-76]/42 [range, 30-53]), PostD (27 [range, 25-30]/24 [range, 22-27]), FR (0.3 [range, 0-1]/0.7 [range, 0-1]) average number of microembolic signals were detected. Using NPS during LC (1.7 [range, 0-3]/1 [range, 0-2]), PreD (0/1.7 [range, 0-4]), SP (0/0), PostD (0/0), DR (18 [range, 0-18]/6.7 [range, 1-13]) average number of microembolic signals were detected.
Conclusion:
EPD significantly reduces but does not eliminate the number of microemboli reaching the brain during carotid artery angioplasty and stenting. We propose monitoring of CAS with submandibular and transtemporal TCD probes to further evaluate the practice of distal embolization protection. Although our study is not powered to make any recommendations about EPDs, we believe that sequential dual probe TCD monitoring is a worthy tool with the potential to give vital information to assess the various devices and the techniques of utilization.