Related Experiment Video
Updated: Jun 25, 2026

An Affordable HIV-1 Drug Resistance Monitoring Method for Resource Limited Settings
Published on: March 30, 2014
Cost-effectiveness analysis of lopinavir/ritonavir and atazanavir+ritonavir regimens in the CASTLE study
Kit N Simpson1, Rukmini Rajagopalan, Birgitta Dietz
1Medical University of South Carolina, 151 B Rutledge Avenue, Room 409, Charleston, South Carolina 29425, USA. simpsonk@musc.edu

Introduction:
The purpose of the study was to conduct a cost-effectiveness analysis and budget impact analysis comparing lopinavir with ritonavir (LPV/r) and atazanavir plus ritonavir (ATV+RTV) for antiretroviral-naïve patients with a baseline CD4+ T-cell distribution and total cholesterol (TC) profile as reported in the CASTLE study.
Methods:
This decision analysis study used a previously published Markov model of HIV disease, incorporating coronary heart disease (CHD) events to compare the short- and long-term budget impacts and CHD consequences expected for the two regimens.
Results:
Patients were assumed to have a baseline CHD risk of 4.6% (based on demographic data) and it was also assumed that 50% of the population in the CASTLE study were smokers. The CHD risk differences (based on percent of patients with TC >240 mg/dL) in favor of ATV+RTV resulted in an average improvement in life expectancy of 0.031 quality-adjusted life years (QALYs) (11 days), and an incremental cost-effectiveness ratio of $1,409,734/QALY. Use of the LPV/r regimen saved $24,518 and $36,651 at 5 and 10 years, respectively, with lifetime cost savings estimated at $38,490. A sensitivity analysis using a cohort of all smokers on antihypertensive medication estimated an average improvement in life expectancy of 31 quality-adjusted days in favor of ATV+RTV, and a cost-effectiveness ratio of $520,861/QALY: a ratio that is still above the acceptable limit within the US.
Conclusion:
The use of an LPV/r-based regimen in antiretroviral-naïve patients with a baseline CHD risk similar to patients in the CASTLE study appears to be a more cost-effective use of resources compared with an ATV+RTV-based regimen. The very small added CHD risk predicted by LPV/r treatment is more than offset by the substantial short- and long-term cost savings expected with the use of LPV/r in antiretroviral-naïve individuals with average to moderately elevated CHD risk.

Related Concept Videos
 01:23
Types of Biopharmaceutical Studies: Controlled and Non-Controlled Approaches
Non-controlled studies, commonly employed for initial exploration, lack a control group, rendering them susceptible to biases and external influences. In contrast, controlled...
 01:15
Impact of Pharmacokinetic–Pharmacodynamic Models: Regulatory Decisions
 01:10
Retrovirus Life Cycles
 01:08
Renal Drug Clearance: Comparison Between Renal Excretion Methods
Renal clearance is often associated with the renal glomerular filtration rate (GFR), which represents the rate at which plasma is filtered through the glomeruli in the kidney. When drug reabsorption is minimal and there is no active secretion, renal clearance is closely related to the...
 01:22
Antiviral Nucleoside Inhibitors
 01:27
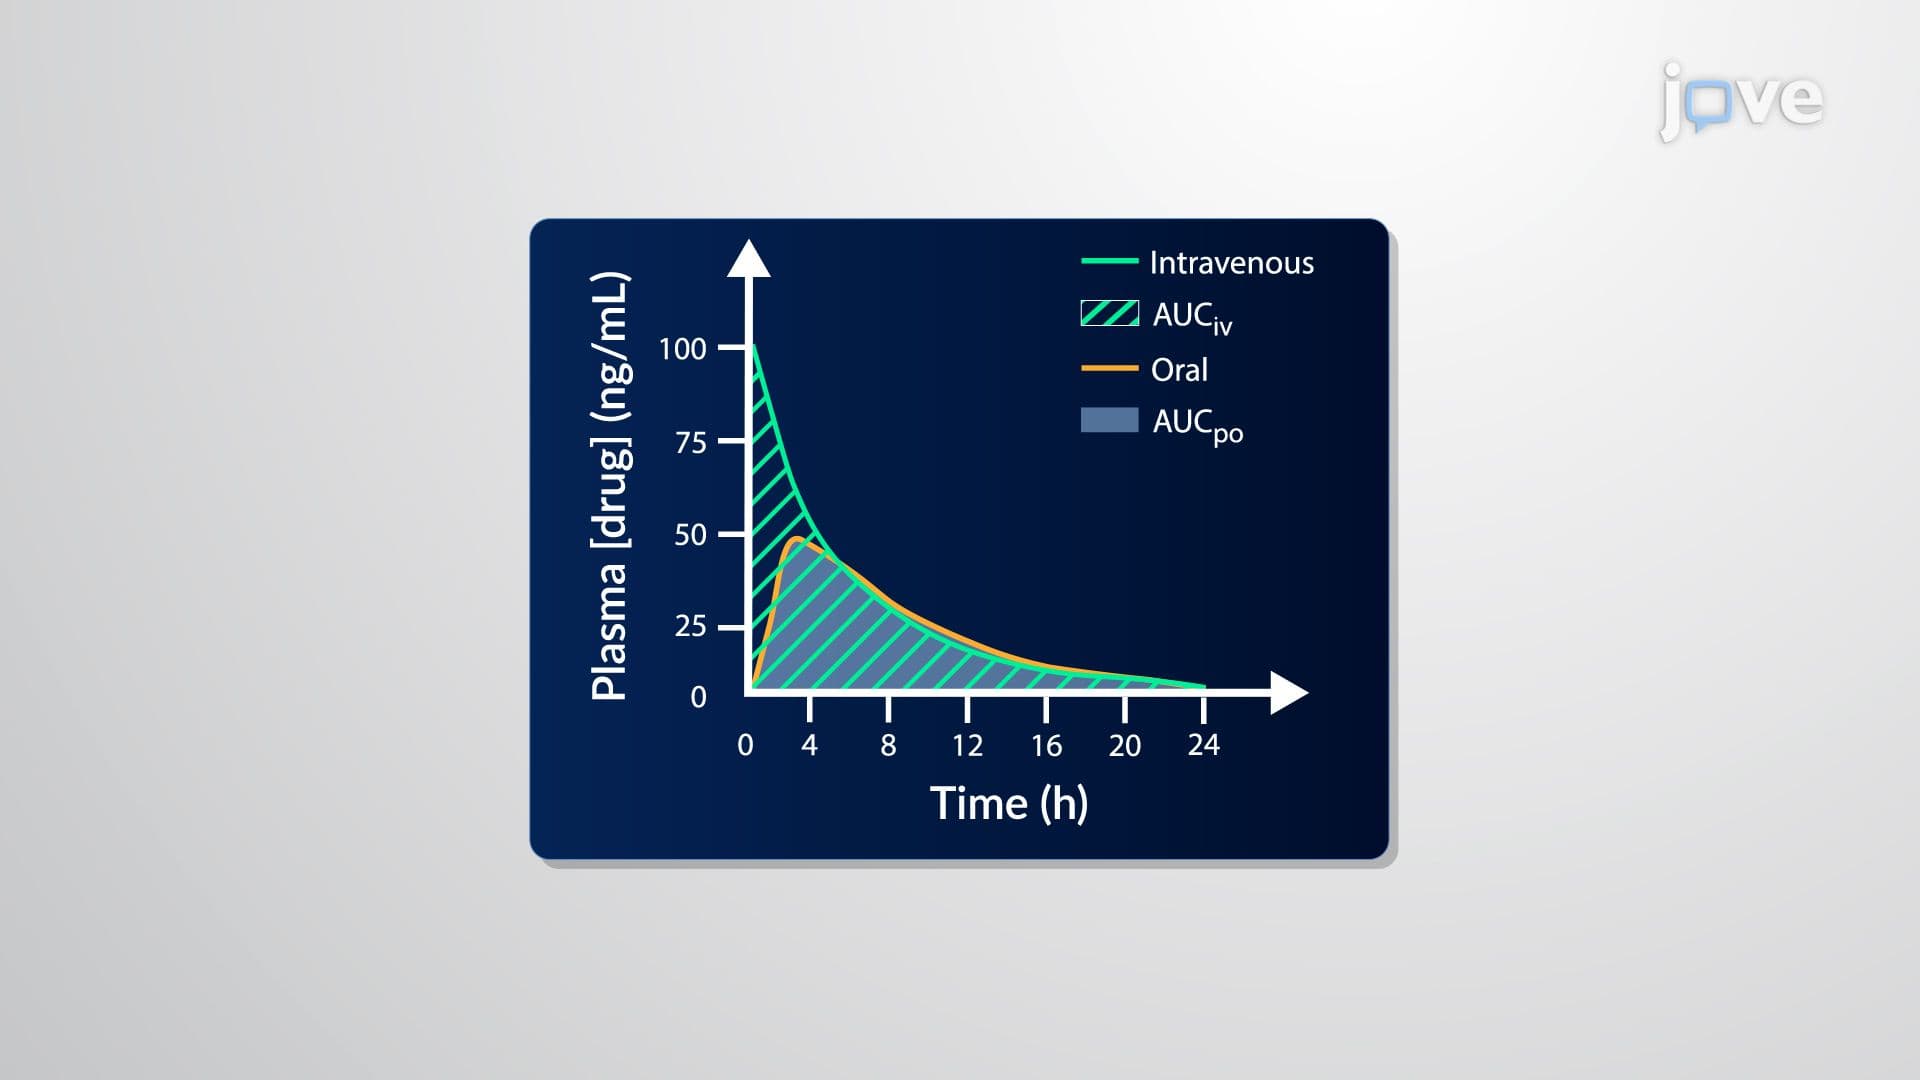
Bioavailability Study Design: Absolute Versus Relative Bioavailability