Related Experiment Video
Updated: Jun 25, 2026
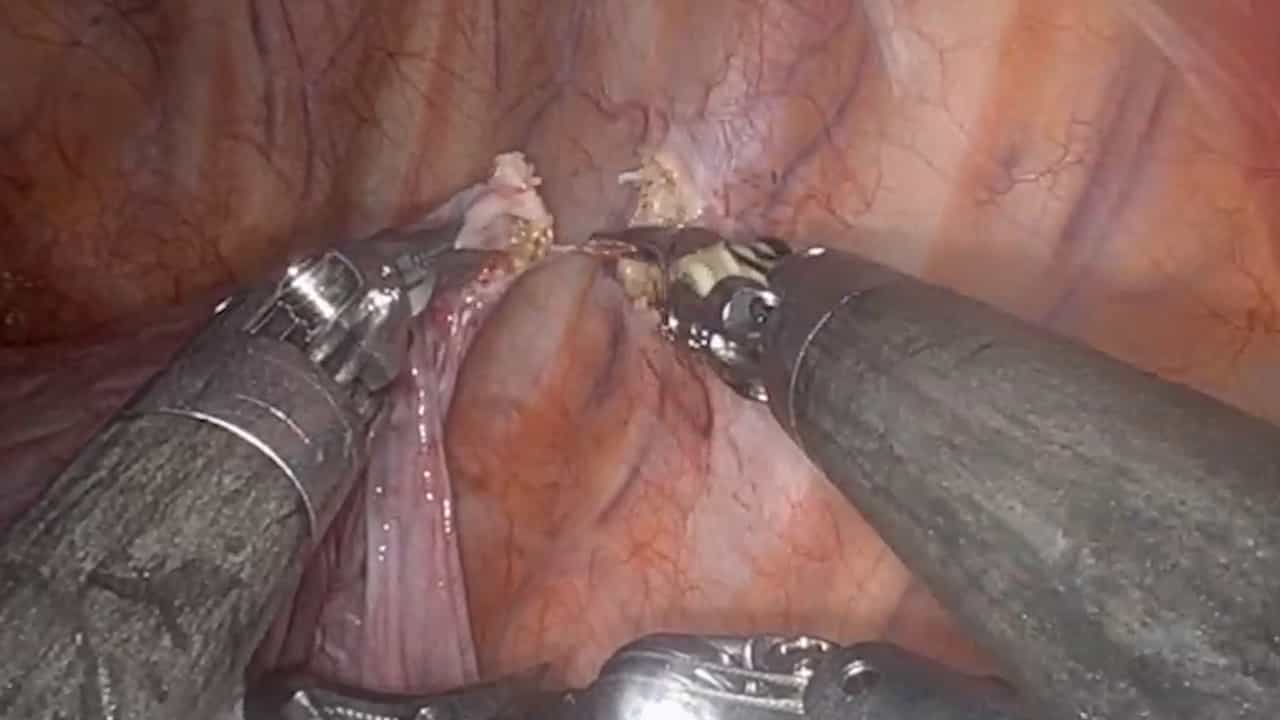

Robotic-assisted Left Pneumonectomy For Vanishing Lung Syndrome
Published on: January 23, 2026
[A case of unanticipated postoperative respiratory distress from cancerous pleural effusion]
Kishiko Nakai1, Tetsuya Kushikata, Ryuji Tose
1Department of Anesthesiology, Hirosaki University Graduate School of Medicine, Hirosaki 036-8563.

A 63-year-old woman with a 2-month history of abdominal distension received diagnostic laparotomy under general anesthesia. The chest X-ray one week preoperatively demonstrated slight left pleural effusion, but she did not show any dyspnea on preanesthetic interview. General anesthesia was induced with propofol, ketamine and fentanyl. Sp(O2) decreased after suction of ascites, but it improved with PEEP Spontaneous respiration developped after the operation, but tidal volume was not enough and respiratory pattern was irregular. Train of four was 100%, and bronchofiberscopy had no suspicions findings. The chest X-ray and TEE revealed extended left hemilateral pleural effusion. Seven hundred seventy ml of hemorrhagic pleural fluid was suctioned. Respiratory pattern improved and the endotracheal tube was removed smoothly. We consider that we diagnosed her state only from her subjective symptoms without considering objective symptoms. Besides we had to explain a possibility of a unanticipated serious respiratory distress. In such a case, more accurate and objective diagnostic procedures are required.
A 63-year-old woman with a 2-month history of abdominal distension received diagnostic laparotomy under general anesthesia. The chest X-ray one week preoperatively demonstrated slight left pleural effusion, but she did not show any dyspnea on preanesthetic interview. General anesthesia was induced with propofol, ketamine and fentanyl. Sp(O2) decreased after suction of ascites, but it improved with PEEP Spontaneous respiration developped after the operation, but tidal volume was not enough and respiratory pattern was irregular. Train of four was 100%, and bronchofiberscopy had no suspicions findings. The chest X-ray and TEE revealed extended left hemilateral pleural effusion. Seven hundred seventy ml of hemorrhagic pleural fluid was suctioned. Respiratory pattern improved and the endotracheal tube was removed smoothly. We consider that we diagnosed her state only from her subjective symptoms without considering objective symptoms. Besides we had to explain a possibility of a unanticipated serious respiratory distress. In such a case, more accurate and objective diagnostic procedures are required.
Related Concept Videos
 01:28
Pleural Effusion II: Symptoms and Management
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:08
Pneumothorax II: Pathophysiology
 01:25
Pleural Effusion I: Introduction
There are two main types of pleural effusion: transudative and exudative. They are differentiated using Light's criteria,...
 01:30
Acute Respiratory Failure-III
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...