Related Experiment Video
Updated: Jun 25, 2026
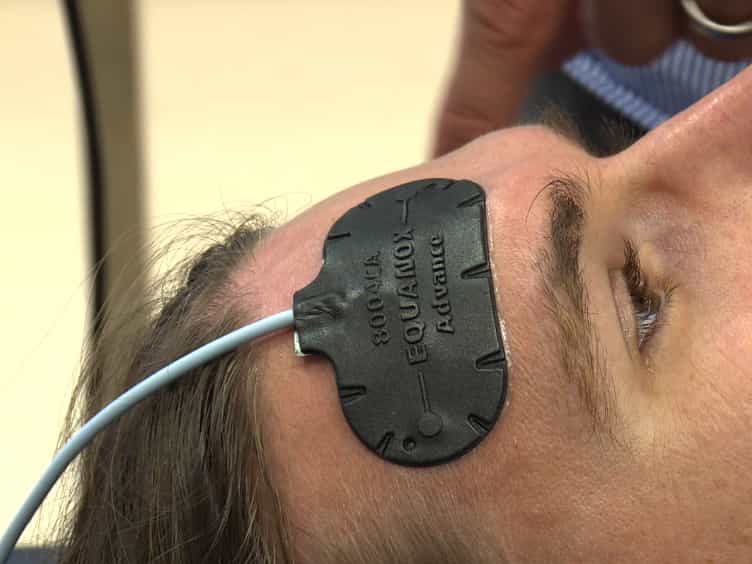

A Model to Simulate Clinically Relevant Hypoxia in Humans
Published on: December 22, 2016
The new AASM criteria for scoring hypopneas: impact on the apnea hypopnea index
Warren R Ruehland1, Peter D Rochford, Fergal J O'Donoghue
1Institute for Breathing and Sleep, Austin Health, Heidelberg, Victoria, Australia. Warren.Ruehland@austin.org.au

Study Objectives:
To compare apnea-hypopnea indices (AHIs) derived using 3 standard hypopnea definitions published by the American Academy of Sleep Medicine (AASM); and to examine the impact of hypopnea definition differences on the measured prevalence of obstructive sleep apnea (OSA).
Design:
Retrospective review of previously scored in-laboratory polysomnography (PSG).
Setting:
Two tertiary-hospital clinical sleep laboratories.
Patients Or Participants:
328 consecutive patients investigated for OSA during a 3-month period.
Interventions:
N/A.
Measurements And Results:
AHIs were originally calculated using previous AASM hypopnea scoring criteria (AHI(Chicago)), requiring either >50% airflow reduction or a lesser airflow reduction with associated >3% oxygen desaturation or arousal. AHIs using the "recommended" (AHI(Rec)) and the "alternative" (AHI(Alt)) hypopnea definitions of the AASM Manual for Scoring of Sleep and Associated Events were then derived in separate passes of the previously scored data. In this process, hypopneas that did not satisfy the stricter hypopnea definition criteria were removed. For AHI(Rec), hypopneas were required to have > or =30% airflow reduction and > or =4% desaturation; and for AHI(Alt), hypopneas were required to have > or =50% airflow reduction and > or =3% desaturation or arousal. The median AHI(Rec) was approximately 30% of the median AHI(Chicago), whereas the median AHI(Alt), was approximately 60% of the AHI(Chicago), with large, AHI-dependent, patient-specific differences observed. Equivalent cut-points for AHI(Rec) and AHI(Alt), compared to AHI(Chicago) cut-points of 5, 15, and 30/h were established with receiver operator curves (ROC). These cut-points were also approximately 30% of AHI(Chicago) using AHI(Rec) and 60% of AHI(Chicago) using AHI(Alt). Failure to adjust cut-points for the new criteria would result in approximately 40% of patients previously classifled as positive for OSA using AHI(Chicago) being negative using AHI(Rec) and 25% being negative using AHI(Alt).
Conclusions:
This study demonstrates that using different published standard hypopnea definitions leads to marked differences in AHI. These results provide insight to clinicians and researchers in interpreting results obtained using different published standard hypopnea definitions, and they suggest that consideration should be given to revising the current scoring recommendations to include a single standardized hypopnea definition.
Related Concept Videos
 01:19
Respiratory Assessment: Purpose and Indications
Objectives and Importance:
The primary goal of respiratory assessment is to evaluate patients at early risk of clinical deterioration. Since respiratory distress often precedes other signs of declining health, breathing patterns and sounds become a...
 01:26
Respiratory Volumes and Capacities I
 01:10
Atelectasis II: Pathophysiology
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:25
Hyperpnea and Hyperventilation
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement: