Related Experiment Video
Updated: Jun 25, 2026


A Modified Trier Social Stress Test for Vulnerable Mexican American Adolescents
Published on: July 10, 2017
A subnormal peak cortisol response to stimulation testing does not predict a subnormal cortisol production rate
A N Paisley1, S V Rowles, D Brandon
1Department of Endocrinology, Christie Hospital, Manchester M20 4BX, United Kingdom.

Introduction:
The decision to commence lifelong glucocorticoid replacement therapy is often based on a cortisol stimulation test. We investigated the relationship between the peak cortisol response to insulin-induced hypoglycemia and daily cortisol production rate (CPR) to ascertain whether provocative tests are accurate in indicating the need to initiate lifelong glucocorticoid replacement.
Patients And Methods:
Ten patients (five male; mean age, 44 +/- 13 yr) with pituitary disease and with demonstrably suboptimal peak cortisol response (350-500 nmol/liter) to insulin-induced hypoglycemia, underwent CPR measurement by isotope dilution using gas chromatography-mass spectrometry and 24-h urinary free cortisol (UFC).
Results:
The median baseline and peak cortisol attained with hypoglycemia were 284 (164-323) and 473.5 (366-494) nmol/liter, respectively. A strong positive correlation was seen between peak stimulated cortisol and CPR (adjusted for body surface area) (r = 0.75; P = 0.02), and in all patients CPR [4.6 (2.9-15.1) mg/d x m(2)] was within the reference range (2.1-12 mg/d x m(2)) or elevated (one patient). A wide range was found for 24-h UFC [116.5 (20.5-265.9) nmol/liter] in this group of patients, and this parameter lacked significant correlation with either serum cortisol concentration or CPR.
Conclusion:
This is the first study to demonstrate a significant correlation between CPR and peak cortisol values during hypoglycemic challenge. An inadequate cortisol response to hypoglycemia suggests the need for glucocorticoid cover at times of stress, but these data indicate that a suboptimal peak cortisol does not equate to a low CPR and should not be an automatic indication for lifelong glucocorticoid replacement therapy. UFC bears no relation to serum cortisol or CPR and is therefore unhelpful in assessment of such patients.


Related Concept Videos
 01:19
Cushing Syndrome II: Pathophysiology
 01:26
Cushing Syndrome I: Introduction
 01:37
Hypothalamic-Pituitary Axis
 01:27
Adrenal Gland Disorders
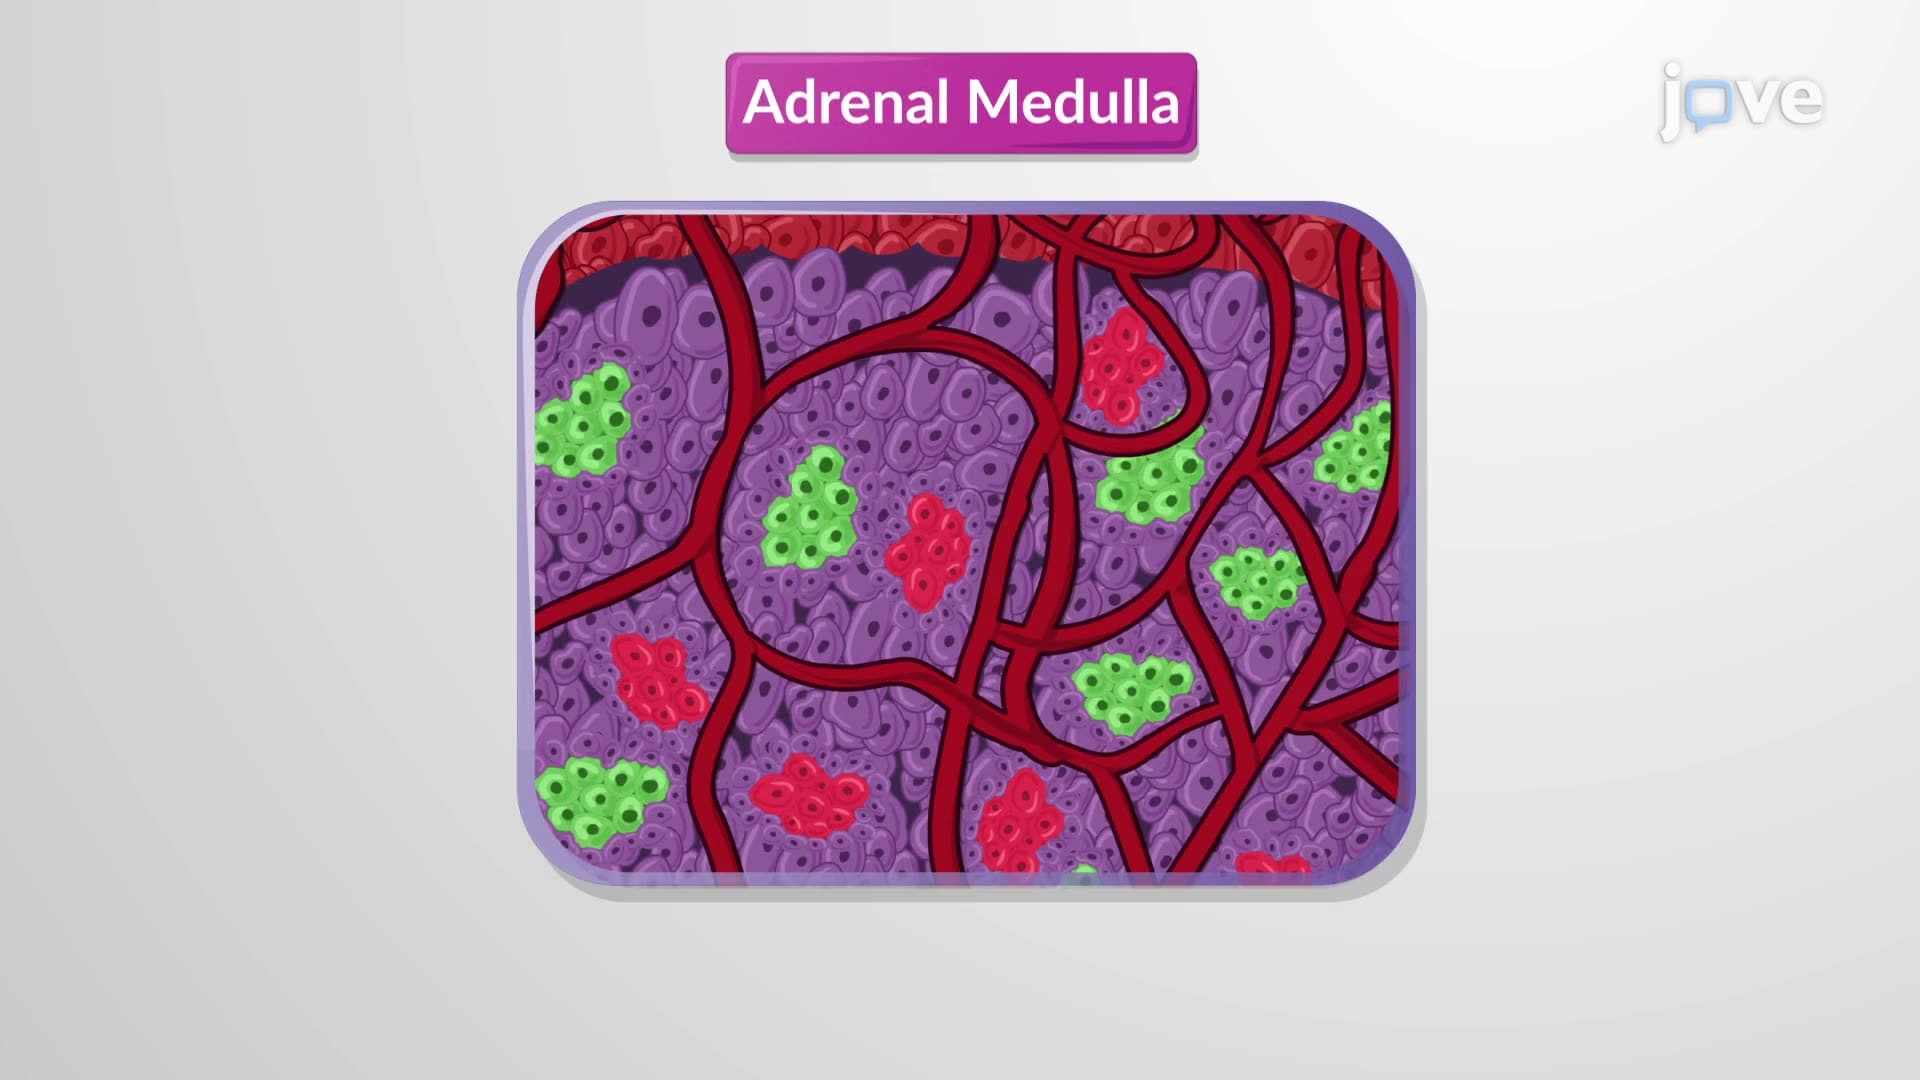
Adrenal insufficiency, characterized by insufficient cortisol and aldosterone production, leads to conditions like Addison's disease. This disorder, affecting the adrenal cortex, exhibits symptoms such as skin bronzing, dehydration, low blood pressure, fatigue, and weight loss. Congenital adrenal hyperplasia, a genetic ailment causing...
 01:31
Hormones of the Adrenal Glands
The adrenal cortex, a powerhouse of hormone synthesis, generates over two dozen corticosteroid hormones. The zona glomerulosa produces mineralocorticoids, exemplified by aldosterone, influencing the electrolyte composition of body fluids. The synthesis of glucocorticoids such as cortisol and corticosterone...
 01:24
Physiological Foundation of Stress
Role of the Sympathetic Nervous System
Adrenaline triggers the...