Related Experiment Video
Updated: Jun 25, 2026


A Model of Long-Term Ventricular Fibrillation in Isolated Rat Hearts
Published on: February 17, 2023
Increased cycle length during long-duration ventricular fibrillation is caused by decreased upstroke velocity as well
Peter G Robertson1, Jian Huang, Kang A Chen
1Department of Medicine, Division of Cardiovascular Disease, University of Alabama at Birmingham, Birmingham, Alabama 35294-0007, USA.

Insights
Ventricular fibrillation (VF) cycle length increases due to longer diastolic intervals, not action potential duration. This is caused by poor wavefront propagation and ischemia during VF.
Area of Science:
- Cardiovascular Physiology
- Electrophysiology
Background:
- Ventricular fibrillation (VF) is characterized by progressively increasing cycle length (CL).
- Understanding the mechanisms behind CL changes is crucial for managing VF.
Purpose of the Study:
- To determine if increased CL in VF is caused by prolonged diastolic interval (DI) or action potential duration (APD).
- To investigate if increased DI is solely due to postrepolarization refractoriness.
Main Methods:
- Recorded VF in swine using epicardial plaque and microelectrode for 20 minutes.
- Calculated CL, APD, DI, action potential amplitude (APA), and V(max) over time.
- Estimated refractory period and performed rapid pacing to assess refractoriness.
Main Results:
- CL, DI, and minimum DI (DI(min)) increased significantly during VF progression.
- APD, V(max), and APA decreased significantly.
- DI(min) at 20 minutes was not significantly different from mean DI at VF onset.
Conclusions:
- Increased CL in VF is primarily due to increased DI, while APD shortens.
- The myocardium remains excitable during a significant portion of the DI.
- Poor wavefront propagation, linked to decreased APA and V(max) from ischemia, contributes to increased DI beyond postrepolarization refractoriness.
Background:
Cycle length (CL) increases as ventricular fibrillation (VF) progresses.
Objective:
The purpose of this study was to test the hypotheses that increased CL is due to increased diastolic interval (DI), not increased action potential duration (APD), and that the DI increase is not solely due to increased postrepolarization refractoriness.
Methods:
In 10 swine, VF was recorded for 20 minutes using a floating microelectrode through a hole in a 504-electrode epicardial plaque. Mean APD, DI, action potential amplitude (APA), maximum change in voltage during the AP upstroke (V(max)), and CL were calculated from the floating microelectrode recordings each minute of VF. The refractory period was estimated from the minimum DI (DI(min)). In two animals, rapid pacing was performed to gauge refractoriness.
Results:
As VF progressed, CL, DI, and DI(min) increased (P <.05), whereas APD, V(max), and APA decreased (P <.05). At 20 minutes, DI(min) was not different from mean DI at VF onset. Pacing captured, but 53% of paced wavefronts blocked within the plaque.
Conclusion:
Increasing CL in VF is due to increased DI and not APD, which shortens. The increase in DI(min) over time is much less than the increase in mean DI, indicating that the myocardium is excitable during much of the DI. This finding, along with the ability to pace at a CL shorter than the native VF CL and the poor paced wavefront propagation, suggests that the increase in DI is due not only to increased postrepolarization refractoriness but also to poor wavefront propagation because of decreased APA and V(max) secondary to global ischemia caused by VF.

Related Concept Videos
 01:29
Disturbances in Heart Rhythm
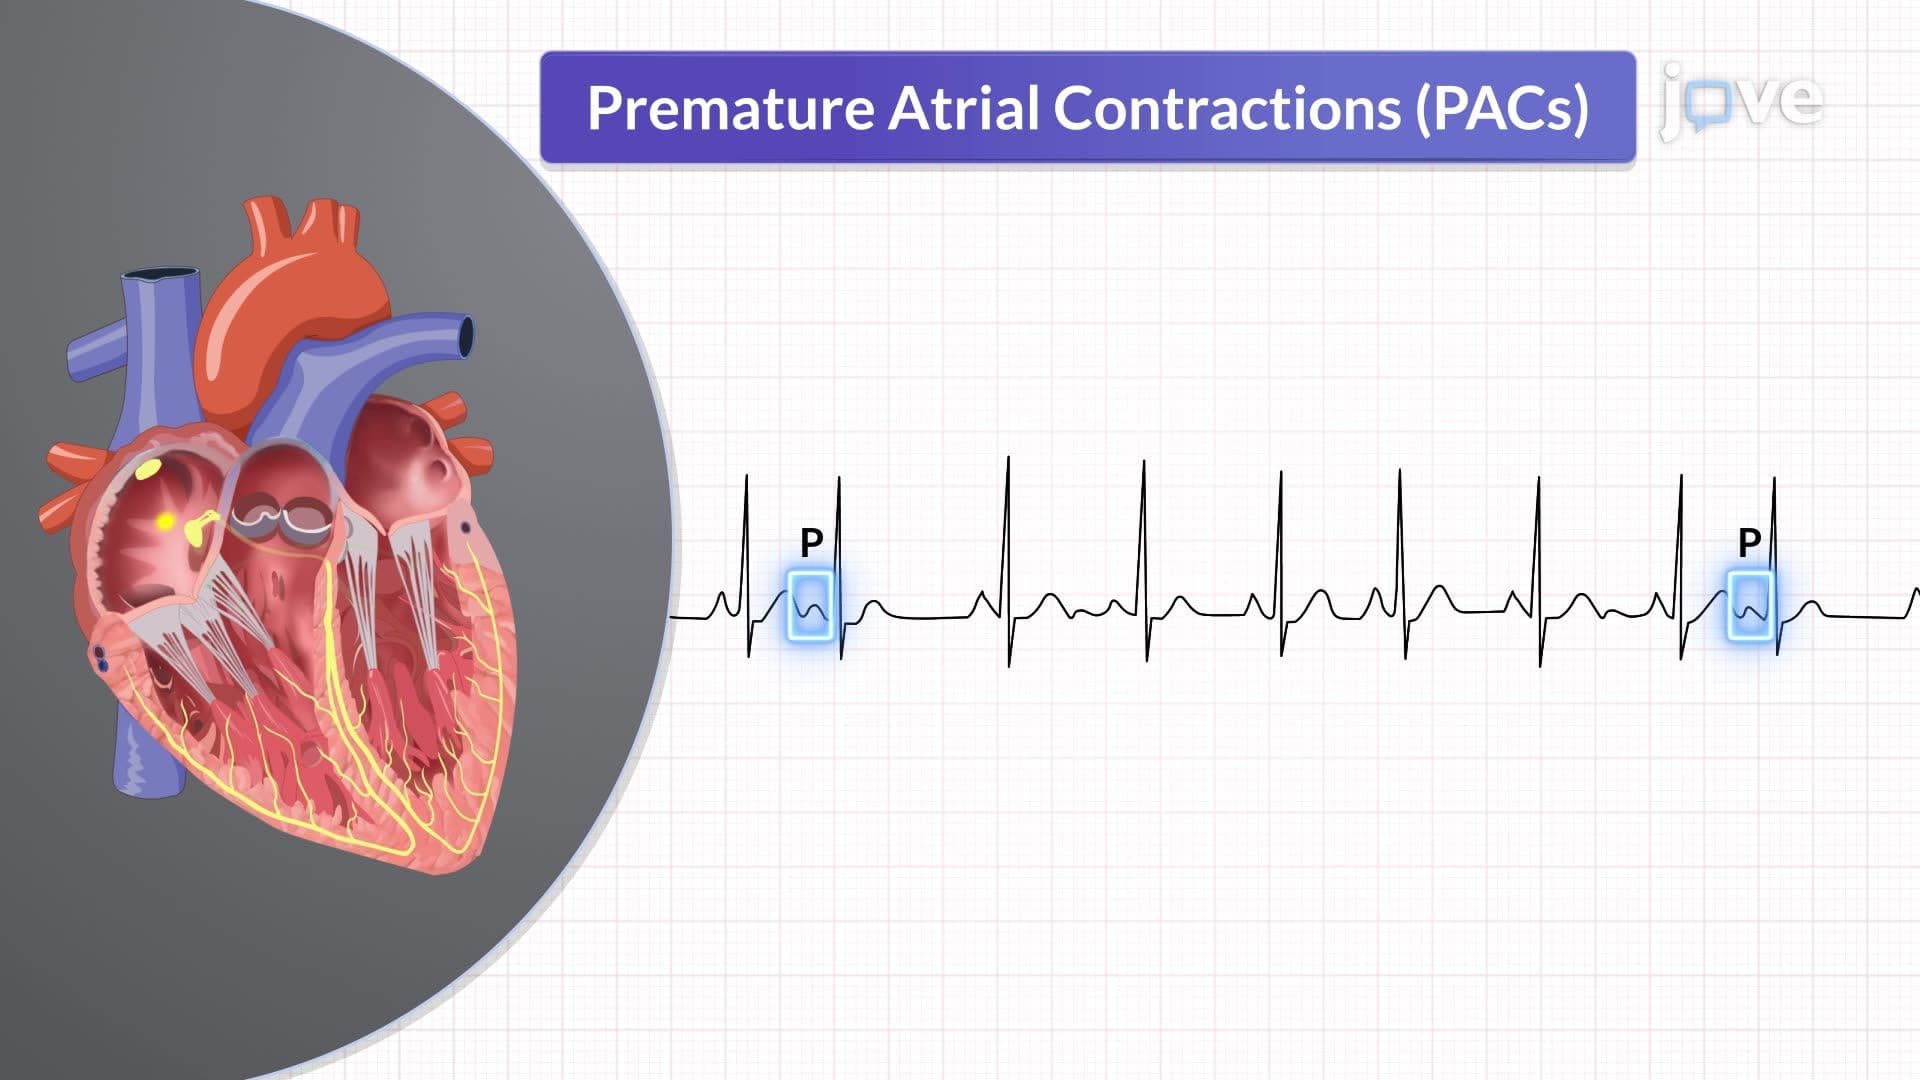
Arrhythmias are categorized by their speed, rhythm, and origin. A slow heart...
 01:29
Dysrhythmias III: Characteristics of Dysrhythmias
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias
 01:30
Cardiac Action Potential
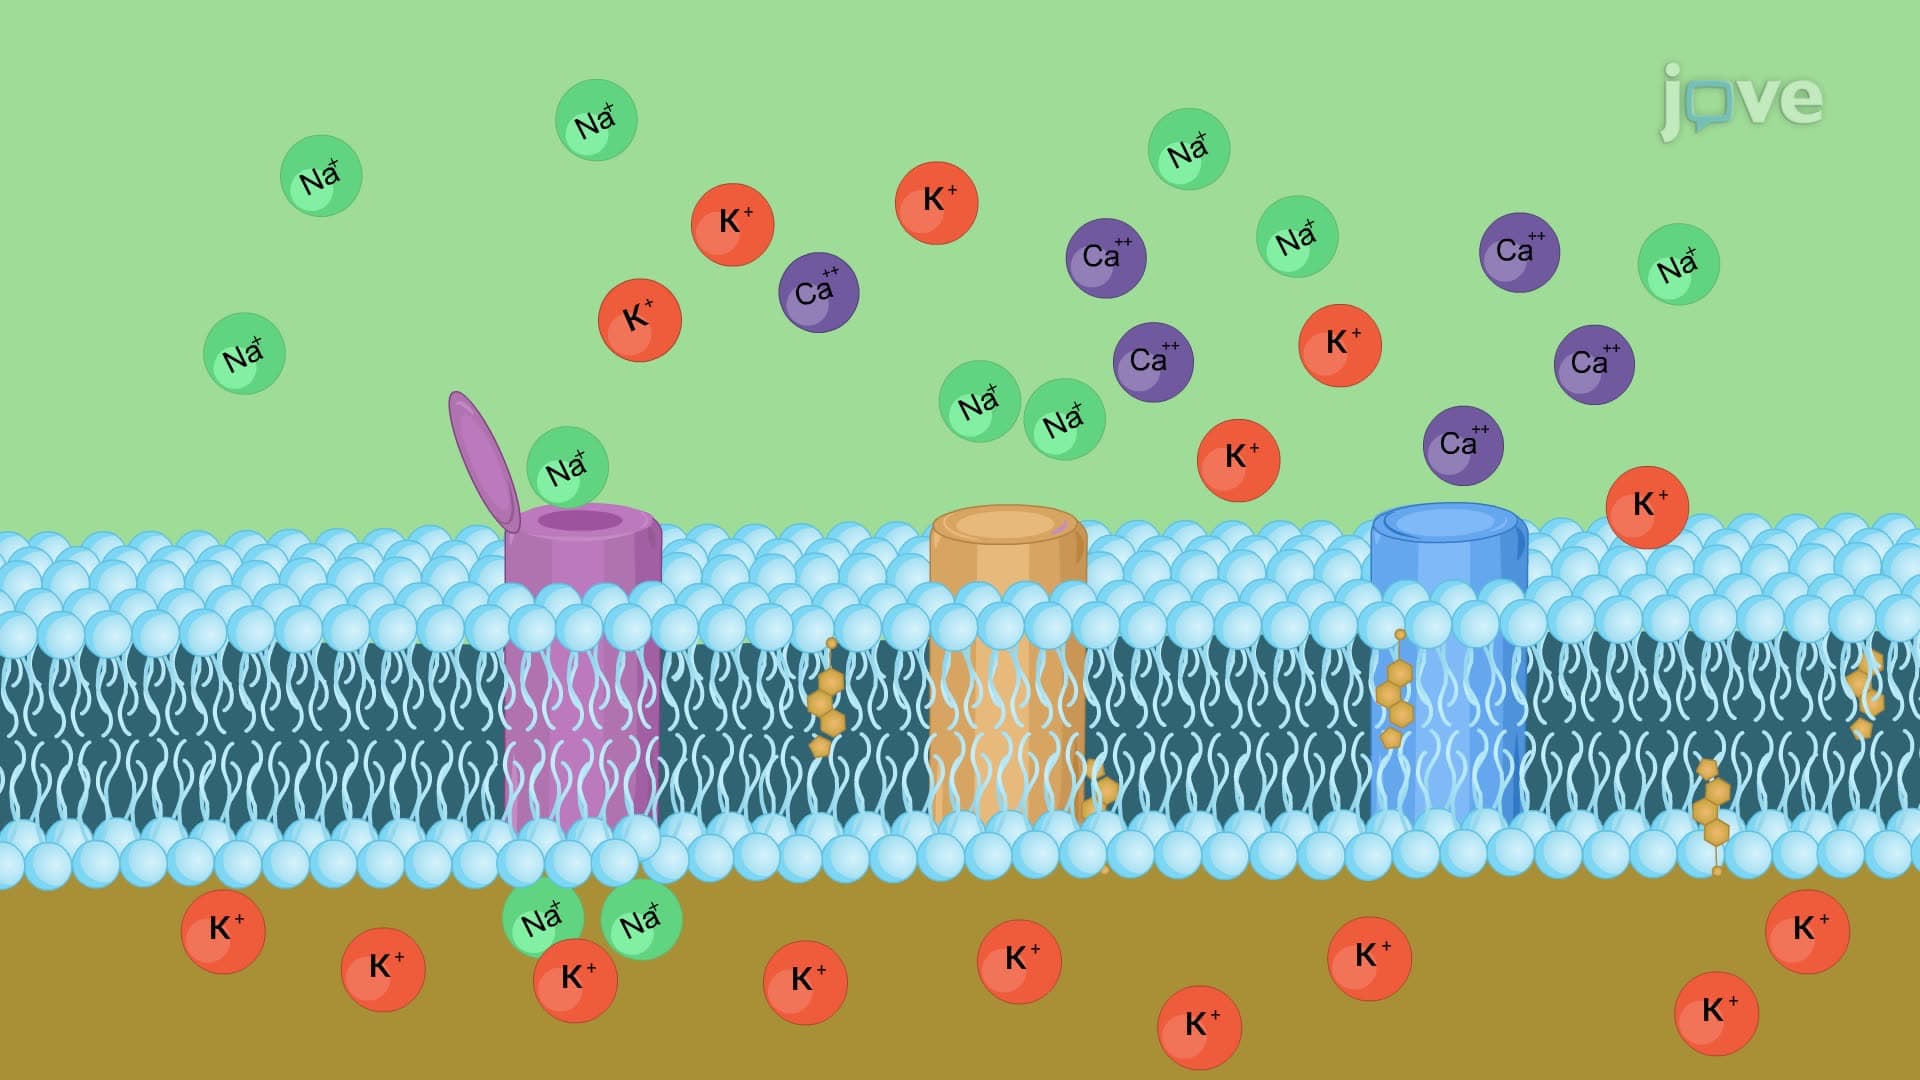
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials
 01:29
Heart Failure II: Pathophysiology
 01:18
Dysrhythmias IV: Characteristics of Bradyarrhythmias