Related Experiment Video
Updated: Jun 25, 2026


Anogenital Distance and Perineal Measurements of the Pelvic Organ Prolapse (POP) Quantification System
Published on: September 20, 2018
Risk factors for 3rd and 4th degree perineal tear
1Department of Obstetrics and Gynaecology, North Devon District Hospital, Barnstaple, UK. oeskandar@yahoo.com

We reviewed 3,038 deliveries at our hospital, over a period of 2 years (2005 and 2006) to identify risk factors for 3rd and 4th degree perineal tear. We used the hospital database and labour ward registry book and reviewed patients' record notes. After excluding elective and emergency caesarean sections, 2,278 women had delivered vaginally, from which 36 patients had 3rd/4th degree perineal tears as defined by the RCOG Green top guidelines No 29 (2007). A total of 2,242 women who delivered vaginally without 3rd/4th degree perineal tears were used as controls in this study. The rate of 3rd/4th degree perineal tear was 1.18% for all deliveries and 1.58% for vaginal deliveries. Occiptoposterior position during delivery (OR: 69.8), primigravida (OR: 5.8), and high birth weight (OR: 1.19) are risk factors for anal sphincter tear. However, induction of labour (OR: 0.71), use of medio-lateral episiotomy (OR: 0.35), epidural analgesia (OR: 0.88) and instrumental delivery of occipitoanterior position (OR: 0.77) reduced the risk of severe perineal tear. Primipara and occipitoposterior position (OP) during delivery are the only statistically significant risks for the occurrence of severe perineal damage. High birth weight is a risk factor but it is not statistically significant. Instrumental delivery of OP position is a highly statistically significant risk factor. On the other hand, induction of labour (IOL), epidural analgesia and instrumental delivery for occipitoanterior position are protective factors against anal sphincter injury, although they did not reach statistical significance.
We reviewed 3,038 deliveries at our hospital, over a period of 2 years (2005 and 2006) to identify risk factors for 3rd and 4th degree perineal tear. We used the hospital database and labour ward registry book and reviewed patients' record notes. After excluding elective and emergency caesarean sections, 2,278 women had delivered vaginally, from which 36 patients had 3rd/4th degree perineal tears as defined by the RCOG Green top guidelines No 29 (2007). A total of 2,242 women who delivered vaginally without 3rd/4th degree perineal tears were used as controls in this study. The rate of 3rd/4th degree perineal tear was 1.18% for all deliveries and 1.58% for vaginal deliveries. Occiptoposterior position during delivery (OR: 69.8), primigravida (OR: 5.8), and high birth weight (OR: 1.19) are risk factors for anal sphincter tear. However, induction of labour (OR: 0.71), use of medio-lateral episiotomy (OR: 0.35), epidural analgesia (OR: 0.88) and instrumental delivery of occipitoanterior position (OR: 0.77) reduced the risk of severe perineal tear. Primipara and occipitoposterior position (OP) during delivery are the only statistically significant risks for the occurrence of severe perineal damage. High birth weight is a risk factor but it is not statistically significant. Instrumental delivery of OP position is a highly statistically significant risk factor. On the other hand, induction of labour (IOL), epidural analgesia and instrumental delivery for occipitoanterior position are protective factors against anal sphincter injury, although they did not reach statistical significance.
Related Concept Videos
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:26
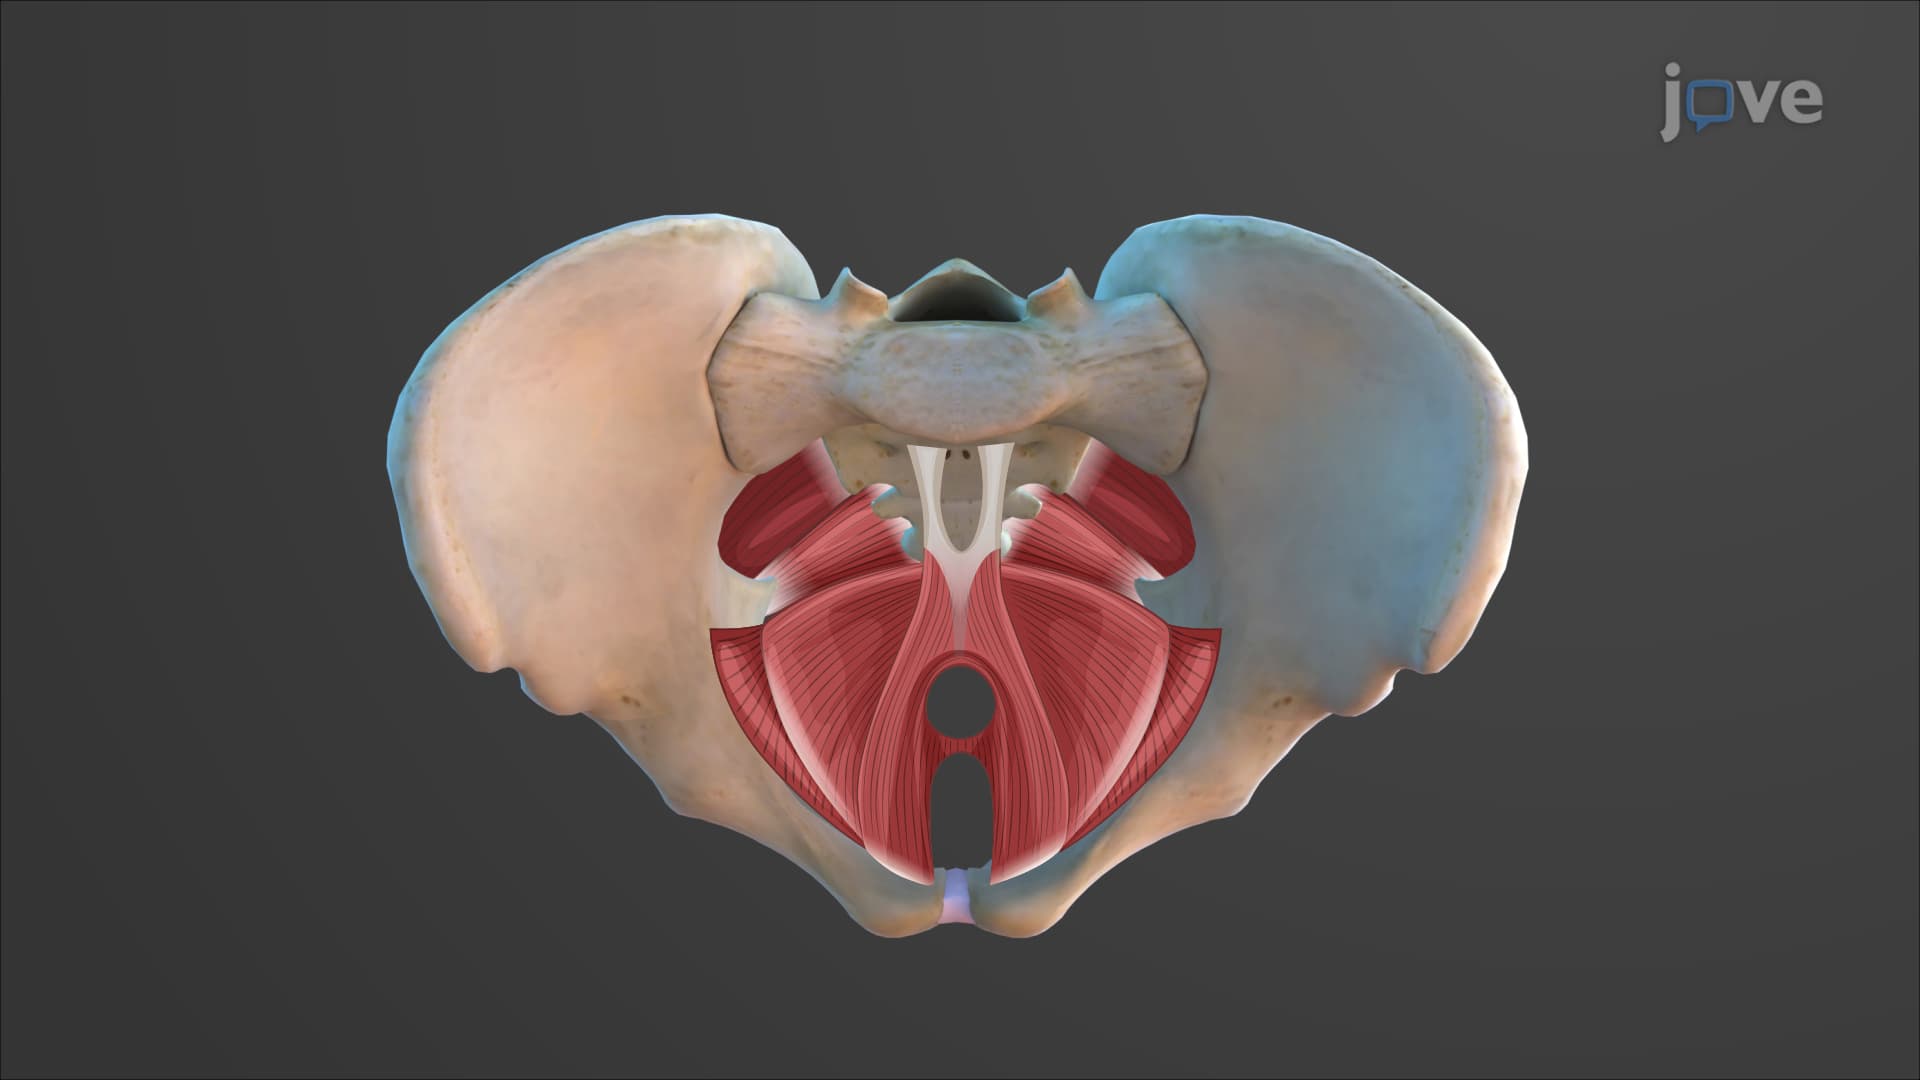
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:25
Peritoneal Dialysis II: Peritoneal Dialysis Systems and Complications
 01:26
Aneurysm III: Interprofessional Care
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus.