Related Experiment Video
Updated: Jun 24, 2026
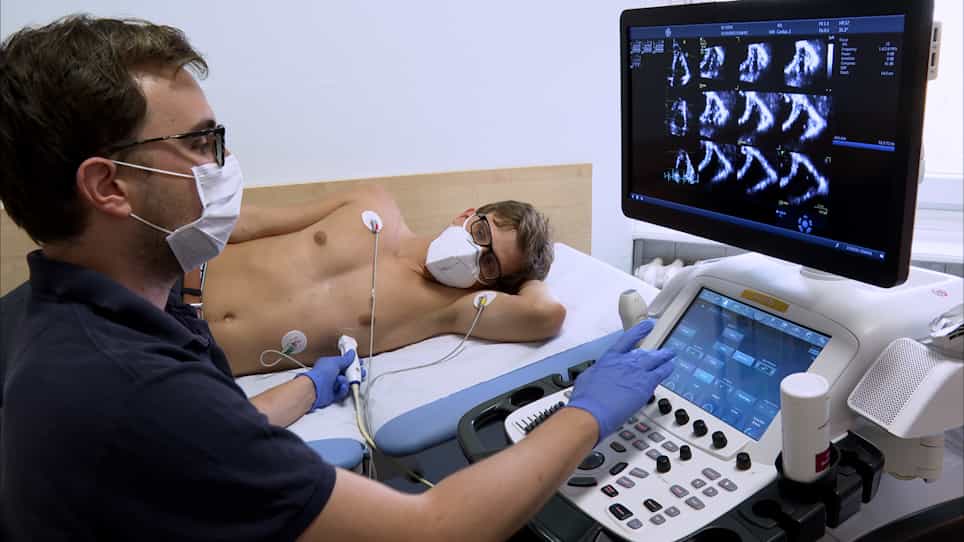
Morphological and Functional Assessment of the Right Ventricle Using 3D Echocardiography
Published on: October 28, 2020
Prevalence of ventricular discordance and its relation to functional capacity in idiopathic dilated cardiomyopathy
Gunnar Plehn1, Julia Vormbrock, Lutz Lefringhausen
1Department of Cardiology and Angiology, Marienhospital Herne, University of Bochum, Germany. gunnar.plehn@ruhr-uni-bochum.de

Insights
In idiopathic dilated cardiomyopathy (IDC), left and right ventricular dilatation varies. Ventricular volume discordance strongly correlates with left ventricular enlargement but adds little to understanding exercise limitations beyond left ventricular measurements.
Area of Science:
- Cardiology
- Medical Imaging
- Heart Failure Research
Background:
- Idiopathic dilated cardiomyopathy (IDC) is characterized by left ventricular (LV) dilatation, but right ventricular (RV) involvement varies.
- The prevalence and functional significance of relative biventricular dilatation in IDC remain understudied.
- Cardiac magnetic resonance imaging (MRI) offers a comprehensive tool for assessing ventricular morphology and function.
Purpose of the Study:
- To investigate the prevalence and functional importance of relative left and right ventricular dilatation in IDC patients using cardiac MRI.
- To determine the correlation between ventricular volume discordance and the extent of LV enlargement.
- To assess the contribution of biventricular assessment to understanding exercise capacity limitations in IDC.
Main Methods:
- Prospective study of 58 IDC patients with LV ejection fraction <40% and NYHA class ≥2.
- Cardiac MRI performed on a 1.5 Tesla scanner for detailed RV and LV dimensional and functional analysis.
- Cardiopulmonary exercise testing used to evaluate exercise capacity; patients stratified into tertiles by LV end-diastolic volume.
Main Results:
- Significant heterogeneity in relative RV and LV dilatation observed in IDC patients compared to controls.
- Strong correlation (r=0.8, P<0.001) found between ventricular volume discordance and LV enlargement.
- LV/RV volume ratios differed significantly across tertiles (P<0.001); LV ejection fraction was the sole independent predictor of maximum oxygen consumption.
Conclusions:
- Ventricular volume discordance in IDC is strongly linked to the degree of LV enlargement.
- Comprehensive biventricular MRI assessment provides limited additional insight into exercise tolerance mechanisms compared to isolated LV evaluation.
- LV function remains the primary determinant of exercise capacity in IDC patients.
Introduction:
Although left ventricular (LV) dilatation is the most distinguishing morphologic feature of idiopathic dilated cardiomyopathy (IDC), right ventricular (RV) dilatation may variably contribute to total cardiac enlargement. The prevalence and functional importance of the relative degree of left and right ventricular dilatation has not been comprehensively studied using cardiac magnetic resonance imaging (MRI).
Methods:
Our prospective study included 58 consecutive IDC patients with a LV ejection fraction <40% and NYHA functional class > or =2. MRI was performed with a 1.5 Tesla scanner for RV and LV dimensional and functional analysis. Cardiopulmonary exercise testing was used for evaluation of exercise capacity. Patients were grouped into tertiles based on the distribution of LV end-diastolic volume.
Results:
Compared to control subjects a considerable heterogeneity in the relative degree of left and right ventricular dilatation was noted in IDC patients. Within the entire patient group, a strong correlation between the degree of ventricular volume discordance and the extent of LV enlargement was observed (r = 0.8; P < 0.001). Tertile analysis revealed that the LV/RV volume ratio significantly differed in the three subgroups of patients (1.0 +/- 0.3 vs. 1.5 +/- 0.4 vs. 2.1 +/- 0.9; P < 0.001). Only weak correlations between MRI data and patients' functional capacity were found. LV ejection fraction was identified as the only independent predictor of maximum oxygen consumption in our setting.
Conclusion:
In IDC patients the degree of ventricular volume discordance is strongly related to the extent of left ventricular enlargement. However, comprehensive biventricular assessment of cardiac function by MRI adds little to our understanding of the cardiac mechanisms limiting exercise tolerance when compared to exclusive left ventricular measurements.

Related Concept Videos
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:29
Cardiomyopathy IV: Restrictive Cardiomyopathy
 01:25
Cardiomyopathy I: Introduction and Classification
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send blood...
 01:29
Cardiomyopathy V: Interprofessional Care