Related Experiment Video
Updated: Jun 24, 2026


Isolation, Characterization, And High Throughput Extracellular Flux Analysis of Mouse Primary Renal Tubular Epithelial Cells
Published on: June 20, 2018
Southeast Asian AE1 associated renal tubular acidosis: cation leak is a class effect
Stephen Walsh1, Franck Borgese, Nicole Gabillat
1Laboratoire de Biologie et Physiopathologie des Systèmes Intégrés, FRE3094, CNRS-Université de Nice, Bâtiment de Sciences Naturelles, Nice Cedex 2, France. stephen.walsh@ucl.ac.uk

Abstract:
Anion Exchanger 1 (AE1) is present in the erythrocyte and also in the alpha-intercalated cell; different mutations can cause either red cell disease or distal renal tubular acidosis (dRTA). Recently, we described a cation leak property in four dRTA-causing AE1 mutants, three autosomal dominant (AD) European mutants, one autosomal recessive (AR) from Southeast Asia, G701D. G701D had a very large leak property and is unusually common in SE Asia. We hypothesized that this property might confer a survival advantage. We characterized three other AR dRTA-associated AE1 mutants found in SE Asia, S773P, Delta850 and A858D via transport experiments in AE1-expressing Xenopus oocytes. These three SE Asian mutants also had cation leaks of similar magnitude to that seen in G701D, a property that distinguishes them as a discrete group. The clustering of these cation-leaky AE1 mutations to malarious areas of SE Asia suggests that they may confer malaria resistance.
Related Concept Videos
 01:24
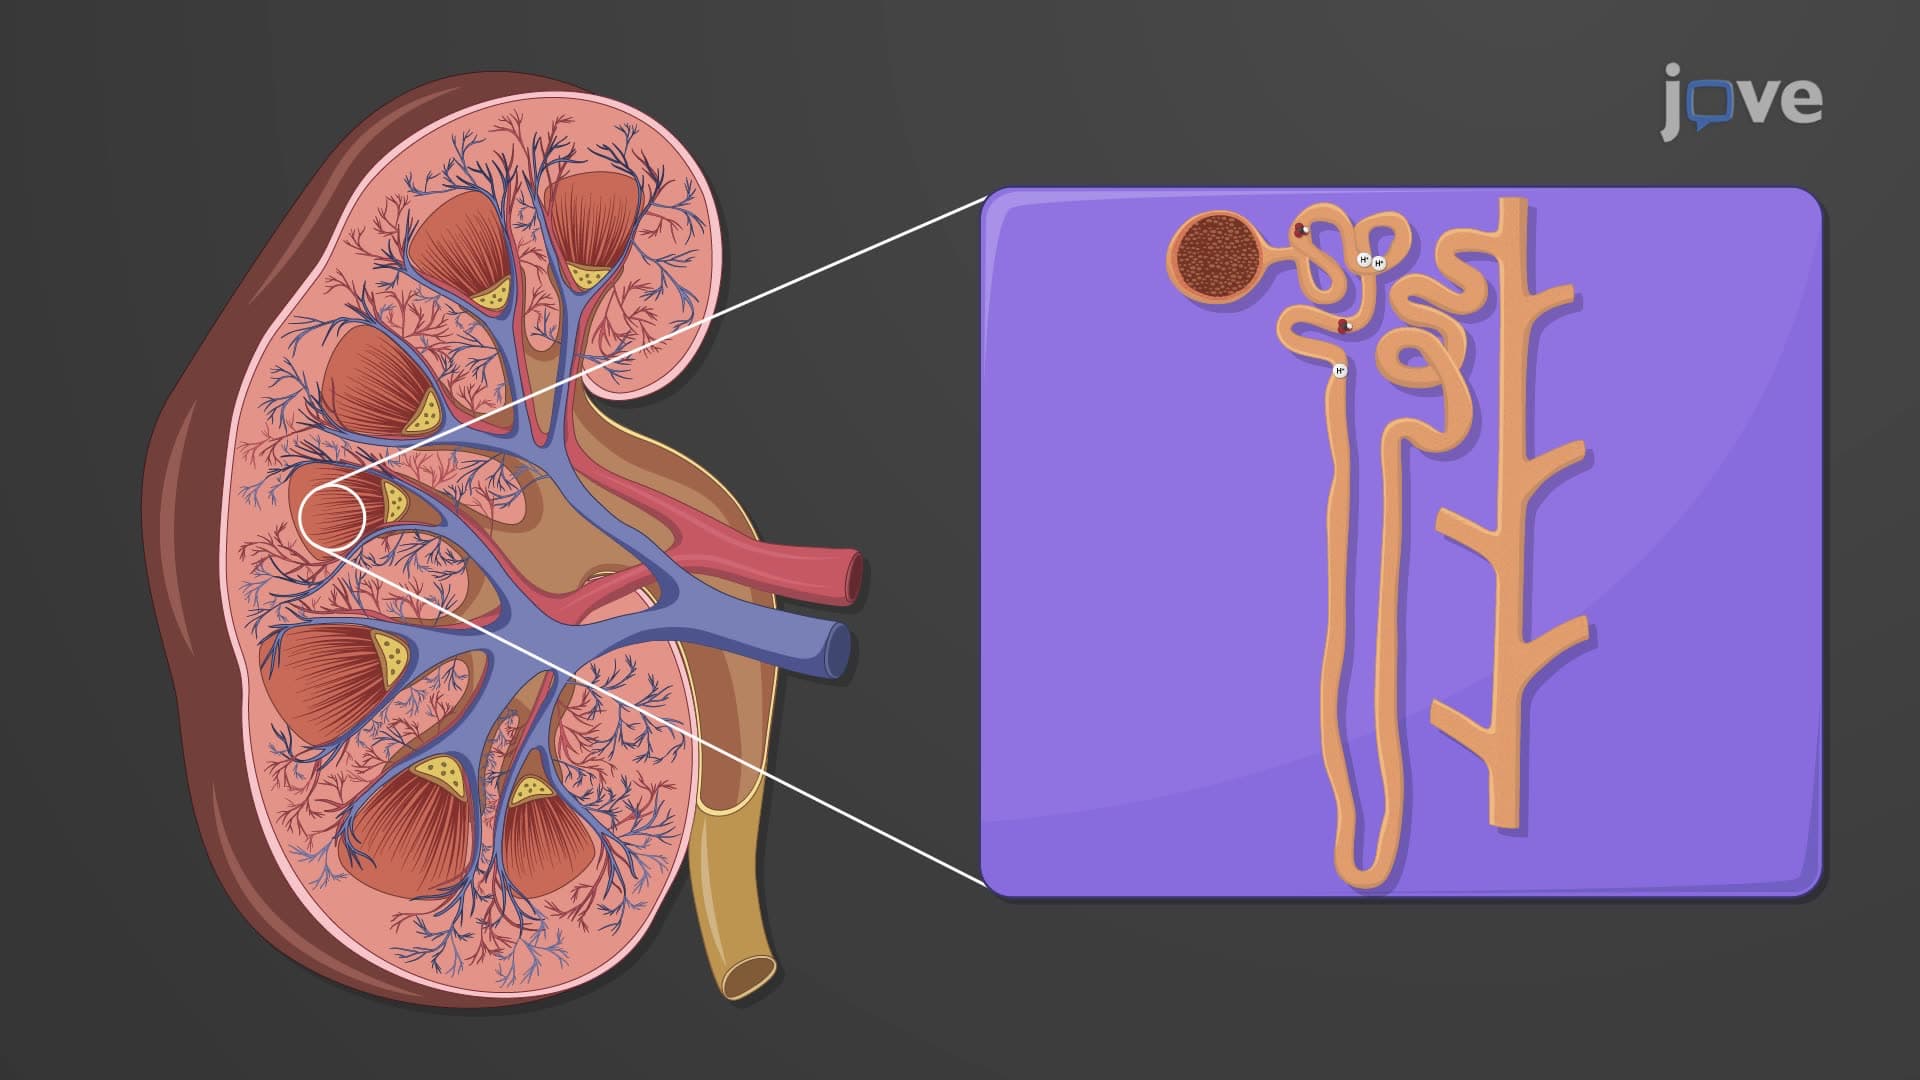
Renal Tubule and Collecting Duct
Proximal Convoluted Tubule (PCT):
The PCT is the initial segment of the renal tubule, extending from the Bowman's capsule that encloses the glomerulus. Its convoluted structure and microvilli-lined cells increase the surface area for reabsorption. The PCT reabsorbs glucose, amino acids, sodium, and water from the filtrate, ensuring essential...
 01:29
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:28
Renal Drug Excretion: Tubular Secretion
 01:22
Acute Kidney Injury I: Introduction
 01:22
Drug Elimination by Renal Route: Tubular Reabsorption
 01:22
Renal Drug Excretion: Effect of Urine pH, Flow Rate, and Drug pKa
The pKa of a drug,...