

Electrophysiological correlates of intermediate syndrome following acute organophosphate poisoning
Pradeepa Jayawardane1, Nimal Senanayake, Andrew Dawson
1South Asian Clinical Toxicology Research Collaboration (SACTRC), Faculty of Medicine, University of Peradeniya, Peradeniya, Sri Lanka. pradeepajayawardane@yahoo.co.uk

Introduction:
Organophosphate (OP) poisoning is a major global health problem. The late onset of respiratory failure associated with intermediate syndrome (IMS) is a major contributor to the high morbidity, mortality, and cost of OP poisoning. This is particularly important as most poisoning occurs in the under-resourced developing world. Repetitive nerve stimulation studies. An understanding of the abnormalities observed in repetitive nerve stimulation studies during the progression and development of IMS spectrum disorder may help clinicians to utilize electrodiagnostic testing in the better management of their patients with acute OP poisoning. In addition, it will allow researchers to interpret future research that utilizes repetitive nerve stimulation as an outcome measure. A review of the clinical and experimental electrophysiological studies in the IMS shows that subclinical electrophysiological abnormalities are common, progressive, and precede the onset of the clinical IMS. Serial repetitive nerve stimulation studies have been most commonly used and are the most accessible for clinicians. Clinical and experimental studies demonstrate a progression through early initial decrement-increment patterns at high rates of stimulations, which correlate with moderate muscle weakness, to decrement-increment patterns at intermediate- and low-frequency stimulations. Progression to a combination of decrement-increment and repetitive fade patterns correlates with clinical deterioration; severe decrement pattern is usually observed immediately before the onset of respiratory failure. Although electrophysiological features closely parallel clinical severity during progression of IMS, the same is not true during recovery. Electrophysiological changes sometimes improve long before the patient recovers normal strength and respiratory function. Intermediate syndrome. Thus, IMS can be regarded as a spectrum disorder affecting the neuromuscular junction (NMJ) with two main forms: a forme fruste variety associated with mild weakness and the classical IMS with weakness of 3/5 or less than 3/5 on the Medical Research Council (MRC) grading; patients in the latter category are at risk of developing late onset respiratory failure. While IMS remains a clinically important entity, the early occurrence of abnormalities on repetitive nerve stimulation studies suggest that this is part of the continuum of nicotinic receptor stimulation.
Conclusions:
Reviewing the anatomical and the functional structure of the NMJ and neuromuscular transmission helps to provide an understanding of the pathophysiological nature of the neuromuscular transmission failure observed in IMS. This includes potential mechanisms of presynaptic feedback which may reduce acetylcholine release and postsynaptic receptor desensitization and provides some explanation for the time course of IMS. It also suggests other potential strategies to reduce OP-induced NMJ toxicity in which repetitive nerve stimulation is likely to be an important tool in judging efficacy.
More Related Videos
 06:45
Electrophysiological Recording of The Central Nervous System Activity of Third-Instar Drosophila Melanogaster
Published on: November 21, 2018
 10:46
Acute In Vivo Electrophysiological Recordings of Local Field Potentials and Multi-unit Activity from the Hyperdirect Pathway in Anesthetized Rats
Published on: June 22, 2017
Related Concept Videos
 01:26
Anticholinesterase Agents: Poisoning and Treatment
Irreversible agents form a strong bond with the cholinesterase enzyme, making it inactive. The breakdown of the phosphorylated enzyme is slower than the...
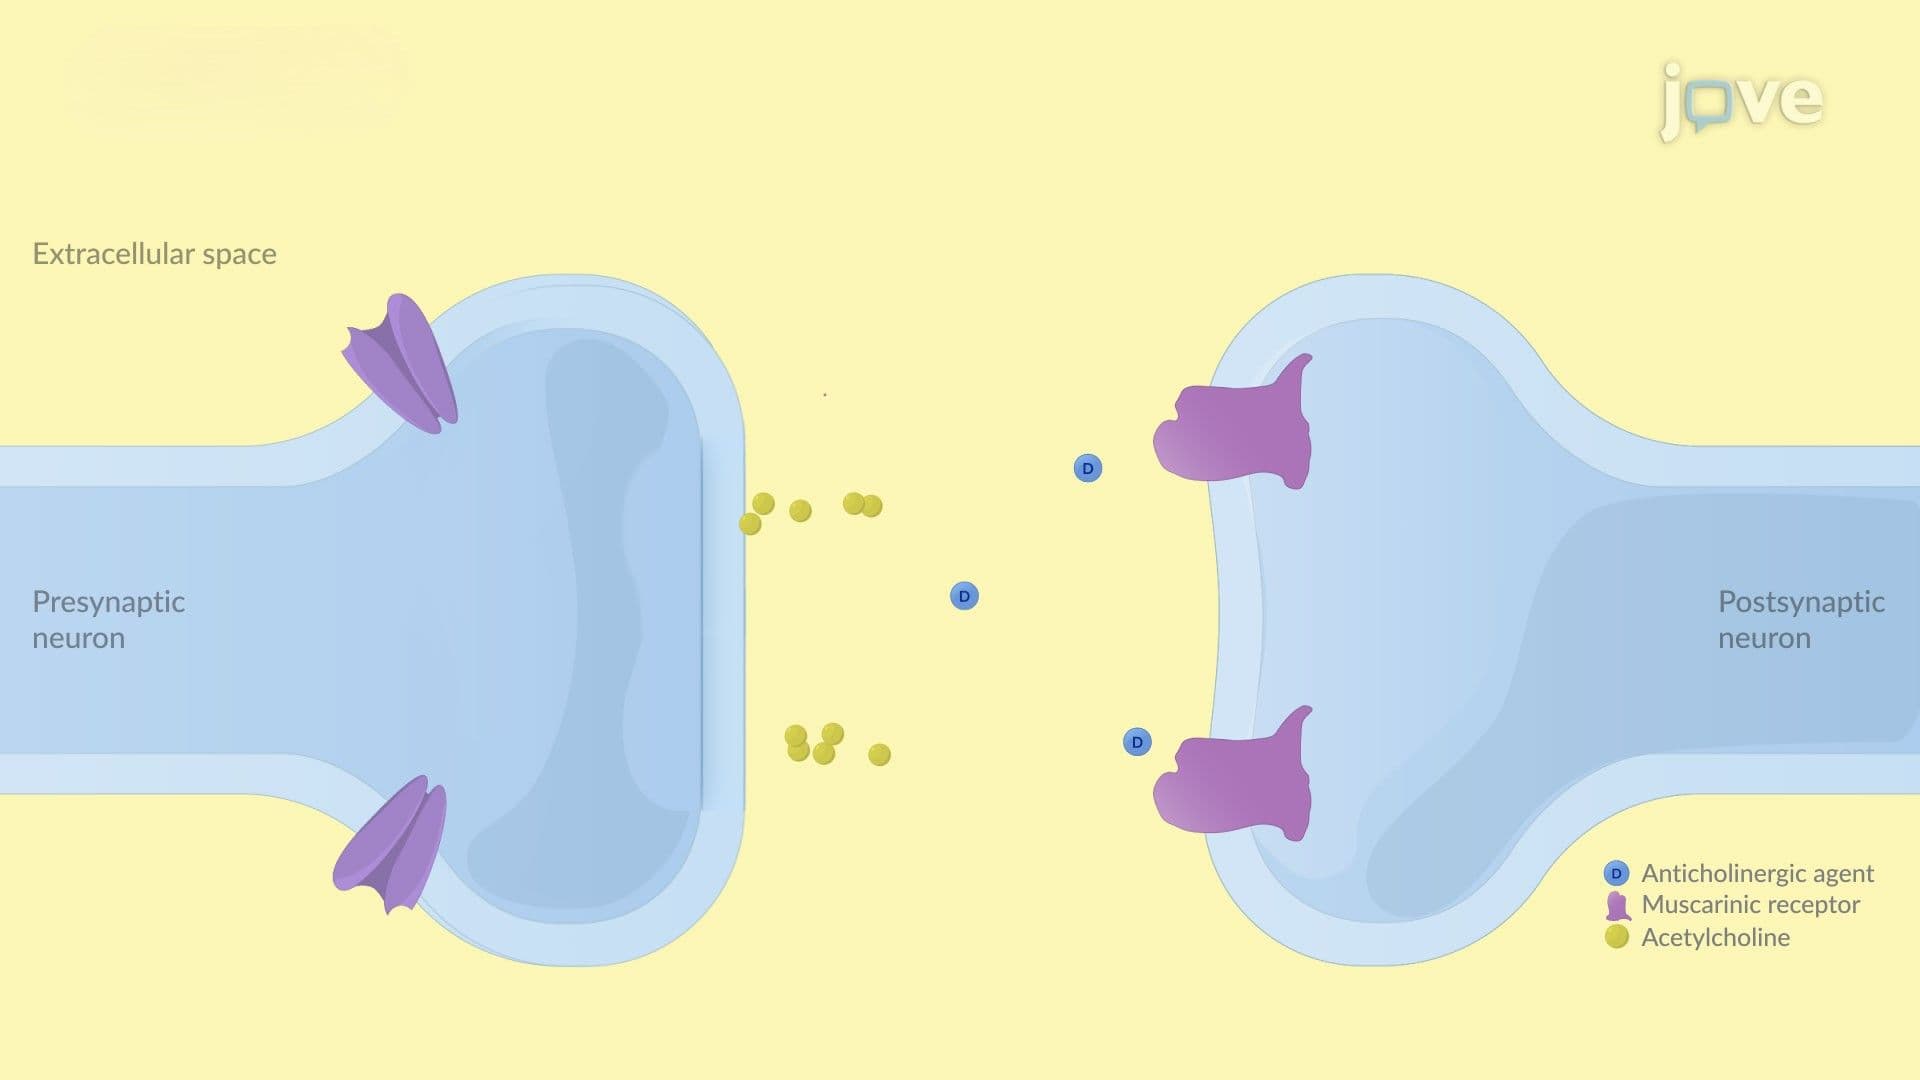 01:30
Toxidromes: Clinical Features
 01:19
Depolarizing Blockers: Pharmocokinetics
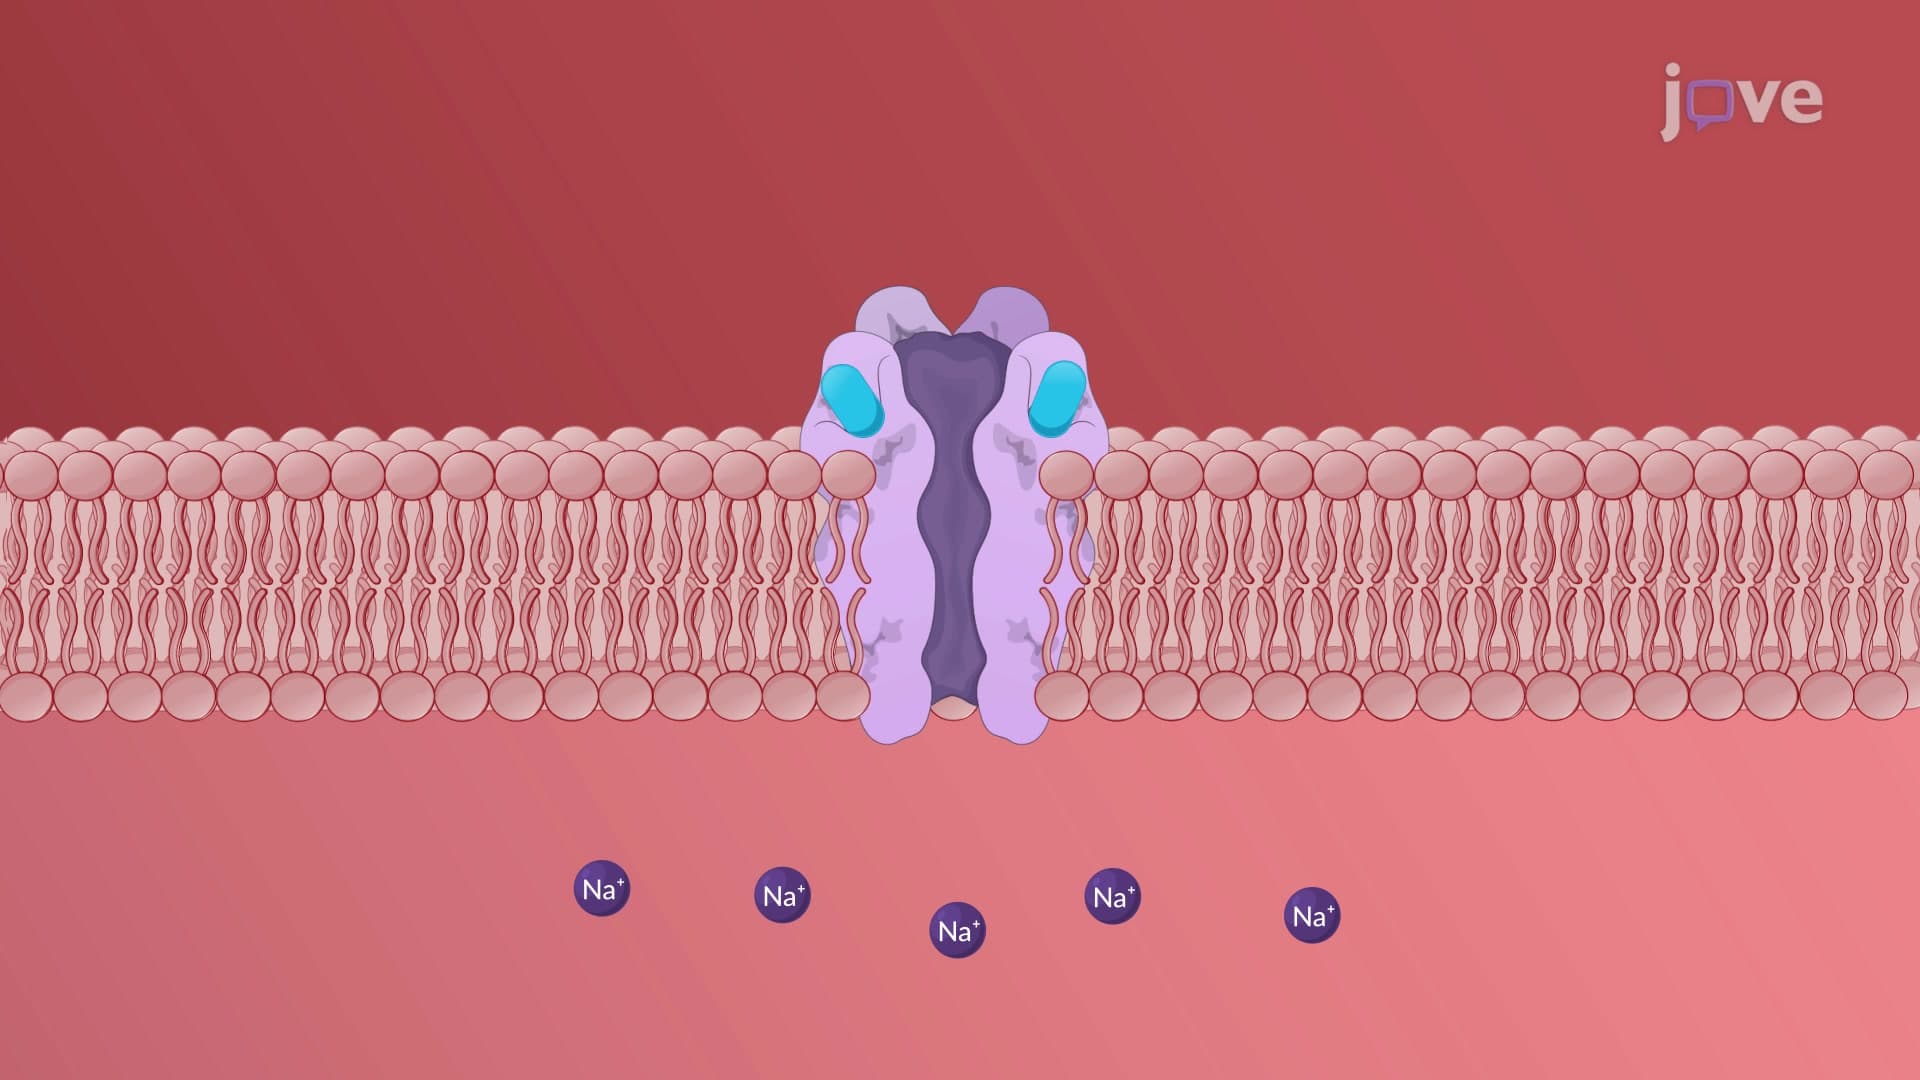 01:28
Depolarizing Blockers: Mechanism of Action
Succinylcholine is the most commonly used depolarizing blocker. Chemically, it constitutes two molecules of acetylcholine joined together by an acetate methyl group. They act on the receptors in the same way as acetylcholine. Because succinylcholine...
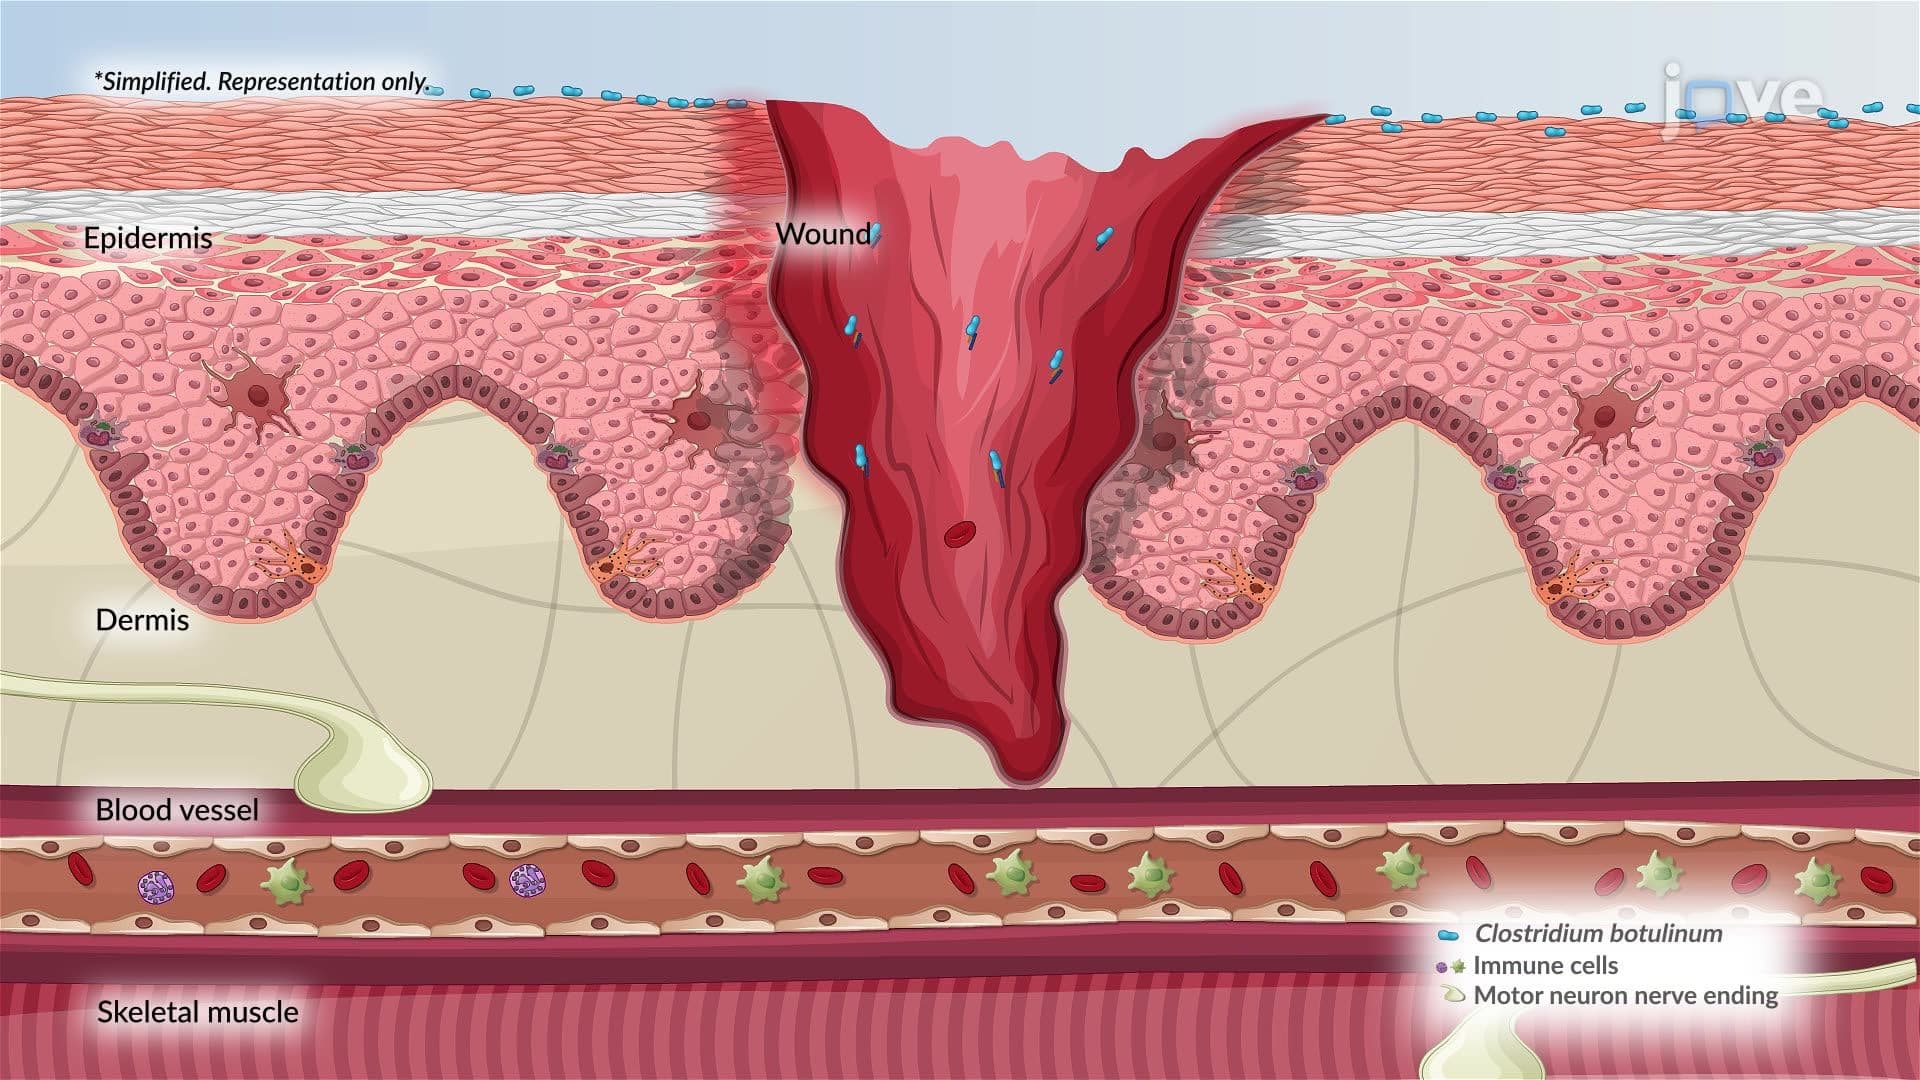 01:22
Botulism
 01:30
Acute Coronary Syndrome III: Diagnostic Studies