Related Experiment Video
Updated: Jun 24, 2026

Behavioral Assessment of Hearing in 2 to 4 Year-old Children: A Two-interval, Observer-based Procedure Using Conditioned Play-based Responses
Published on: January 23, 2017
Infant air and bone conduction tone burst auditory brain stem responses for classification of hearing loss and the
Kathy R Vander Werff1, Beth A Prieve, Lea M Georgantas
1Department of Communication Sciences and Disorders, Syracuse University, Syracuse, New York 13244, USA. kvander@syr.edu

Insights
Diagnosing infant hearing loss (HL) is feasible using tone burst auditory brain stem response (TBABR) and visual reinforcement audiometry (VRA). These methods provide reliable data for early intervention, classifying HL type and severity.
Area of Science:
- Audiology and Hearing Science
- Pediatric Medicine
- Neuroscience
Background:
- Early detection of hearing loss (HL) in infants is crucial for timely intervention and optimal developmental outcomes.
- Existing diagnostic protocols require validation for their efficacy in classifying HL type and severity in young infants.
- Establishing normative data for auditory brain stem response (ABR) and behavioral audiometry is essential for accurate HL diagnosis.
Purpose of the Study:
- To provide normative data for frequency-specific tone burst auditory brain stem response (TBABR) thresholds by air conduction (AC) and bone conduction (BC) in early infancy.
- To establish ear-specific behavioral thresholds in infants by one year of age.
- To analyze the relationship between TBABR and behavioral thresholds for accurate HL classification and prediction.
Main Methods:
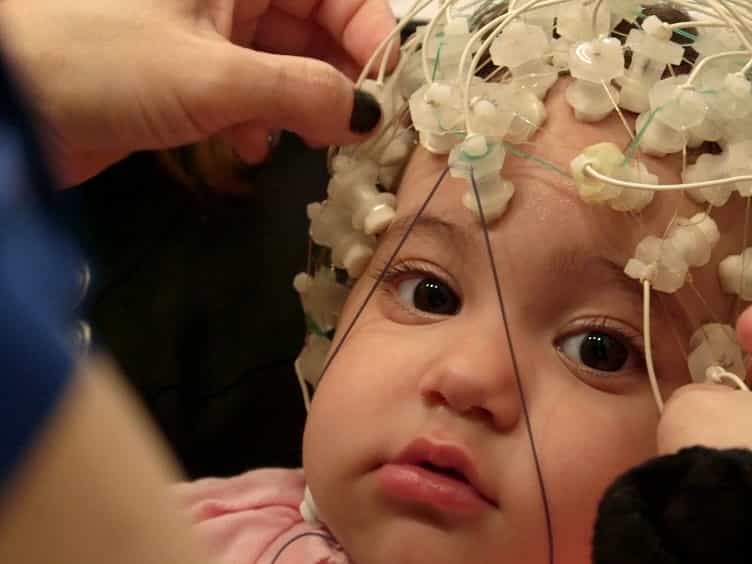
- AC- and BC-TBABRs were measured in infants younger than 3 months under natural sleep.
- Visual reinforcement audiometry (VRA) was used to obtain behavioral thresholds in infants around 10 months of age.
- Data analysis focused on threshold and latency differences between AC and BC, and correlations between TBABR and VRA results.
Main Results:
- Mean TBABR thresholds in normal-hearing infants were comparable to existing data.
- A consistent air-bone gap (ABG) of 15 dB was observed at 500 Hz in normal-hearing infants, with larger gaps in those with conductive HL.
- Strong correlations (r = 0.86-0.91) were found between TBABR and VRA thresholds, indicating good prediction of behavioral responses.
Conclusions:
- AC- and BC-TBABRs are readily obtainable in sleeping infants and effectively classify HL type and severity based on ABG.
- Latency differences in TBABR and click ABR distinguish between infants with and without ABGs.
- Clinically feasible protocols for TBABR and VRA meet early intervention guidelines, enabling accurate HL diagnosis in infants.
Objective:
A clinical protocol for diagnosing hearing loss (HL) in infants designed to meet early intervention guidelines was used with the goals of providing normative data for (1) frequency-specific tone burst auditory brain stem response (TBABR) thresholds by air conduction (AC) and bone conduction (BC) in early infancy used to classify type and severity of HL, (2) ear-specific behavioral thresholds for these same infants by 1 yr of age, and (3) the relationship between TBABR thresholds and behavioral thresholds for this group of infants.
Design:
AC- and BC-TBABRs were measured in young infants (mean age, <3 mo) under natural sleep to classify the type and severity of HL (conductive, sensorineural, or mixed). A small group of normal-hearing adults undergoing the same TBABR protocol served as a control group. Threshold and latency data for AC- and BC-ABR were analyzed for infants classified as having normal hearing and for those with and without conductive HL. The ability to detect conductive HL based on ABR latencies evoked by clicks presented at 80 dB nHL was assessed. Behavioral thresholds using visual reinforcement audiometry (VRA) were measured in infants at a mean age of approximately 10 mo. The relationship between TBABR and behavioral thresholds obtained in infancy was analyzed, and the prediction of behavioral thresholds from TBABR thresholds was examined.
Results:
Mean TBABR thresholds in young infants with normal hearing tested under natural sleep were similar to previously published data. The relationship between AC- and BC-TBABR thresholds differed as a function of stimulus frequency for infants but not adults. A mean air-bone gap (ABG) of 15 dB was present at 500 Hz even in normal-hearing infants, with those infants classified as having conductive HL presenting with substantially larger ABGs. Wave V latency functions for AC- and BC-TBABR also differed between infants and adults as a function of frequency. Infant BC-TBABR latencies were well matched between those with normal hearing and conductive HL, whereas AC-TBABR latency functions separated these groups. Mean VRA thresholds using insert phones in normal-hearing infants tested were between 14 and 17 dB HL for all three test frequencies at a mean age of 9.7 mo. Correlations between TBABR and VRA thresholds, both obtained during infancy, were strong for all three test frequencies (r = 0.86, 0.90, and 0.91 for 500, 2000, and 4000 Hz, respectively).
Conclusions:
AC- and BC-TBABR results can be readily obtained in young infants under natural sleep and were used to classify the type of HL based on the absolute threshold and the size of the ABG. Differences in wave V latency functions for TBABR by AC and BC and wave I and V latencies of the high-level click ABR also distinguish between infants with and without TBABR ABGs. Ear-specific behavioral responses can be obtained at levels under 20 dB HL in normal-hearing infants younger than 1 yr using VRA, and these behavioral thresholds correlate well with TBABR thresholds obtained on average 6.5 mo previously in this population. The current results suggest that protocols for obtaining AC- and BC-TBABR and behavioral thresholds that meet guidelines for early intervention are clinically feasible.
Related Concept Videos
 01:31
Hearing
 01:13
The Cochlea
 01:15
Auditory Pathway
When viewed cross-sectionally, the cochlea reveals the scala vestibuli and scala tympani flanking the...
 01:21
Perceiving Loudness, Pitch, and Location
Place theory, or place coding, suggests that different pitches are heard because various sound waves activate specific locations along the cochlea's basilar membrane. The brain determines the pitch of a sound by identifying...
 01:16
Anatomy of the Ear
 00:53
Sound Intensity Level
The human ear can perceive an extensive range of sound intensity, necessitating the use of the logarithmic scale to define a physical quantity—the intensity level. It is a ratio of two intensities and hence a...