Related Experiment Video
Updated: Jun 24, 2026


Simultaneous Laryngopharyngeal and Conventional Esophageal pH Monitoring
Published on: December 14, 2020
Influence of esophageal pH recording on physical activity in children
Laurent Michaud1, Françoise Troadec, Laurent Béghin
1Division of Gastroenterology, Hepatology, Lille University Children's Hospital and EA 3925, IFR 114, Lille University 2, Lille, France. l-michaud@chru-lille.fr

Insights
Ambulatory esophageal pH monitoring significantly reduces children's physical activity, particularly high-intensity movements. This reduction may impact the accuracy of gastroesophageal reflux diagnosis.
Area of Science:
- Pediatric Gastroenterology
- Diagnostic Technologies
- Clinical Physiology
Background:
- Gastroesophageal reflux (GER) diagnosis relies on 24-hour pH-metry.
- Ambulatory esophageal pH monitoring reflects daily life but might alter patient behavior.
- The impact of pH monitoring on pediatric physical activity requires investigation.
Purpose of the Study:
- To evaluate the influence of ambulatory esophageal pH recording on physical activity levels in children.
- To quantify changes in physical activity during pH monitoring compared to baseline.
Main Methods:
- Prospective study of 22 children (3-15 years) undergoing ambulatory pH-metry.
- 24-hour physical activity measured using triaxial accelerometers before and during pH monitoring.
- Comparison of physical activity intensity levels (low, moderate, high) using the Wilcoxon signed-rank test.
Main Results:
- Physical activity was 53% lower during pH monitoring (P < 0.0005).
- Low-level activity duration increased (84% vs 73%, P < 0.01).
- Moderate and high-intensity activity durations decreased significantly (P < 0.005 and P < 0.0001).
Conclusions:
- Ambulatory 24-hour esophageal pH recording substantially reduces children's physical activity.
- High-level physical activity is most affected.
- Further research is needed to determine if reduced activity affects pH-metry sensitivity and leads to false negatives.
Objectives:
Twenty-four-hour pH-metry represents the gold standard for the diagnosis of gastroesophageal reflux. Ambulatory esophageal pH recording provides a better reflection of occurrences under normal domestic living conditions, but it may influence physical activity. The aim of this study was to assess the influence of ambulatory esophageal pH recording on physical activity in children.
Patients And Methods:
This prospective study included 22 patients (18 boys, 4 girls) 3 to 15 years old (mean age 6.9 +/- 2.3 years) who had been referred for ambulatory pH-metry. The 24-hour physical activity was measured twice in each child using a triaxial accelerometer 1 week before or after pH-metry and during pH-metry. Levels of intensity of physical activity (low: sedentary activities; moderate: walking; high: intense activities such as jumping, running, and sport) were compared by the paired nonparametric Wilcoxon test.
Results:
Physical activity was 53% lower during 24-hour pH-metry than when it was not present (P < 0.0005). The duration of low-level physical activity was longer during pH-metry (84% vs 73%; P < 0.01). The duration of moderate-intensity and high-intensity physical activity was shorter during pH-metry (16% vs 24% and 0.2% vs 2.2%, respectively; P < 0.005 and P < 0.0001).
Conclusions:
Ambulatory 24-hour esophageal pH recording substantially decreases physical activity, mainly high-level physical activity. Whether such changes in activity decrease the sensitivity of pH-metry and lead to false negative results in some children remains to be assessed.

Related Concept Videos
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:21
Barrett Esophagus-I: Introduction
This constant acid exposure transforms the esophagus's pink mucosal lining (stratified squamous epithelium) into a type of lining more similar...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:24
Esophagus
The movement of edibles from the pharynx into the esophagus is facilitated by the upper esophageal sphincter, which is formed primarily by the...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:21
Stomach pH Regulation
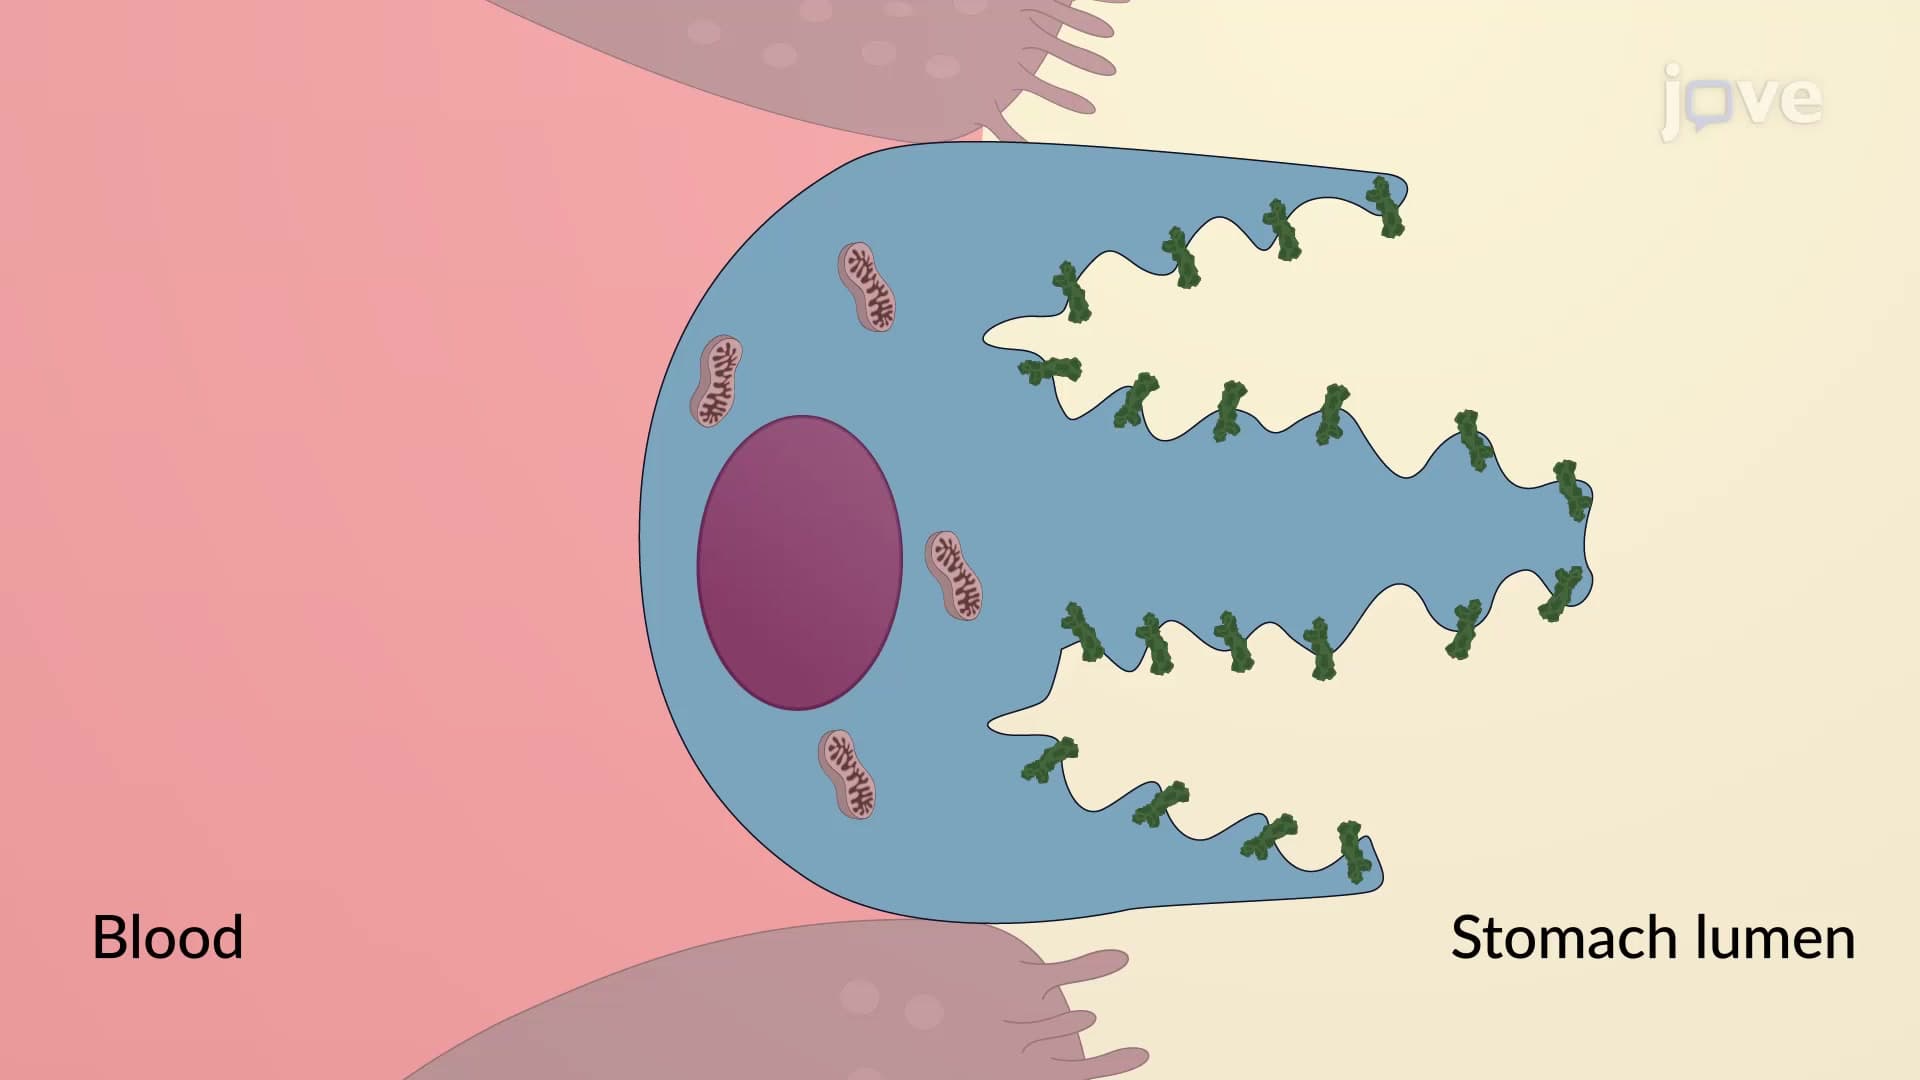
The acid-secreting gastric mucosal epithelial cells (parietal cells) lining the stomach lumen maintain the low pH in the lumen. Numerous ion transporters and channels on these parietal...