Related Experiment Video
Updated: Jun 24, 2026
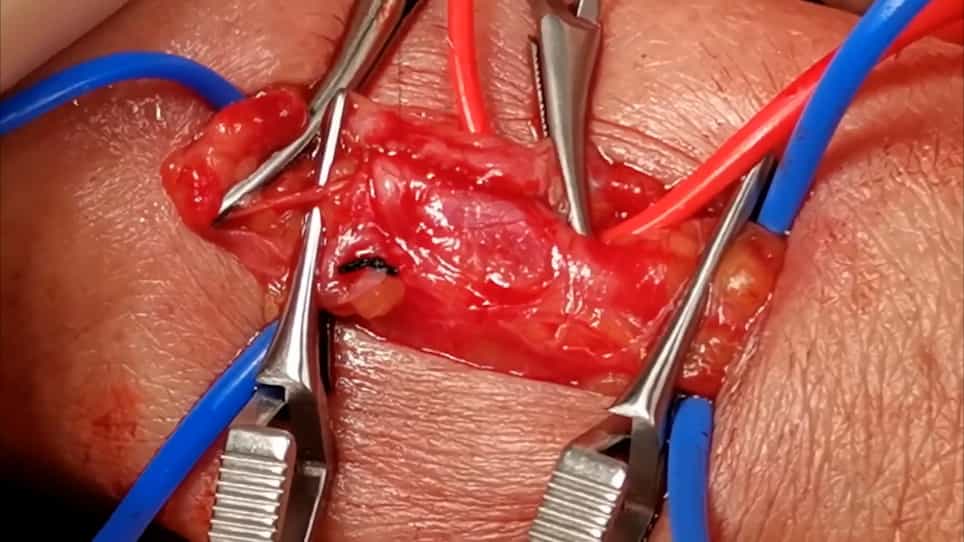

Creating Radio-cephalic Arteriovenous Fistula in the Forearm with a Modified No-Touch Technique
Published on: April 1, 2022
Radial artery achieves better flowmetric results than saphenous vein in the elderly
Giuseppe Santarpino1, Francesco Onorati, Cristian Scalas
1Cardiac Surgery Unit, Magna Graecia University of Catanzaro, Catanzaro, Italy.

Insights
In elderly patients undergoing coronary artery bypass grafting (CABG), radial artery (RA) grafts show superior flow compared to saphenous vein (SV) grafts, with similar clinical outcomes. This suggests RA may be a better choice for arterial grafting in this population.
Area of Science:
- Cardiovascular Surgery
- Vascular Grafting
- Geriatric Cardiology
Background:
- Complete arterial grafting in the elderly is debated due to concerns about limited life expectancy and potential morbidity.
- The radial artery (RA) and saphenous vein (SV) are commonly used conduits for coronary artery bypass grafting (CABG).
Purpose of the Study:
- To compare transit time flow (TTF) and clinical outcomes of elderly patients (>or=70 years) undergoing CABG using either RA or SV as the second conduit.
- To evaluate graft flow reserve (GFR), pulsatility index (P.I.), and clinical, biochemical, and echocardiographic results.
Main Methods:
- Prospective study of 75 elderly patients receiving RA CABG (Group A) and 163 receiving SV CABG (Group B) between 2003-2007.
- Comparison of TTF parameters (max flow, mean flow, P.I., GFR), hospital outcomes, and one-year follow-up data.
- Analysis included echocardiography and troponin I leakage.
Main Results:
- RA grafts demonstrated significantly higher maximum and mean flow, and lower P.I. compared to SV grafts.
- Significantly higher GFR values were observed in RA conduits.
- Comparable troponin I leakage and postoperative hospital outcomes were noted between groups.
- One-year follow-up revealed better freedom from acute cardiovascular events in the RA group (P=0.04).
Conclusions:
- Despite similar clinical, biochemical, and echocardiographic results, RA grafting in elderly patients yields superior flowmetric performance compared to SV grafting.
- RA conduits show enhanced flow dynamics, including higher mean flow and GFR, and lower P.I.
- These findings support the use of radial artery grafts in elderly patients undergoing CABG for improved graft function.
Abstract:
Due to the limited life expectancy and the supposed higher morbidity with complete arterial grafting, extensive arterial graft in the elderly is still questioned. It was the aim of this study to evaluate transit time flow and clinical, biochemical and echocardiographic results of elderly patients undergoing coronary artery bypass grafting (CABG) with either saphenous vein (SV) or radial artery (RA) employed as the second conduit of choice. The present study evaluates clinical and flowmetric results of a prospective series of elderly patients (>or=70 years old) undergoing RA CABG (75 patients, Group A) or SV CABG (163 patients, Group B) during isolated myocardial revascularization, performed either off-pump (OPCABG) and on-pump during the last 5 years at a single academic institution (between January 2003 and December 2007). Transit time flowmetric (TTF) maximum and mean flow, pulsatility index (P.I.), and graft flow reserve (GFR) were compared. Hospital outcome was analyzed. Clinical data were compared between the two groups and one-year follow-up was completed. The two groups showed comparable preoperative and intraoperative variables. When TTF analysis was considered, patients undergoing RA grafting demonstrated a significantly higher maximum (systolic) and mean flow compared to SV grafting, either in circumflex, diagonal, and right coronary territory. Pulsatility index was significantly lower in the RA group in circumflex, diagonal, and right coronary grafts. Furthermore, when GFR was calculated significantly higher values were found in RA conduits in the circumflex, diagonal, and right coronary grafts. Comparable troponin I leakage was detected between the two groups. Postoperative variables addressing hospital outcome were similar in the two groups. When echocardiographic data were analyzed, no differences were recorded in postoperative recovery of left ventricular ejection fraction and wall motion score index. One-year follow-up showed better freedom from acute cardiovascular events in the RA group (P = 0.04). Our data show that despite comparable clinical, biochemical, and echocardiographic results in elderly patients undergoing RA or SV grafting, better flowmetric results - in terms of GFR, mean flow, and pulsatility index - can be detected in arterial conduits.
More Related Videos
 08:05
Occlusion of the Great and Small Saphenous Vein Using Copolymeric Glue Based on N-Butyl Cyanoacrylate and Methacryloxy Sulfolane
Published on: December 9, 2022
 08:42
Ultrasound Assessment of Endothelial-Dependent Flow-Mediated Vasodilation of the Brachial Artery in Clinical Research
Published on: October 22, 2014
Related Concept Videos
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:11
Assessment of radial pulse
The radial pulse, located at the wrist, is often the preferred site for assessing peripheral pulse because of its accessibility and dependability. The process of determining the radial pulse involves several steps:
 01:21
Sites for measuring blood pressure
The Brachial Artery: Primary Site for Blood Pressure Measurement
 01:27
Assessment of the Cardiovascular System III: Palpation
Jugular Venous Pressure (JVP) Measurement
Position the patient at a thirty- to forty-five-degree angle or in a semi-fowler's position. Look for the highest point of pulsation in the internal jugular vein and measure the vertical distance to the angle of Loius or sternal angle. A normal JVP is 3-4 cm above the...
 01:17
Veins of Upper Limbs
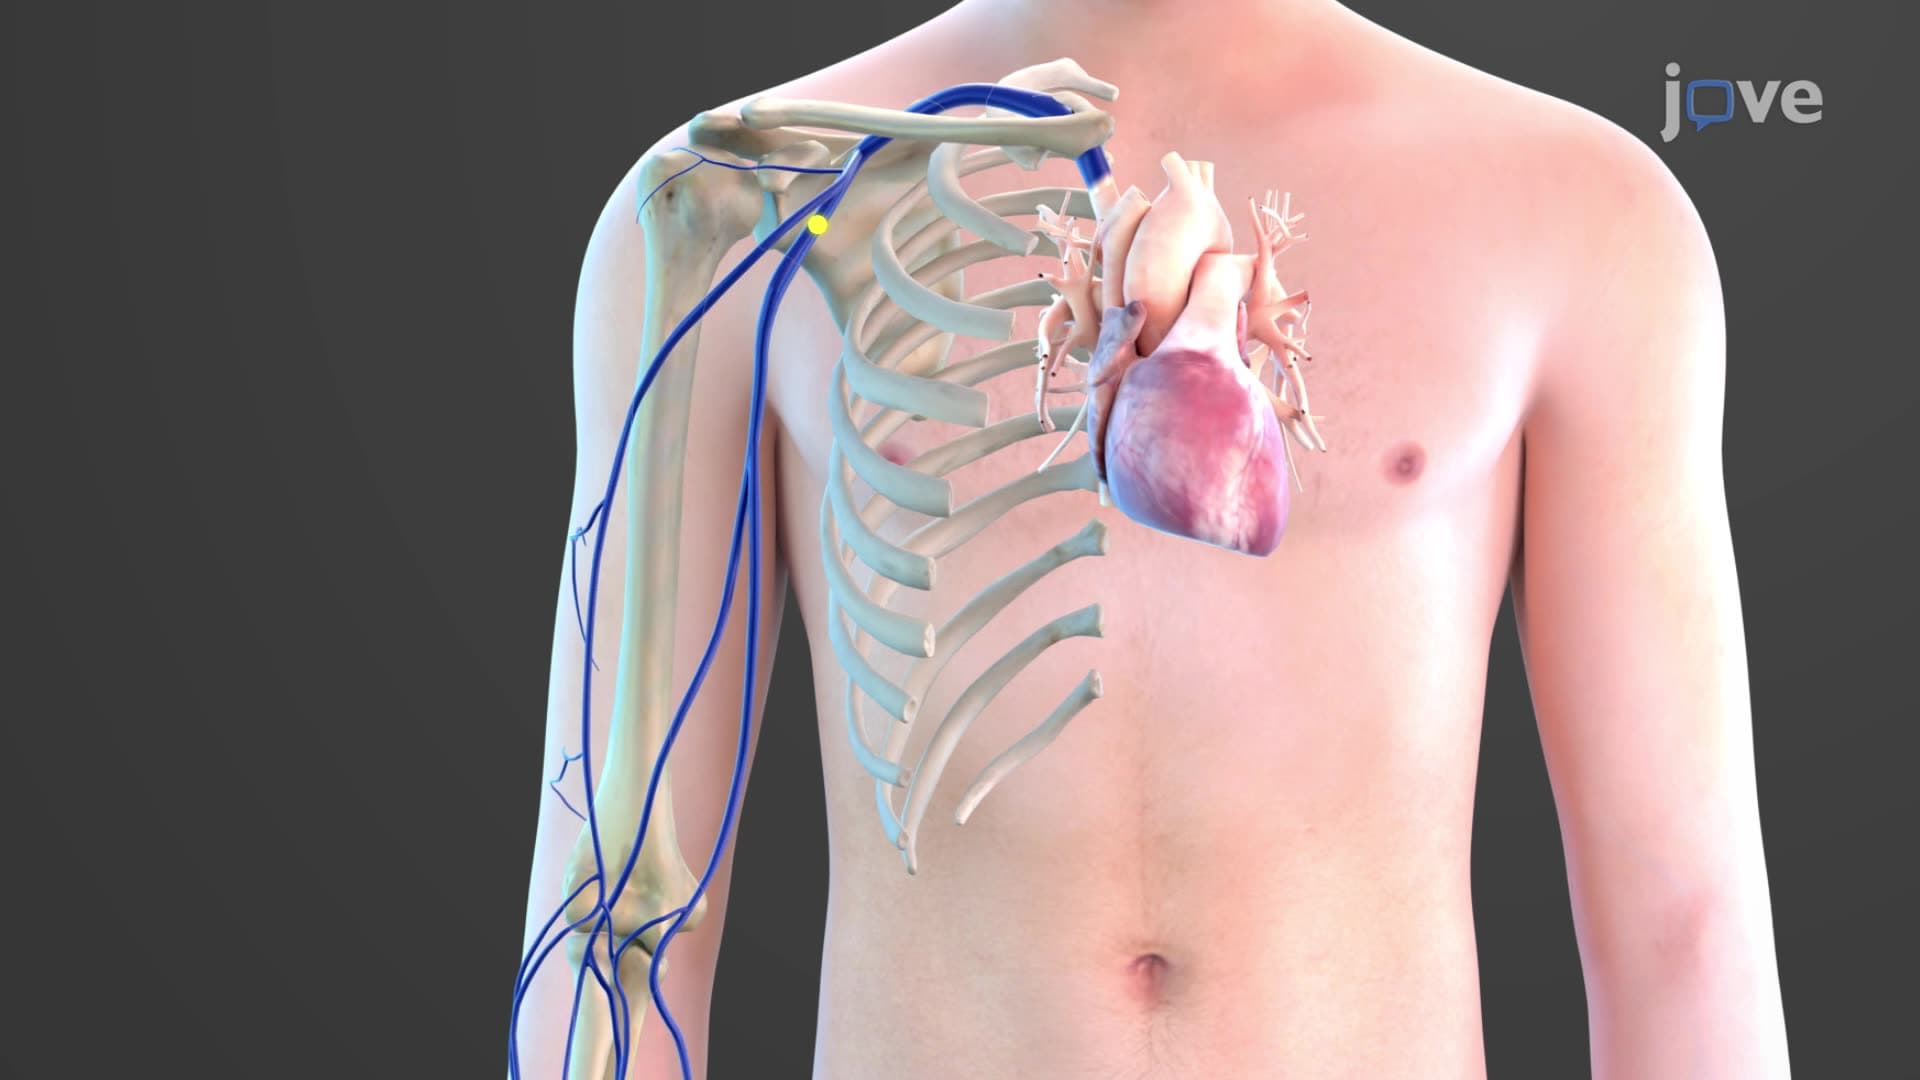
The deep venous system is primarily composed of the ulnar and radial veins. The ulnar vein, which drains the fingers through the superficial palmar venous arches, and the radial vein, which serves the palms via the deep palmar...
 01:25
Hemodialysis I: Introduction