Related Experiment Videos
Presentation and management of post-treatment relapse in autoimmune pancreatitis/immunoglobulin G4-associated
Neomal S Sandanayake1, Nicholas I Church, Michael H Chapman
1Department of Gastroenterology, University College Hospital, London, United Kingdom; Institute of Hepatology, University College London, London NW1 2BU, United Kingdom.

Background & Aims:
Autoimmune pancreatitis (AIP) is a multisystem disorder that often has extrapancreatic manifestations such as immunoglobulin G4-associated cholangitis (IAC). Patients respond rapidly to steroids but can relapse after therapy. We assessed the clinical management of relapse in a group of patients with AIP/IAC.
Methods:
We performed a prospective study of patients diagnosed with AIP from 2004-2007 who received steroids. Treatment outcome was defined clinically, radiologically, and biochemically as response to steroids, remission after steroids, failure to wean steroids, and relapse. Steroids +/- azathioprine (AZA) were used to treat patients who failed, relapsed, or could not be weaned from steroids.
Results:
Twenty-eight patients with AIP were studied; 23 (82%) had IAC. All patients responded within 6 weeks to prednisolone therapy. Twenty-three patients achieved remission after a median of 5 months of treatment (range, 1.5-17 months), whereas 5 patients (18%) could not be weaned because of a disease flare. Of the patients who achieved remission, 8 of 23 (35%) subsequently relapsed. Overall, 13 of 23 patients (57%) with AIP/IAC relapsed, compared with 0 of the 5 with isolated AIP (P = .04, Fisher exact test). Steroids were increased/restarted in all patients who relapsed; 10 also received AZA. Remission was achieved and maintained in 7 patients; they remain on AZA monotherapy at a median of 14 months (range, 1-27 months).
Conclusions:
Relapse or failure to wean steroids occurred in 46% of patients with AIP. Patients with IAC are at particularly high risk of relapse. AZA appears to be effective in patients with post-treatment relapse or who cannot be weaned from steroids. To view this article's video abstract, go to the AGA's YouTube Channel.
Related Concept Videos
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:25
Acute Pancreatitis I: Introduction
 01:27
Acute Pancreatitis I: Introduction
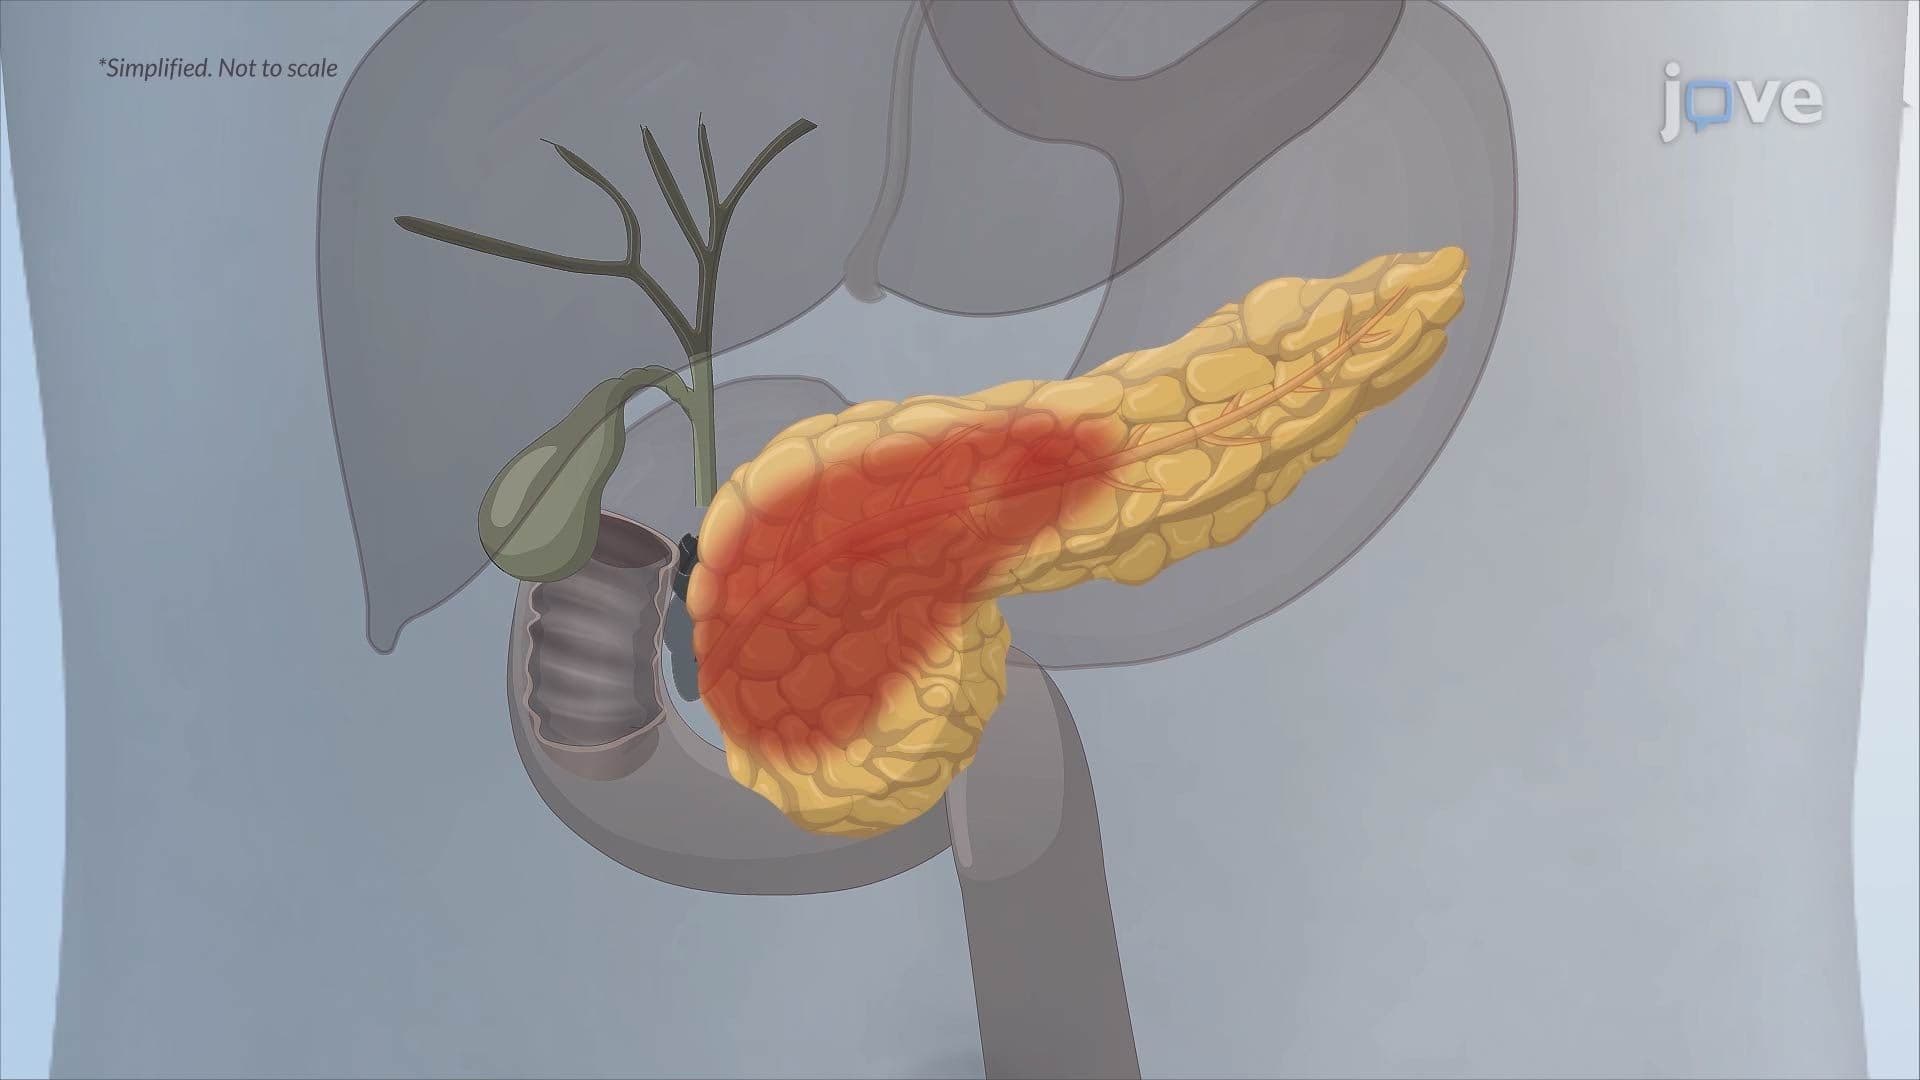
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include:
 01:25
Chronic Pancreatitis I: Introduction
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...