Related Experiment Video
Updated: Jun 24, 2026
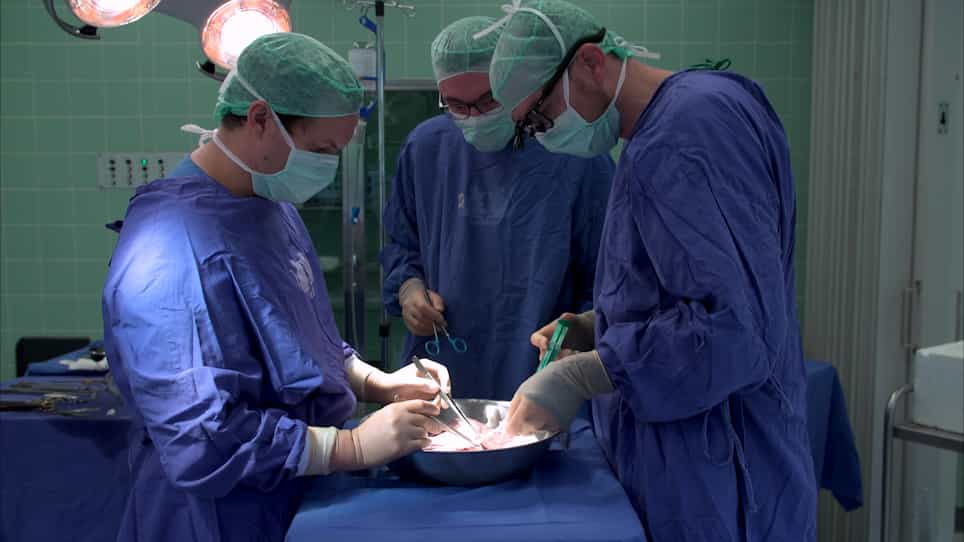

Porcine Liver Transplantation Without Veno-Venous Bypass As an Extended Criteria Donor Model
Published on: August 17, 2022
Liver transplantation: an update 2009
Catherine Skagen1, Michael Lucey, Adnan Said
1Gastroenterology and Hepatology, University of Wisconsin School of Medicine and Public Health, Madison, Wisconsin 53792, USA.

Insights
Living donor liver transplantation offers a viable option to increase transplants and reduce waitlist deaths. However, donor risks and hepatocellular carcinoma recurrence require further study, while careful management is crucial for HIV-positive recipients.
Area of Science:
- Hepatology
- Transplant Surgery
- Immunology
Background:
- Liver transplantation faces challenges including donor organ shortage and managing complex recipient populations.
- Living donor liver transplantation (LDLT) and transplantation in human immunodeficiency virus (HIV)-positive individuals represent evolving areas.
- Hepatocellular carcinoma (HCC) management and down-staging prior to liver transplant are critical concerns.
Purpose of the Study:
- To review current challenges and advancements in liver transplantation.
- Focus on living donor liver transplant, HIV-positive recipients, and HCC down-staging.
- To provide insights into outcomes, risks, and future directions in these areas.
Main Methods:
- Review of recent studies and cohort data on liver transplantation outcomes.
- Analysis of recipient and donor data for living donor liver transplantation.
- Evaluation of outcomes and management strategies for HIV-positive and coinfected recipients.
- Assessment of down-staging techniques for hepatocellular carcinoma.
Main Results:
- LDLT outcomes are comparable to deceased donor transplants, but with higher HCC recurrence rates and donor morbidity/mortality concerns.
- Liver transplantation in selected HIV-positive recipients shows equivalent outcomes to HIV-negative recipients; coinfected recipients have less favorable outcomes.
- Drug interactions between immunosuppressants and antiretroviral therapy necessitate dose adjustments.
- Loco-regional therapy for HCC down-staging is expanding, with waiting time post-therapy predicting recurrence.
Conclusions:
- LDLT is a viable strategy to increase transplants and reduce waitlist mortality, though donor risks and HCC recurrence need further investigation.
- Careful management and coordination are essential for HIV-positive liver transplant recipients.
- The role of loco-regional therapies in down-staging HCC is growing and shows promise.
Purpose Of Review:
In this review we focus on three challenging aspects of liver transplantation: living donor liver transplant, transplantation in HIV-positive recipients and down-staging of hepatocellular carcinoma for liver transplantation.
Recent Findings:
The adult-to-adult living donor liver transplantation cohort study is providing valuable information on recipient and donor outcomes associated with living donor liver transplantation. The recipient outcomes with living donor liver transplantation are comparable to those with deceased donor liver transplantation for most diseases, but increased hepatocellular carcinoma recurrence has been reported with living donor liver transplantation. Donor morbidity is not infrequent and donor mortality remains a concern. Liver transplantation for HIV-positive recipients is associated with equivalent outcomes as HIV-negative recipients for selected recipients. Transplantation in coinfected recipients (HIV and HCV+) is associated with less favorable outcomes. Drug interaction between immunosuppression and highly active antiretroviral therapy is increasingly recognized and requires major modifications in dosing. Down-staging hepatocellular carcinoma to within transplant criteria is being used in some centers using loco-regional therapy. Waiting time after loco-regional therapy is currently the best predictor of recurrence. The role of newer chemotherapeutics is being tested as part of neoadjuvant therapy after resection or loco-regional therapy.
Summary:
Living donor liver transplantation is a viable strategy to increase transplantation and reduce death on the waiting list. Donor morbidity should be the subject of further efforts to minimize these risks. The increased recurrence risk with living donor liver transplantation for hepatocellular carcinoma warrants further study. Careful coordination between transplant professionals and HIV experts is necessary to monitor issues of posttransplant care of the HIV-infected recipient. The role of loco-regional therapies in down-staging patients with hepatocellular carcinoma is expanding.

Related Concept Videos
 01:28
Kidney Transplant I: Introduction
 01:26
Kidney Transplant II: Surgical Procedure
 01:24
Tissue Transplantation
The Biology of Tissue Transplantation
The biology of tissue transplantation hinges on the Major Histocompatibility Complex (MHC) molecules. These molecules...