Related Experiment Video
Updated: Jun 24, 2026

Quantitative 3D In Silico Modeling (q3DISM) of Cerebral Amyloid-beta Phagocytosis in Rodent Models of Alzheimer's Disease
Published on: December 26, 2016
Critical issues for successful immunotherapy in Alzheimer's disease: development of biomarkers and methods for early
Rawan Tarawneh1, David M Holtzman
1Department of Neurology, Washington University School of Medicine, St. Louis, MO 63110, USA.

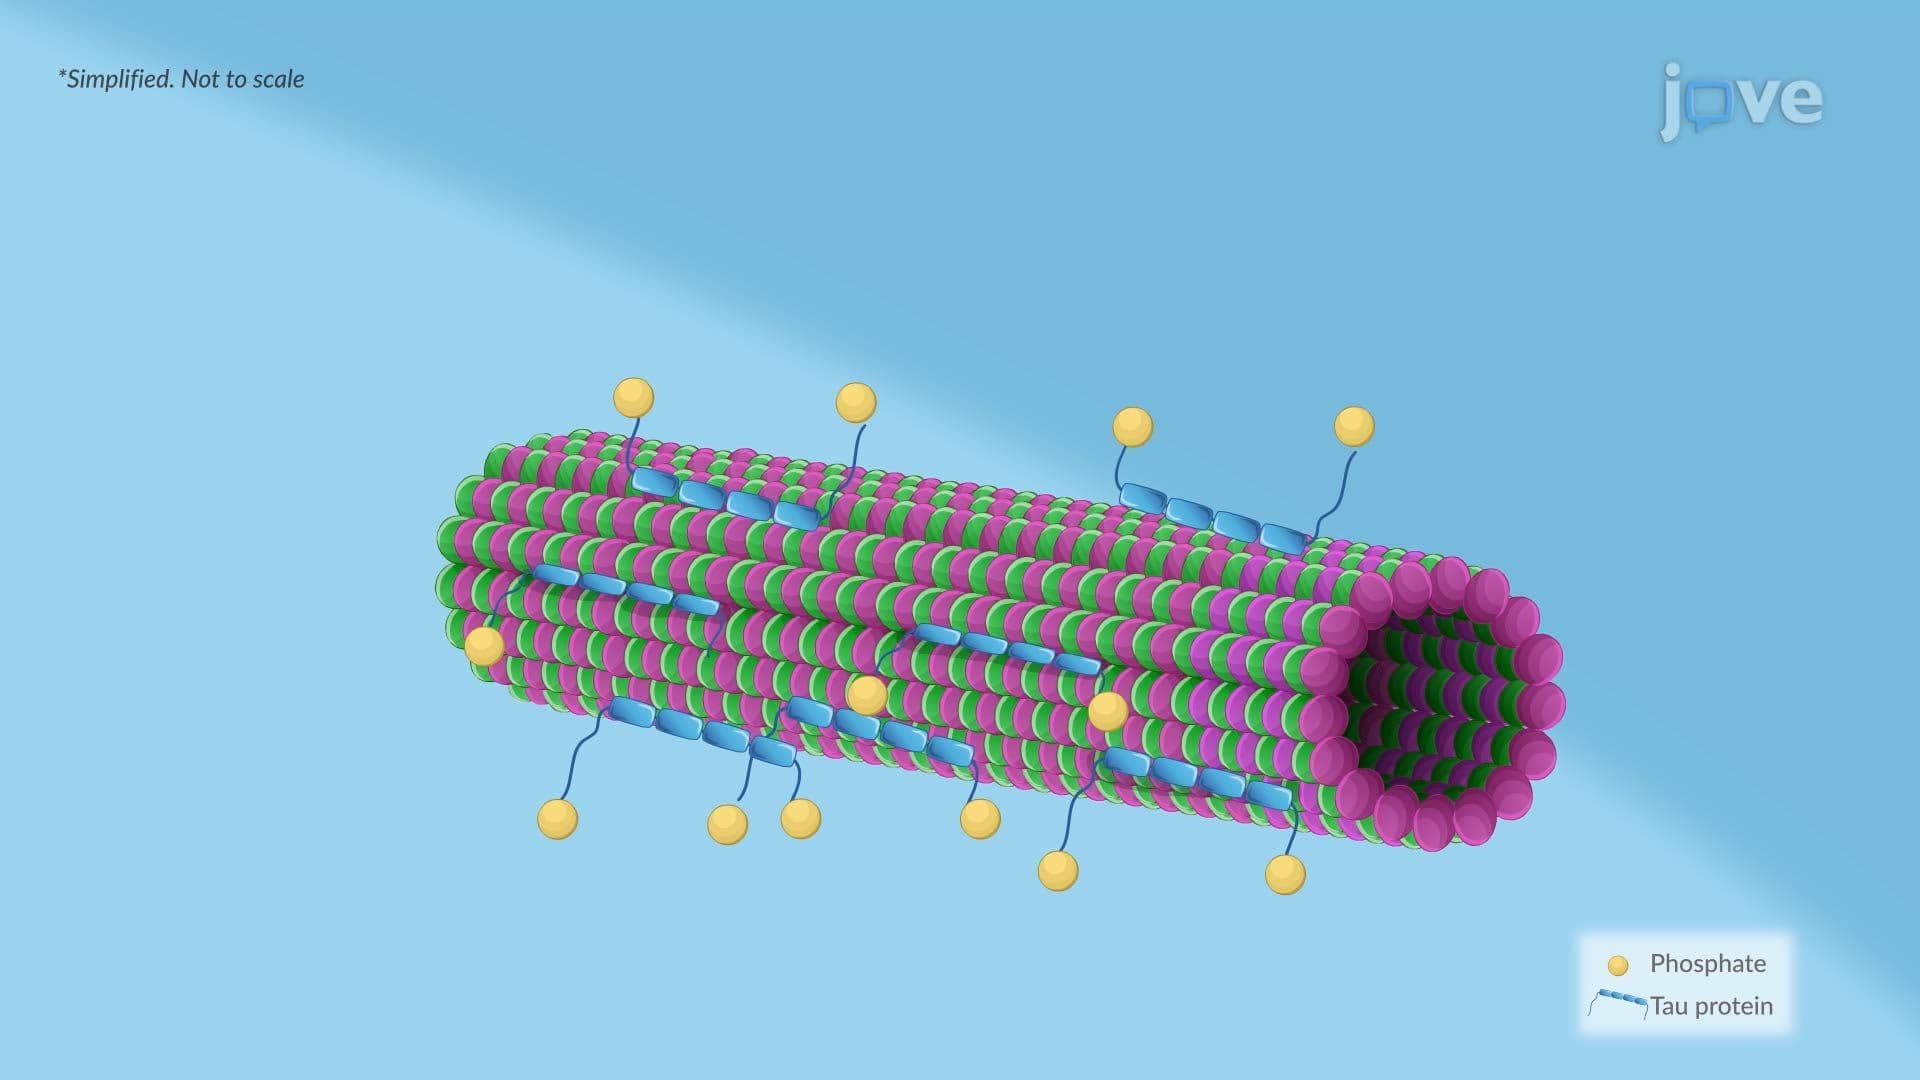
Over the last 10 years, promising data has emerged from both animal and human studies that both active immunization with amyloid-beta (Abeta) as well as passive immunization with anti-Abeta antibodies offer promise as therapies for Alzheimer's disease (AD). Data from animal models suggests that antibodies to Abeta through several mechanisms can decrease Abeta deposition, decrease Abeta -associated damage such as dystrophic neurite formation, and improve behavioral performance. Data from human studies suggests that active immunization can result in plaque clearance and that passive immunotherapy might result in slowing of cognitive decline. Despite this, a recent analysis from a phase I trial that involved active immunization with Abeta42, while not powered to determine efficacy, suggested no large effect of active immunization despite the fact that plaque clearance was very prominent in some subjects. An important issue to consider is when active or passive immunization targeting Abeta has the chance to be most effective. Clinico-pathological and biomarker studies have shown that in terms of the time course of AD, Abeta deposition probably begins about 10-15 years prior to symptom onset (preclinical AD) and that tau aggregation in tangles and in neurites does not begin to accelerate and build up in larger amounts in the neocortex until just prior to symptom onset. By the time the earliest clinical signs of AD emerge, Abeta deposition may be close to reaching its peak and tangle formation and neuronal cell loss is substantial though still not at its maximal extent. Since immunization targeting Abeta does not appear to have major effects on tangle pathology, for immunization to have the most chance for success, performing clinical trials in individuals who are cognitively only very mildly impaired or even in those with preclinical AD would likely offer a much better chance for success. Current work with AD biomarkers suggests that such individuals can now be identified and it seems likely that targeting this population with immunization strategies targeting Abeta would offer the best chance of success.
Over the last 10 years, promising data has emerged from both animal and human studies that both active immunization with amyloid-beta (Abeta) as well as passive immunization with anti-Abeta antibodies offer promise as therapies for Alzheimer's disease (AD). Data from animal models suggests that antibodies to Abeta through several mechanisms can decrease Abeta deposition, decrease Abeta -associated damage such as dystrophic neurite formation, and improve behavioral performance. Data from human studies suggests that active immunization can result in plaque clearance and that passive immunotherapy might result in slowing of cognitive decline. Despite this, a recent analysis from a phase I trial that involved active immunization with Abeta42, while not powered to determine efficacy, suggested no large effect of active immunization despite the fact that plaque clearance was very prominent in some subjects. An important issue to consider is when active or passive immunization targeting Abeta has the chance to be most effective. Clinico-pathological and biomarker studies have shown that in terms of the time course of AD, Abeta deposition probably begins about 10-15 years prior to symptom onset (preclinical AD) and that tau aggregation in tangles and in neurites does not begin to accelerate and build up in larger amounts in the neocortex until just prior to symptom onset. By the time the earliest clinical signs of AD emerge, Abeta deposition may be close to reaching its peak and tangle formation and neuronal cell loss is substantial though still not at its maximal extent. Since immunization targeting Abeta does not appear to have major effects on tangle pathology, for immunization to have the most chance for success, performing clinical trials in individuals who are cognitively only very mildly impaired or even in those with preclinical AD would likely offer a much better chance for success. Current work with AD biomarkers suggests that such individuals can now be identified and it seems likely that targeting this population with immunization strategies targeting Abeta would offer the best chance of success.
Related Concept Videos
 01:26
Alzheimer's Disease: Overview
The clinical diagnosis of AD hinges on the presence of memory and other cognitive impairments. Biomarkers, such as changes in Aβ and tau...
 01:22
Alzheimer's Disease: Treatment
 01:29
Alzheimer Disease l: Introduction
 01:23
Alzheimer Disease ll: Pathophysiology